What is rubella, and why is a mild illness worth a note?
Rubella, also called German measles, is the mildest of the six classic childhood exanthems. It is caused by a rubivirus, a single-stranded RNA virus of the family Matonaviridae. It is a different virus from the measles virus, despite the older name, which reflects the time when rubella was thought to be a variant of measles or scarlet fever.
For the child the illness is mild, so its importance lies almost entirely in who is not immune, rather than in what it does to the child. The people around the child include non-immune people, and that is where the weight falls. Rubella in pregnancy and congenital rubella syndrome belong to the topic of congenital and maternal infections, so they are not taught here.
Rubella virus has no reservoir other than humans, so it persists only through spread from person to person. How does it spread, and why does it so often go unnoticed?
How does the virus travel, and why does it spread unseen?
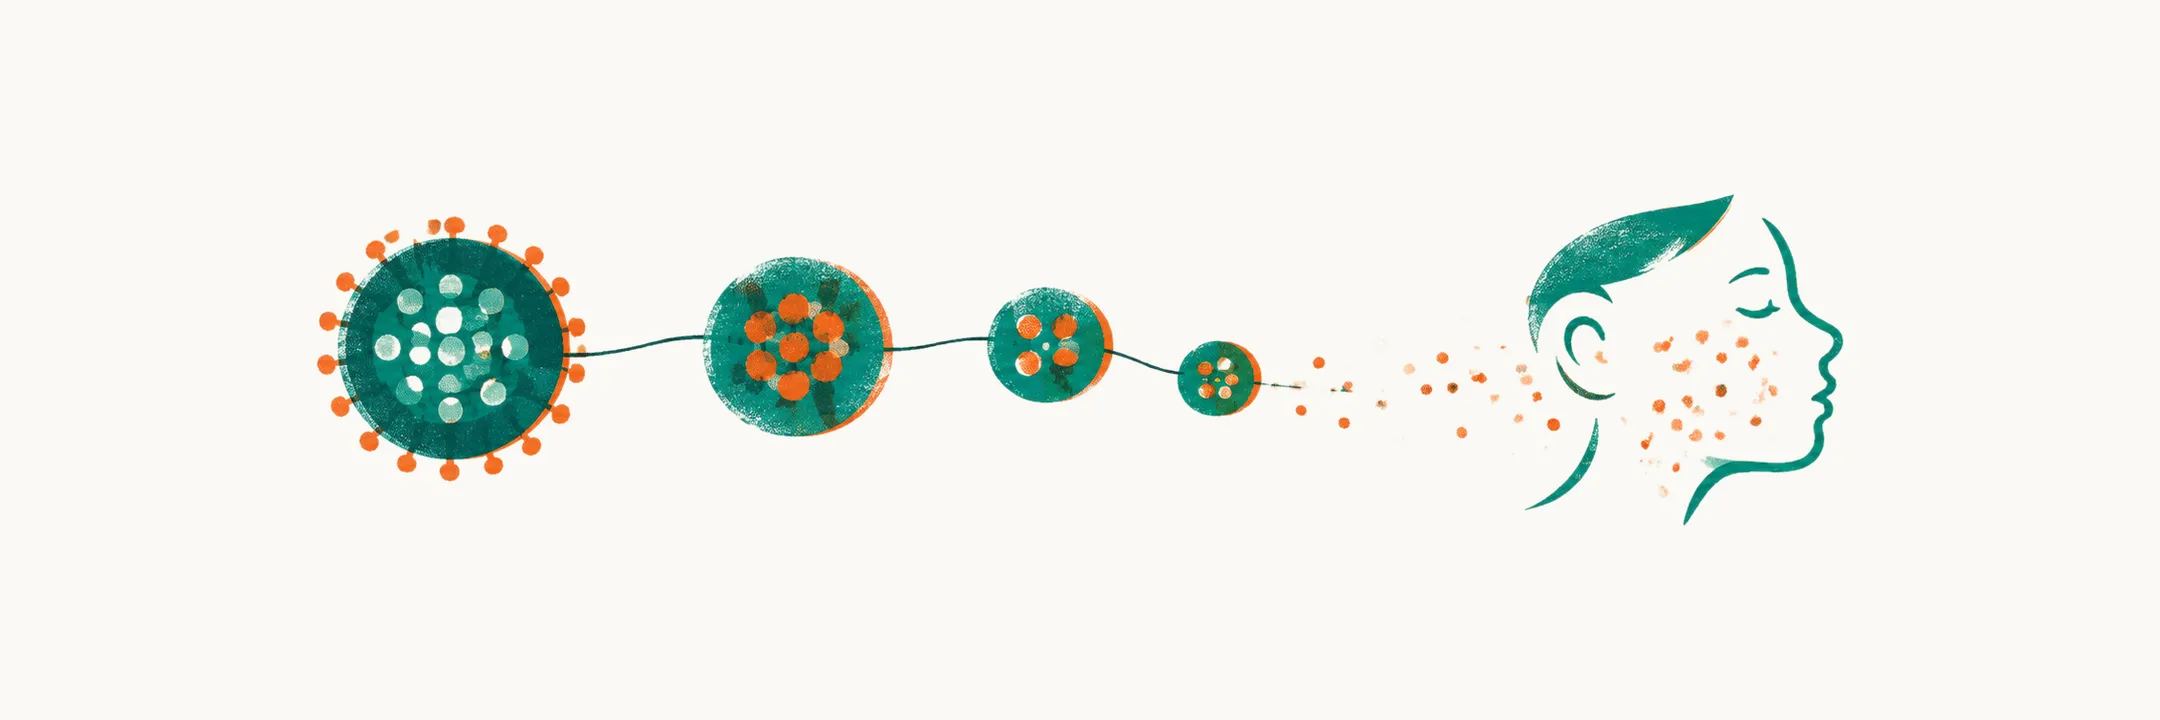
The virus passes by direct or droplet contact with nasopharyngeal secretions. It replicates first in the nasopharynx and the regional lymph nodes, and then it reaches the blood. The incubation period averages 14 days, with a range of 12-23 days, so the virus spreads through the body for about two weeks before the illness shows itself.
Many infections stay quiet along the way: up to half of infections are subclinical, producing no symptoms. Because of this, rubella can circulate without anyone noticing, transmitted by people who never develop a rash and never know they were infected. A person with no symptoms can still shed the virus, so the chain of spread is invisible.
When the illness does show itself, what does it look like?
What does a child with rubella look like, and how does age change it?
The clinical picture depends on age. In young children the rash is usually the first symptom, and a prodrome (the symptoms before the rash) is uncommon. In older children and adults there may be a prodrome of 1-5 days, with low-grade fever, malaise and upper respiratory symptoms before the rash.
Lymphadenopathy is the most useful early finding. The postauricular, occipital and posterior cervical lymph nodes enlarge. This is consistent with the route of the virus, since the first nodes involved are the ones near the nasopharynx and scalp. The enlargement characteristically begins about a week before the rash, so it can give the illness away earlier than the rash does. It may be generalised, and it can persist for several weeks. It is more prominent, and more diagnostically useful, than in the other classic exanthems.
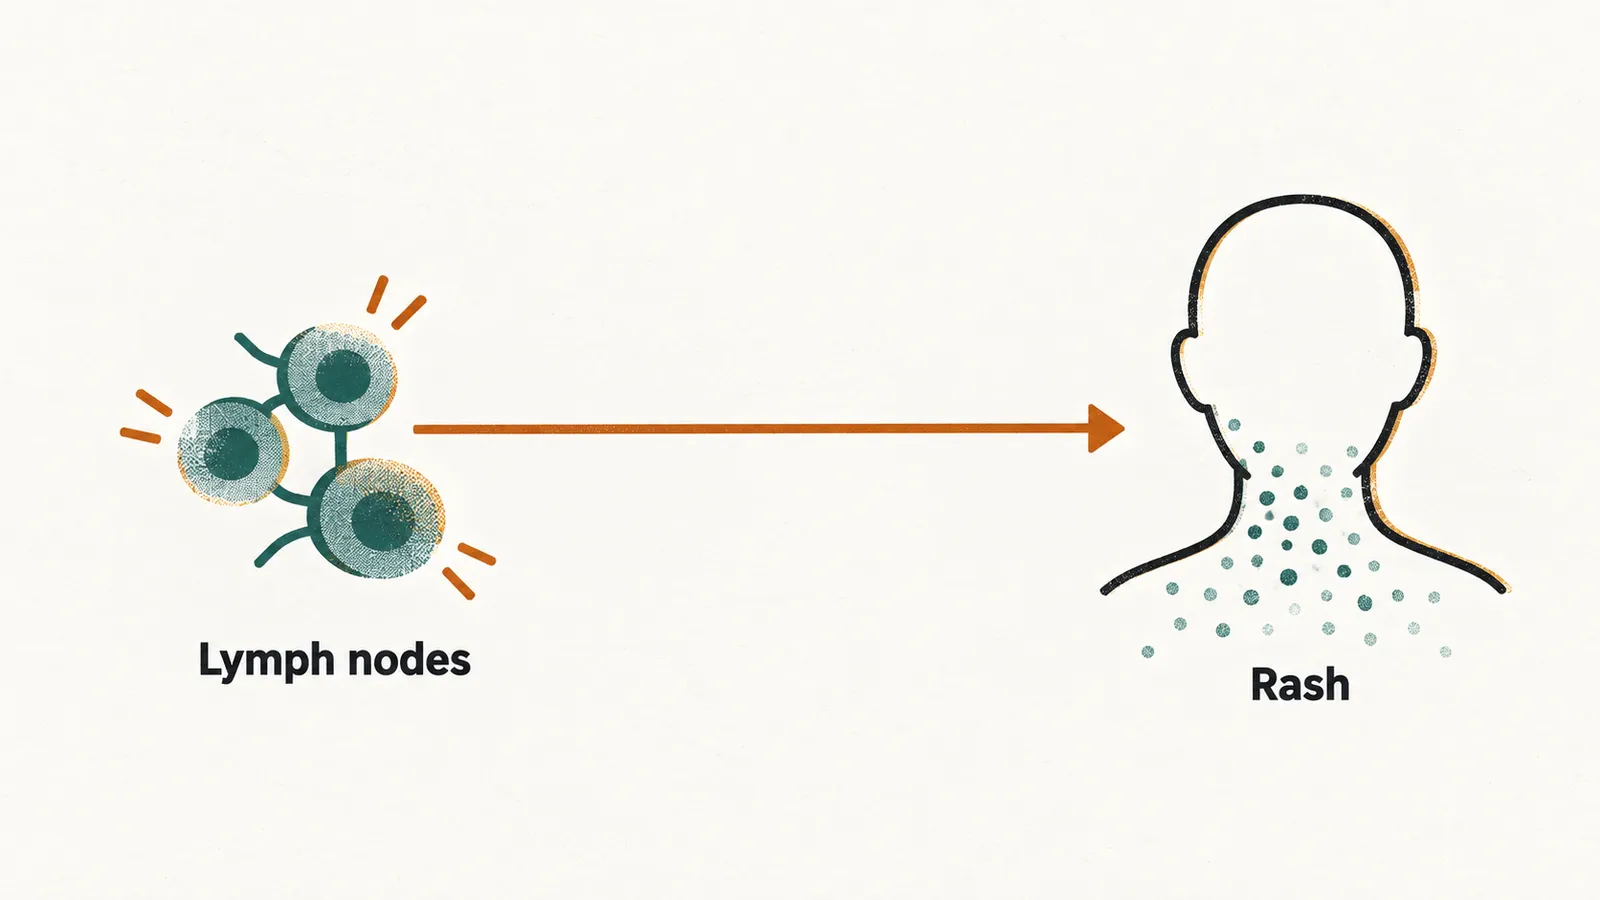
The rash comes at the end of the incubation period, 14-17 days after exposure, and it is the point at which the illness becomes visible. It is maculopapular. It begins on the face, becomes generalised within about 24 hours and spreads rapidly downwards, in the head-to-foot direction described in the Diagnostic Framework for Childhood Exanthems. It lasts about 3 days and fades without desquamation. Two features contrast with Measles:
- The rash is fainter than the measles rash.
- The rash does not coalesce into confluent patches.
On the soft palate, small red spots (Förchheimer spots) are described in a minority of cases. They are an enanthem, the same kind of eruption as the rash but on a mucous membrane, and they are not diagnostic.
The picture changes again in adults.
Joint symptoms in adults
Joint symptoms are rare in children and in adult men. They occur frequently in adult women, up to 70% in reported series. They usually begin around the time the rash appears and last up to about a month.
Since the rash alone does not settle the diagnosis, how is rubella confirmed?
How is rubella confirmed, and why not by the rash?
Measles, scarlet fever, fifth disease and drug eruptions all produce rashes that can pass for rubella, and no single feature of the rash separates them. The Förchheimer spots do not help either, as they are not diagnostic. So confirmation rests on laboratory testing rather than on the appearance of the rash.
Three tests each show that the body has met the virus recently:
- rubella-specific IgM, the antibody class of recent infection;
- a significant rise in IgG, the longer-lasting antibody class, between paired samples;
- PCR on a throat or nasopharyngeal swab.
IgG persists, so it marks past exposure or vaccination rather than a current infection. That is why IgG without IgM documents immunity in someone whose vaccination history is unclear.
Once the diagnosis is suspected or confirmed, what can be done?
What can be done for the child, and for those around?
There is no specific antiviral treatment; care is supportive. Management therefore turns to limiting spread, because the weight of rubella falls on the non-immune people around the child.
The timing of spread explains how this is done. A person with rubella is most contagious when the rash erupts, and can transmit from about 7 days before to 7 days after the rash appears. The prodrome and subclinical cases are infectious too. Because of this, exposure usually happens before the rash identifies the illness.
Suspected cases are isolated until 7 days after the rash appears, and they are reported to public health authorities. The contacts were exposed before the rash, so contact assessment begins as soon as rubella is suspected, not waiting for laboratory confirmation.
Isolation limits spread once the illness is suspected. How is rubella prevented before that?
How is rubella prevented?
Two doses of MMR (measles-mumps-rubella) vaccine prevent rubella. In the Italian national vaccination plan (PNPV 2023-2025), the first dose is given in the second year of life and the booster at 5-6 years. The first dose waits until after the first birthday for a biological reason: maternal antibody neutralises the vaccine if it is given earlier, as in measles.
Another mild rash matters most to the people around the child, such as a pregnant woman at home, yet there the child is no longer infectious once the rash appears. What is that illness, and why does a harmless-looking rash matter there?