What is varicella, and how does the same virus later cause zoster?
Varicella (chickenpox) is diagnosed from the skin, not by exclusion. Varicella is the only vesicular member of the six classic childhood exanthems, so the vesicles themselves point to it. Other vesicular eruptions, such as zoster, herpes simplex and hand-foot-and-mouth disease, can look alike, and the stages of the rash help to tell them apart.
The cause is varicella-zoster virus (VZV), a double-stranded DNA herpesvirus. Primary VZV infection, the first meeting with the virus, produces varicella. The feature of herpesviruses that matters here is persistence: the virus is not cleared. After varicella it establishes lifelong latency (a dormant state) in the dorsal root ganglia, which are clusters of sensory nerve cell bodies beside the spinal cord. A latent virus can reactivate, and reactivation decades later produces herpes zoster (shingles). Because the virus hides in the cell bodies of one ganglion and returns along that ganglion’s nerve, zoster is usually confined to one dermatome, the strip of skin supplied by that nerve root.
So varicella and zoster are one virus behaving in two different ways. A person with zoster can also transmit varicella to a susceptible contact through contact with the lesions: the vesicles of zoster hold virus, and a susceptible person is meeting the virus for the first time, so the illness that results is varicella, not zoster.
How does the virus reach the skin, and when can the child spread it?
VZV spreads by respiratory droplets, which can carry infected secretions, and by direct contact with vesicle fluid. It also spreads by airborne transmission of aerosolised virus in closed spaces. The skin lesions are the major source of transmissible virus, which is part of why the disease is highly contagious: up to 90% of susceptible close household contacts develop varicella after exposure.
After the virus is breathed in, it has to multiply near its entry point, spread in the blood to other organs and reach the skin in a second round before any rash can appear. That takes about two weeks: the incubation period is typically 14-16 days after exposure, with a range of 10-21 days.
Because the virus must spread through the body before it reaches the skin, the illness announces itself late, after the child has begun to spread it. The child is contagious from 1-2 days before the rash appears until all lesions have crusted, since the virus is in the lesions and secretions and a crusted lesion no longer holds infectious virus. The infectious period therefore begins before the diagnosis is obvious, so isolating a child only once the rash is recognised comes late.
A mild prodrome of fever and malaise may precede the rash by 1-2 days. The prodrome is more prominent in adolescents and adults, whose illness tends to be more severe, than in young children. In young children the rash is often the first abnormality noticed.
What does the rash look like, and why can the stages be told apart?
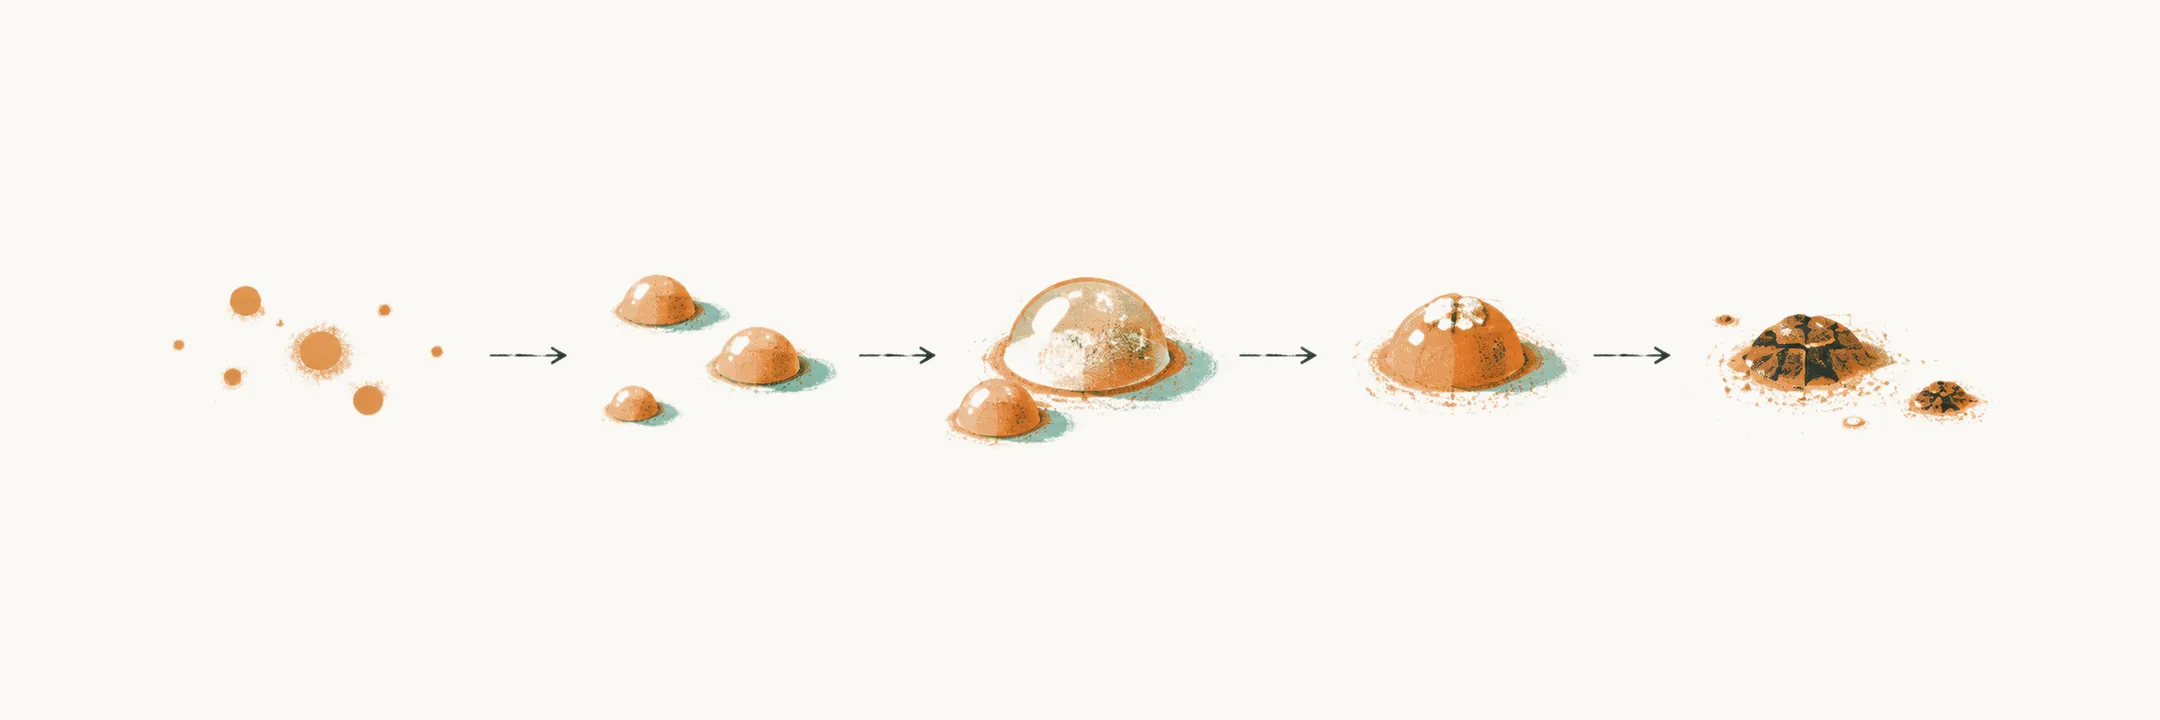
The second round of spread reaches the skin in crops. New lesions keep appearing for the first 4-5 days while older ones are already crusting. Each lesion moves quickly through the stages macule, papule, vesicle, pustule and crust, and each stage lasts hours to a day or so. Because the crops arrive over several days, lesions at several different stages coexist, and lesions at several stages of evolution present at the same time are usually enough to make the diagnosis.
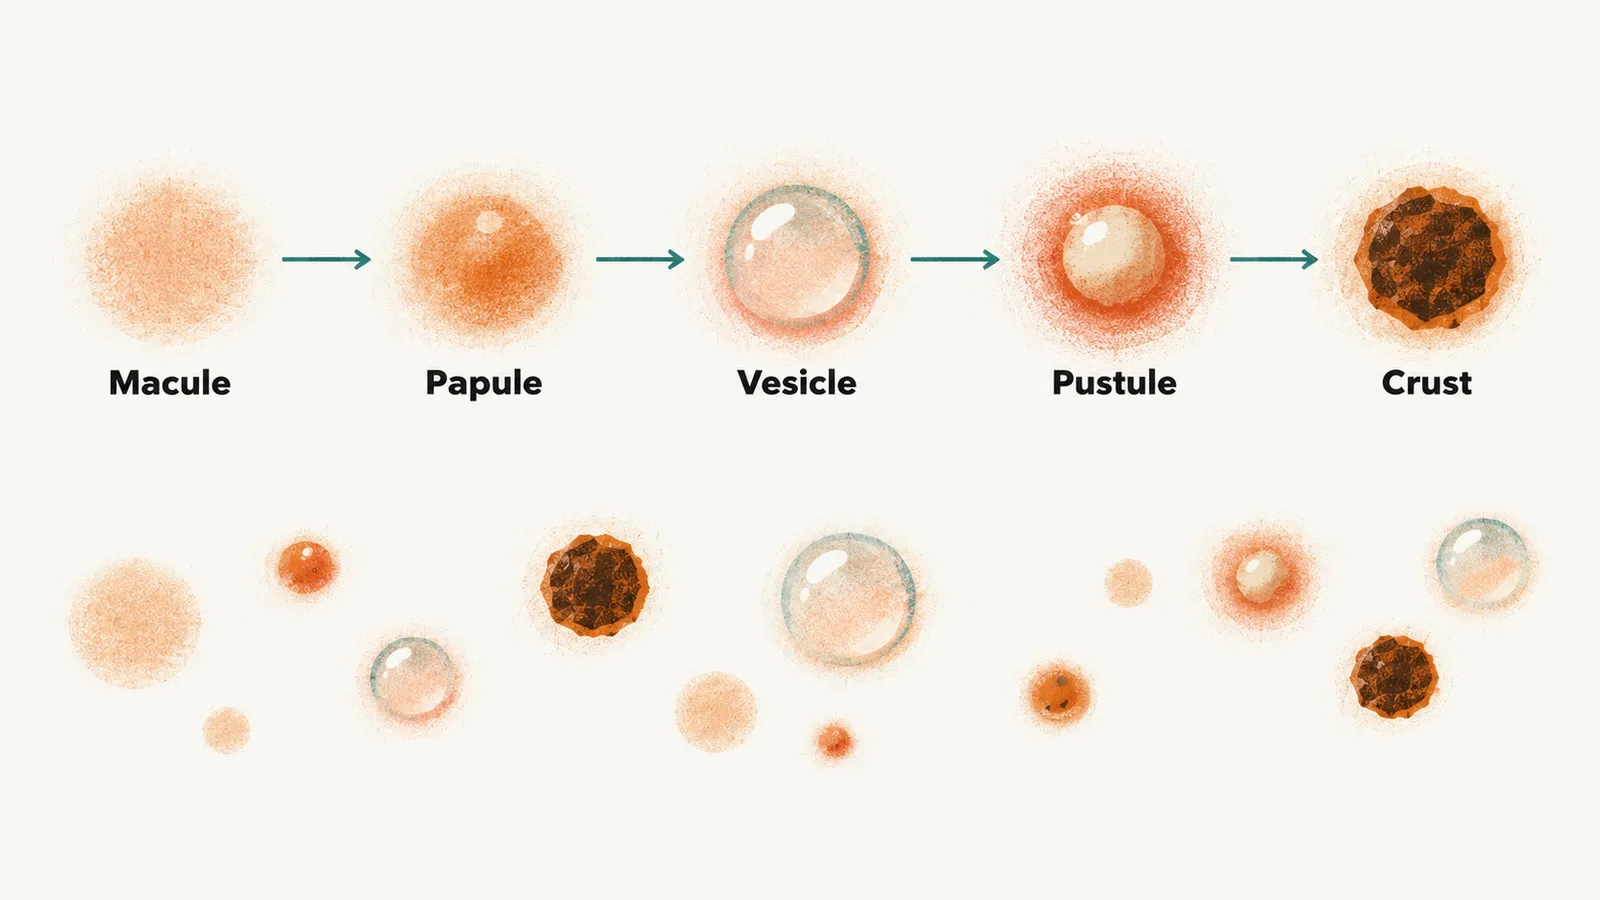
The rash is intensely itchy. It begins centrally, on the head and trunk, and is more concentrated on the trunk than on the limbs, a centripetal distribution. Vesicles may also appear on mucous membranes, including the palate and pharynx. Crusting usually begins within about 5-7 days of rash onset.
Coexisting stages separate varicella from other vesicular eruptions such as insect bites, herpes simplex and eczema herpeticum. In those eruptions the lesions tend to be synchronised.
Who needs an antiviral, and what does everyone get?
Most children recover on their own, so the question is who is at risk of more severe disease. In immunocompetent, otherwise healthy children older than 28 days, antiviral treatment is not normally required: the illness is self-limited with a good outcome, and antivirals do not change that enough to justify them.
Oral aciclovir is considered for children at risk of more severe disease:
- older than 13 years, unvaccinated, presenting within 24 hours of rash onset
- concurrent severe skin disease, such as eczema
- chronic pulmonary disease: cystic fibrosis, chronic lung disease, asthma requiring inhaled corticosteroids, interstitial lung disease
- taking aspirin, which is linked to after varicella
- currently receiving short courses or intermittent oral corticosteroids (for example 1-2 mg/kg prednisolone for wheeze or an asthma exacerbation)
The typical oral regimen in children aged 29 days to 12 years is aciclovir 20 mg/kg per dose four times daily for 5 days. Doses and durations in other age groups are age-dependent and follow the local formulary. Aciclovir works best when started within 24 hours of the rash appearing.
Intravenous aciclovir is used for:
- neonates under 7 days old
- immunocompromised children
- children who continue to develop new crops of lesions beyond 5 days
- children admitted with viral or serious bacterial complications
Symptomatic care matters as much as the antiviral decision:
- paracetamol for fever
- an oral antihistamine for itch
- short nails and loose clothing, to reduce scratching and secondary infection, because scratching opens the skin to bacteria
- adequate fluid intake
NSAIDs such as ibuprofen are contraindicated in varicella because of an association with severe skin and soft tissue infection. The association comes from an observational study, and a proposed explanation is that NSAIDs inhibit neutrophil function and so weaken the defence against infection.
Families are told to return if fever recurs or persists beyond day 3 of the rash, which points to a bacterial complication; if new lesions keep appearing beyond day 5, which means the crops are continuing; or if respiratory or neurological symptoms appear.
Which complication matters, and for whom?
Which complication matters depends on who is infected. The commonest complication can affect any child who scratches, while the gravest complications fall on adults, immunocompromised patients, and babies whose mothers are infected in pregnancy or around delivery.
Scratching opens the skin and lets bacteria enter the lesions, so secondary bacterial infection (impetigo, cellulitis, abscess) can affect any child and is the commonest complication. Persisting or recurring fever is the sign to suspect it.
Varicella pneumonia occurs far more in adults and immunocompromised patients than in children, and carries high mortality in adults. The neurological complications are less common. Cerebellar ataxia (unsteady, uncoordinated movement) is uncommon, occurs in young children, is post-infectious and is usually self-limited. Encephalitis is rare and may be direct viral or post-infectious.
The complications that depend not on the child’s skin but on timing are those of the baby whose mother has varicella, which comes next.
What happens when the mother has varicella around pregnancy or delivery?
Two different problems arise when the mother has varicella in pregnancy or around delivery, and timing explains both.
Neonatal varicella occurs when the mother develops the rash from 5 days before to 2 days after delivery. In that window the baby is exposed to a high viral load but has not yet received protective maternal antibody. Roughly 20-50% of exposed newborns develop varicella. The risk of death is low when the newborn’s rash starts in the first 4 days of life, and rises to around 20% when it starts between 5 and 12 days. Without treatment, historical case fatality approached 30%. Newborns in this exposure window are treated with varicella-zoster immunoglobulin, which is ready-made antibody against the virus and supplies what the baby lacks. If they develop disease, they are treated with intravenous aciclovir.
Congenital varicella syndrome follows maternal infection in the first 20 weeks of pregnancy, and occurs in roughly 2% of those pregnancies. It causes cicatricial (scarring) skin lesions in a dermatomal pattern, limb hypoplasia (underdevelopment), eye abnormalities and neurological impairment, and it carries high mortality in affected infants.
How is varicella prevented, and why does it persist?
The newborn depends on protection that the mother or a vaccine can supply, and prevention is how that protection is supplied. It works at two points: routine vaccination of children, and protection of susceptible contacts after exposure.
The varicella vaccine is part of the Italian mandatory immunisation schedule, given as the combined MMRV (measles-mumps-rubella-varicella) vaccine. The first dose is given in the second year of life, with a booster at 5-6 years. As with measles, it cannot be given before the first birthday because maternal antibody neutralises it. Infants under 13 months therefore remain susceptible, and older people whose immunity has waned are a second susceptible group. That is why varicella has not disappeared despite good coverage.
After exposure, varicella vaccine given within 3-5 days may prevent illness or attenuate it in susceptible contacts who can receive it. As with measles, those who cannot be vaccinated need another route. The high-risk contacts in this group are immunocompromised children, pregnant women, neonates and preterm infants. They are offered varicella-zoster immunoglobulin, the ready-made antibody against the virus. In some situations prophylactic aciclovir is given instead, following national post-exposure guidance.
Varicella, scarlet fever, measles and the other classic exanthems each leave something behind, weeks or years later, so how does the timing of a complication point to its cause? That is the question taken up in Complications and Pitfalls of Childhood Exanthems.