
What is an exanthem, and which six are the classics?
An exanthem is a widespread eruption of the skin built from repetitive lesions: the same morphology repeated across the skin, not a solitary or localised lesion. The word comes from Greek roots meaning “to flower outwards”, which describes the appearance reasonably well. The same phenomenon on a mucous membrane is an enanthem. Exanthem and enanthem are both common in the same illness, and the enanthem is often the earlier and more specific finding, so the mouth is worth looking at.
The six classic childhood exanthems are illnesses in which the rash is the clearest, most characteristic feature, not a subsidiary finding during some other infection. Exanthems as a whole have many causes: drugs, toxins, microorganisms and autoimmune disease. The same skin response can be started by quite different triggers, so “a rash” is not yet a diagnosis.
How does an illness produce a rash?
A rash is what the skin shows when something has changed in its cells or in its small vessels. Whatever the trigger, two mechanisms produce an exanthem.
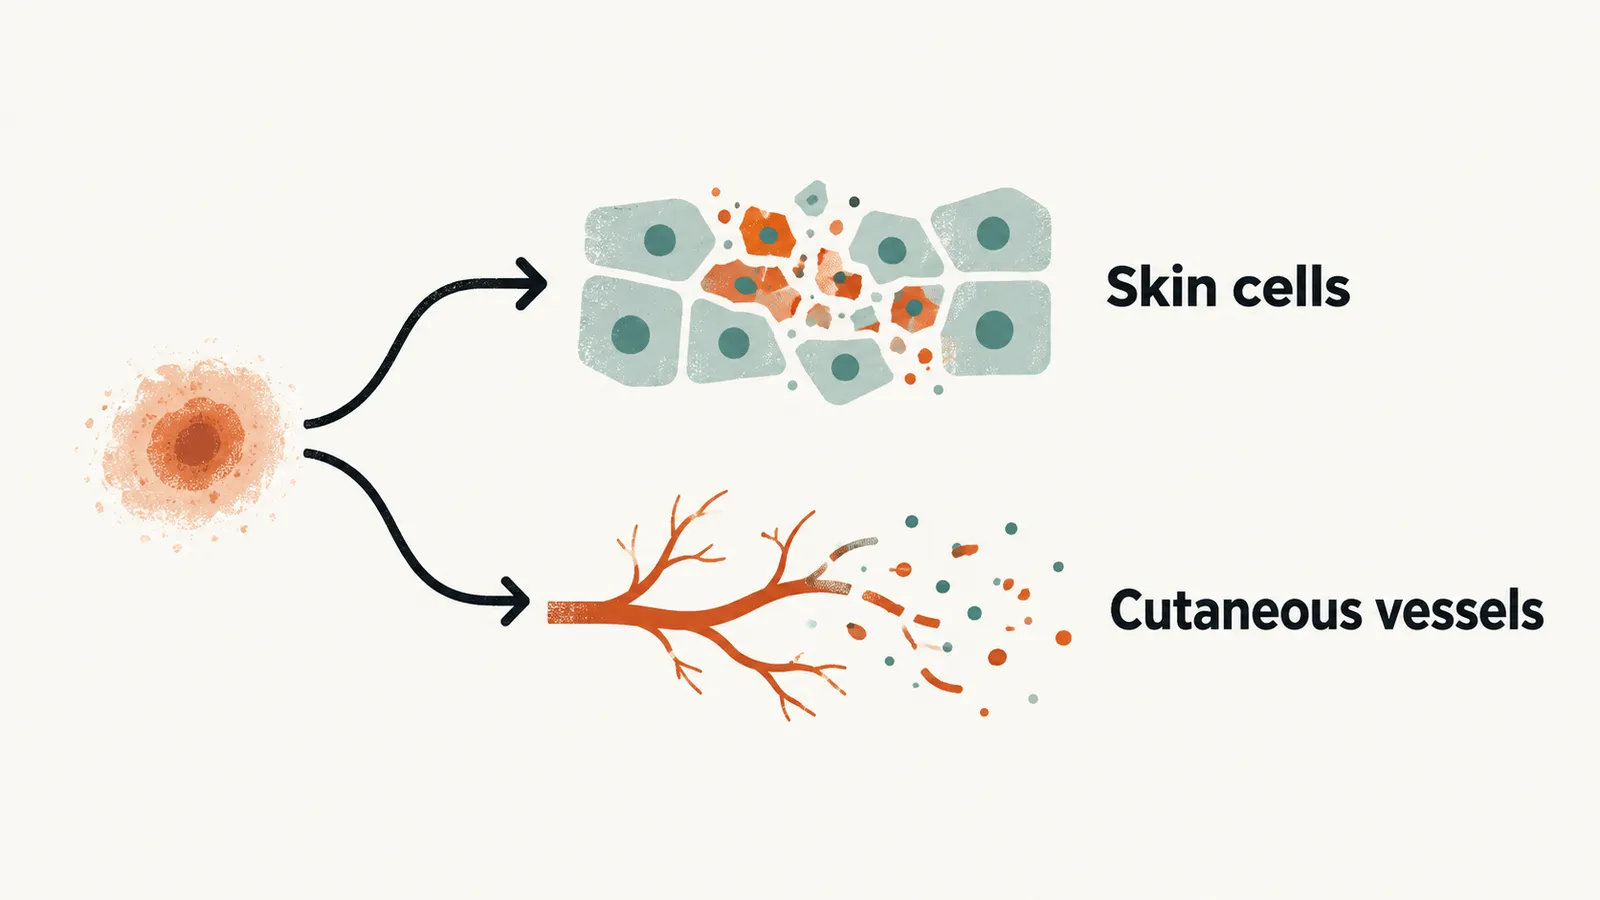
Direct damage to skin cells. The organism invades the epidermis or dermis and damages cells directly. This is the usual mechanism in viral exanthems such as measles, roseola and varicella. In these, viral replication in the skin or in the dermal capillaries produces the visible lesion, so the lesion is a local injury.
Damage to cutaneous vessels. Here the lesion comes from the small blood vessels of the skin rather than from skin cells. Damage to the capillary walls produces erythematous (reddened) lesions, and severe damage produces petechiae and ecchymoses, small and larger areas of bleeding into the skin. A vessel wall can be hit by the organism itself, by a toxin or by the immune response, and four sub-mechanisms are described:
- toxin release, as in scarlet fever (streptococcal pyrogenic exotoxin) and the staphylococcal toxin syndromes;
- immune-complex deposition or a cell-mediated response, as in vasculitic exanthems;
- direct damage by the microorganism, as in meningococcal petechiae;
- infiltration by phagocytes and lymphocytes, as in rickettsial infections.
Fifth disease belongs in this vessel-damage group as well. Its rash is thought to be immune-mediated, through immune-complex deposition, rather than the result of viral invasion of the skin.
Why does it matter where the organism is?
The two mechanisms are easiest to see when the organism and the rash are in different places, and scarlet fever shows this. The streptococci are in the pharynx, not in the skin. The rash is an immune reaction to a circulating exotoxin, a toxin the bacterium releases. Infection and rash are linked by that blood-borne toxin, so the rash appears after the pharyngitis has been present for a day or more. Whether the rash appears depends on the immune response to the toxin rather than on the severity of the infection.
How is a rash described?
Whichever mechanism is at work, a rash is described by naming the primary lesion it is built from, and each lesion type points to a process in the skin. Flat lesions come from vasodilatation. Raised lesions come from oedema or cellular infiltration. Bleeding into the skin comes from fragile capillaries, broken vessels or a coagulation abnormality.
| Lesion | Process |
|---|---|
| Erythema | Vasodilatation |
| Macule (flat) | Vasodilatation |
| Patch | Vasodilatation or pigment accumulation |
| Papule (raised) | Oedema and cellular infiltration |
| Plaque | Confluence of papules |
| Nodule | Inflammatory infiltration of the deepest dermal layers |
| Vesicle | Cellular necrosis with intra- and intercellular oedema and acantholysis (loss of adhesion between epidermal cells) |
| Bulla | A larger vesicle |
| Pustule | A pus-filled lesion |
| Crust | Dried exudate from a previous lesion |
| Scale | Parakeratosis (retained nuclei in the outer horny layer) and dyskeratosis (abnormal keratinisation of individual cells) |
| Wheal | Oedema |
| Petechiae | Bleeding from dermal capillaries, from fragility or a coagulation abnormality |
| Ecchymosis | Subcutaneous blood collection from a broken vessel or coagulopathy |
Which lesion types do the six classics have?
Grouping the lesions by the dominant type gives three morphological classes: maculopapular, vesicular and haemorrhagic. The six classics fall very unevenly among them.
A maculopapular exanthem is made of macules and papules, flat and raised lesions. Five of the six classics are maculopapular, so macules and papules recur throughout the group. This pattern narrows the diagnosis little, because many other conditions also cause a maculopapular exanthem:
- dengue, Epstein-Barr virus, cytomegalovirus, HIV, rickettsial infections, typhoid, secondary syphilis and enteroviral illness;
- drug reactions and fungal disease.
Vesicles define varicella, the only classic in the vesicular group. Other vesicular eruptions are herpes zoster, herpes simplex and hand-foot-and-mouth disease, so several infections can look alike.
Morphology therefore does not belong to the six alone: maculopapular rash has many causes, and varicella is not the only vesicular eruption.
Which rash is not one of the classics?
One class has no classic member. None of the six is primarily built from petechiae or ecchymoses, so these lesions point away from the classics, and no classical childhood exanthem is primarily haemorrhagic. A haemorrhagic rash means petechiae that do not blanch, or ecchymoses. Bleeding into the skin points to damage of the vessels themselves, and several of the conditions that cause it are dangerous. A haemorrhagic rash in a febrile child should therefore be treated as an emergency and investigated for invasive bacterial infection (meningococcal disease above all), severe measles, haemorrhagic fever or coagulopathy. It should not be filed alongside the six classics.
The six classics in one table
The six share little beyond a prominent rash. They differ in pathogen, dominant lesion, typical age and whether a vaccine exists, so they are easiest to compare side by side. The numbering is historical. In the sequence still taught in some European curricula, rubella is the third classic and the fourth slot is vacant. MMR is the combined measles-mumps-rubella vaccine, and MMRV adds varicella.
| No. | Disease | Pathogen | Dominant lesion | Typical age | Vaccine |
|---|---|---|---|---|---|
| 1 | Measles | Measles virus (Paramyxoviridae, RNA) | Maculopapular | Any unvaccinated age | MMR |
| 2 | Scarlet fever | Streptococcus pyogenes (group A strep), exotoxin-mediated | Maculopapular | School-age children | None |
| 3 | Rubella | Rubivirus (RNA) | Maculopapular | Any unvaccinated age | MMR |
| 4 | Historical: Duke’s disease, no longer accepted | ||||
| 5 | Fifth disease (erythema infectiosum) | Parvovirus B19 (DNA) | Maculopapular | School-age children | None |
| 6 | Roseola infantum | Human herpesvirus 6 (DNA) | Maculopapular | 6 months to 2 years | None |
| Unnumbered | Varicella (chickenpox) | Varicella-zoster virus (DNA) | Vesicular | Any unvaccinated age | Varicella or MMRV |
What else belongs in the same differential?
Because the lesion type is not unique to the six, other conditions sit in the same differential of a febrile rash. They have different mechanisms and management, and topics of their own:
- Hand-foot-and-mouth disease (coxsackievirus): vesicular lesions on the hands, feet and oral mucosa in young children.
- Erythema multiforme: target lesions, with concentric rings of colour, usually post-infectious or drug-related.
- Kawasaki disease: a polymorphous rash with fever for 5 days or more, with mucocutaneous changes, cervical lymphadenopathy and extremity changes. Coronary artery involvement is the risk.
- Epstein-Barr virus infection: a faint maculopapular rash, classically intensified after amoxicillin or ampicillin.
- Drug eruptions: morbilliform (measles-like) or targetoid, occasionally progressing to mucosal involvement and epidermal detachment.
With so many causes, and with five of the six looking alike, how does a clinician narrow down which illness a child has?