Pediatric oncohematology is the part of pediatrics that deals with cancers of the blood and lymphoid system in children and adolescents.
Childhood cancer is not adult cancer on a smaller scale. Childhood tumors are more often embryonal, which means they are built from immature precursor cells rather than from mature tissue. They arise from different cell populations, and they carry different recurrent genetic lesions. They also respond to treatment that adults tolerate far less well.
Two families, opposite in shape
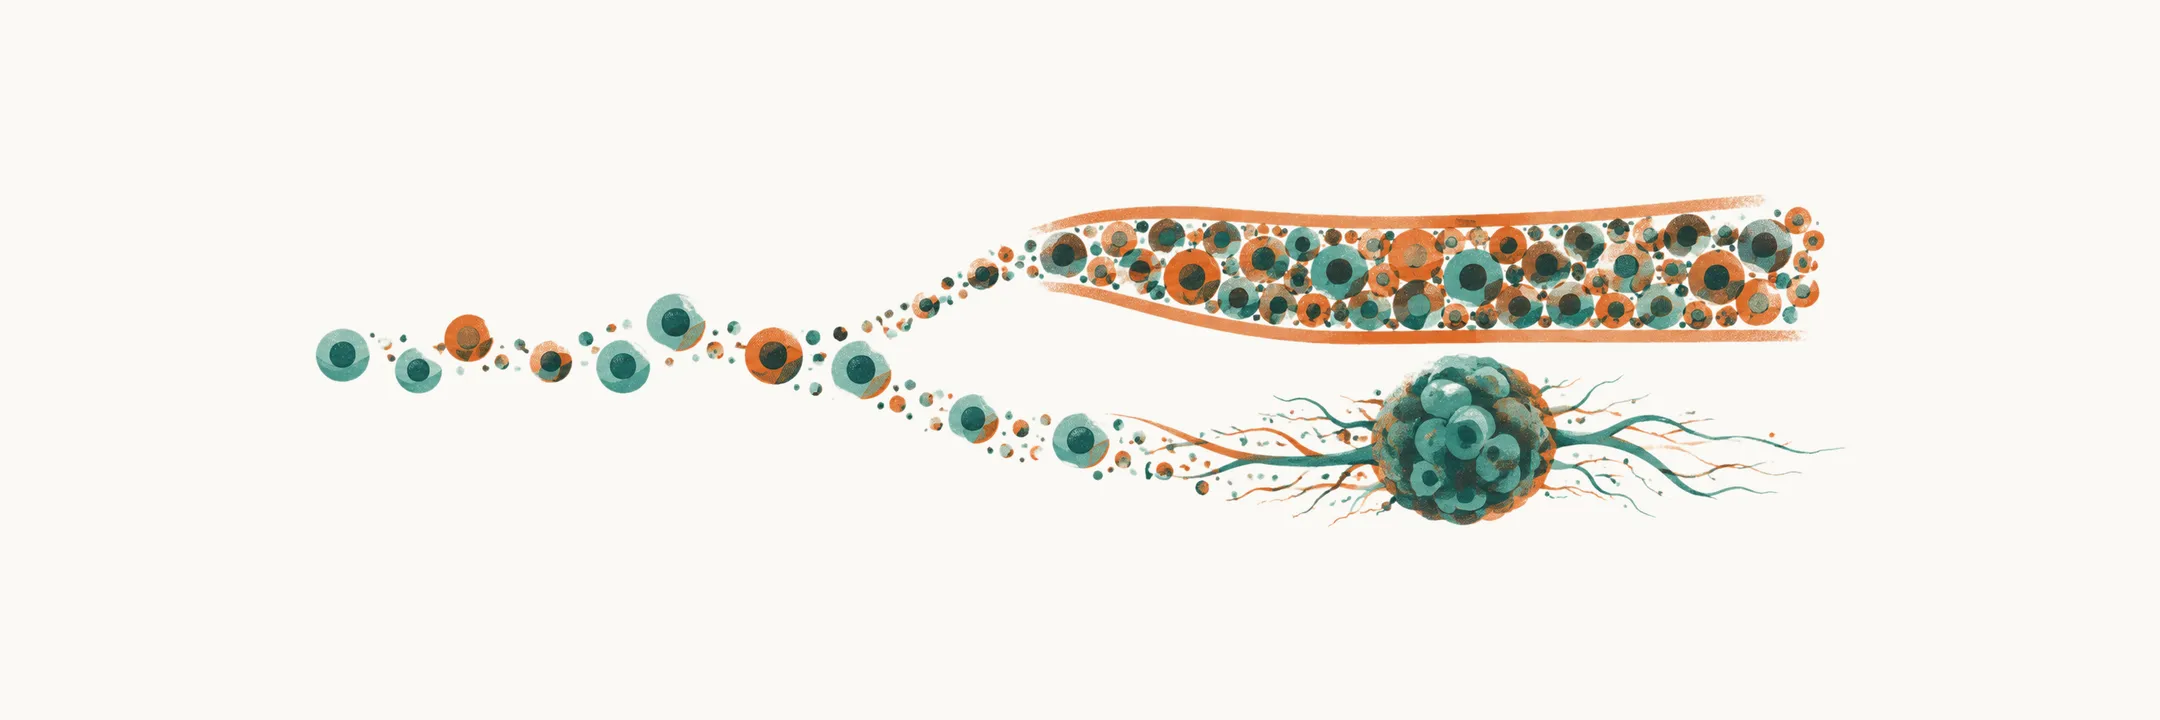
Two disease families carry most of the teaching, and they are opposites. What kind of cell is stuck, where does it sit, and what does that do to the child?
In leukemia, the cell fills the marrow. Leukemia is a clonal disease of the bone marrow: its cells all descend from one transformed cell. Immature precursor cells called blasts multiply and displace normal blood-cell production.
In an embryonal solid tumor, the immature cells form a mass. Neuroblastoma, a tumor of the developing sympathetic nervous system, is the clearest example in early childhood.
Leukemia takes up most of the subject. The commonest leukemia in children is acute lymphoblastic leukemia (ALL), and it takes up most of the leukemia material.
The notes and what each explains
The leukemia notes run in this order: the disease itself, then ALL treatment, then what treatment leaves behind, then newer agents designed to reduce that burden, then the myeloid leukemias.
- Leukemia in Children: Definitions, Presentation, Diagnosis, and Prognosis explains what leukemia is, how acute leukemias are classified, why the presenting signs come from the marrow, how the diagnostic workup is built, and why the prognosis is much better than in adults.
- Treating Childhood ALL — the BFM Backbone, Risk Stratification, and Measurable Residual Disease explains the four phases of the standard Berlin-Frankfurt-Münster (BFM) chemotherapy backbone, how risk groups are assigned, and what the current protocol generation is trying to change.
- Late Effects of Childhood ALL Therapy explains four drug-class associations with problems that appear years after treatment, and how common they are. It also shows why survivorship is clinical care rather than a follow-up appointment.
- Novel Therapies in Childhood ALL: Blinatumomab, CAR-T Cells, and Bortezomib explains why these three agents were introduced and how each works. They share a side-effect profile that reveals the immune system being redirected against leukemia.
- Childhood Acute Myeloid Leukemia explains how acute myeloid leukemia (AML) is told apart from ALL, what the AML treatment backbone is, and why Down syndrome changes the treatment a child can be given.
- Acute Promyelocytic Leukemia in Children explains the subtype defined by a single fusion protein, the product of two genes joined by a chromosomal translocation. APL is treated by a different logic altogether: the leukemic cells are made to mature. It is dangerous through bleeding before treatment starts.
- Neuroblastoma stands outside the leukemia sequence because it is a solid tumor with its own biology. It explains this embryonal tumor of the sympathetic nervous system, its age-dependent behavior, the MYCN oncogene, the staging systems, and the clinical signs that point to the diagnosis.
- Oncologic Emergencies in Children explains that both families, and their treatment, can produce acute complications that become life-threatening within hours: tumor lysis syndrome, leukostasis, mediastinal mass compression, spinal cord compression, the coagulopathy of APL, and febrile neutropenia.
Where to start
Start with leukemia in children. It establishes the vocabulary that every other leukemia note assumes: acute versus chronic, lymphoblastic versus myeloid, blasts and marrow failure. The leukemia notes then read in the order given above: treatment backbone and what it leaves behind, newer agents displacing part of it, AML, then APL.
Neuroblastoma depends on none of the leukemia notes and can be read at any point. The emergencies note is a destination rather than a starting point, because it gathers acute complications that any of these diseases can produce.
What is not covered
Leukemia and neuroblastoma are the core of the subject, but only part of pediatric oncology. Not covered are:
- Pediatric lymphoma, although it is a cancer of the lymphoid system.
- Other childhood solid tumors: Wilms tumor and other renal tumors, retinoblastoma, bone and soft tissue sarcomas, and pediatric brain tumors. Each has its own diagnostic pathway and treatment framework.
- Non-malignant blood disorders that present with similar findings: iron-deficiency and other anemias, thalassemia, sickle cell disease, immune thrombocytopenia, and bone marrow failure syndromes.
- The general supportive and palliative care framework, including transfusion practice for immunocompromised children.
So when a child has leukemia, what has gone wrong in the marrow, and how does it show on the first day?