Childhood ALL is the most common childhood cancer. In it, immature lymphoid precursors, the blasts, displace normal blood-cell production. Cure comes from a fixed combination of drugs, given in sequence. Two ideas organise everything that follows. The first is that the program, the backbone, is the same for every child. The second is that how hard the backbone is pushed is not the same, because that depends on the risk group assigned at diagnosis and on the early response to treatment.
The treatment is combination chemotherapy delivered in protocol phases. Parts of it follow from the biology of the leukemic cell. Other parts follow from where the cell hides, and from how quickly a particular clone responds.
What is the treatment built on, and where did it come from?
In the 1940s Sidney Farber reasoned that folic acid would help children with leukemia, because folic acid was known to drive marrow recovery in malnourished patients. The opposite happened: folate appeared to accelerate the leukemic process. A rapidly dividing clone needs folate to make the building blocks of DNA, so more folate can feed the disease.
That observation became a question. If folate feeds the disease, what if the supply is cut off? The antifolate aminopterin produced the first temporary remissions in childhood acute leukemia. Antifolate therapy, and then single-agent chemotherapy in general, became the platform for everything that followed.
Drugs then accumulated one at a time:
- mercaptopurine and methotrexate, in the 1940s and 1950s;
- corticosteroids, vincristine and L-asparaginase, in the 1950s and 1960s;
- cytarabine and cyclophosphamide, in the 1960s;
- anthracyclines, also in the 1960s;
- epipodophyllotoxins, in the 1970s;
- later, imatinib, clofarabine, nelarabine and .
L-asparaginase fits the same logic of starving the cell. Lymphoblasts lack asparagine synthetase, so they depend on the asparagine circulating in the blood. Asparaginase depletes it, and that selectively starves the leukemic cell.
The lasting lesson is that each new agent was inserted into a protocol backbone that already existed. It is the backbone, not the individual drug, that cures ALL.
What do the four phases do?
The BFM (Berlin-Frankfurt-Münster) backbone is built from four phases, and the middle blocks are repeated as protocol cycles. Each phase has one job.
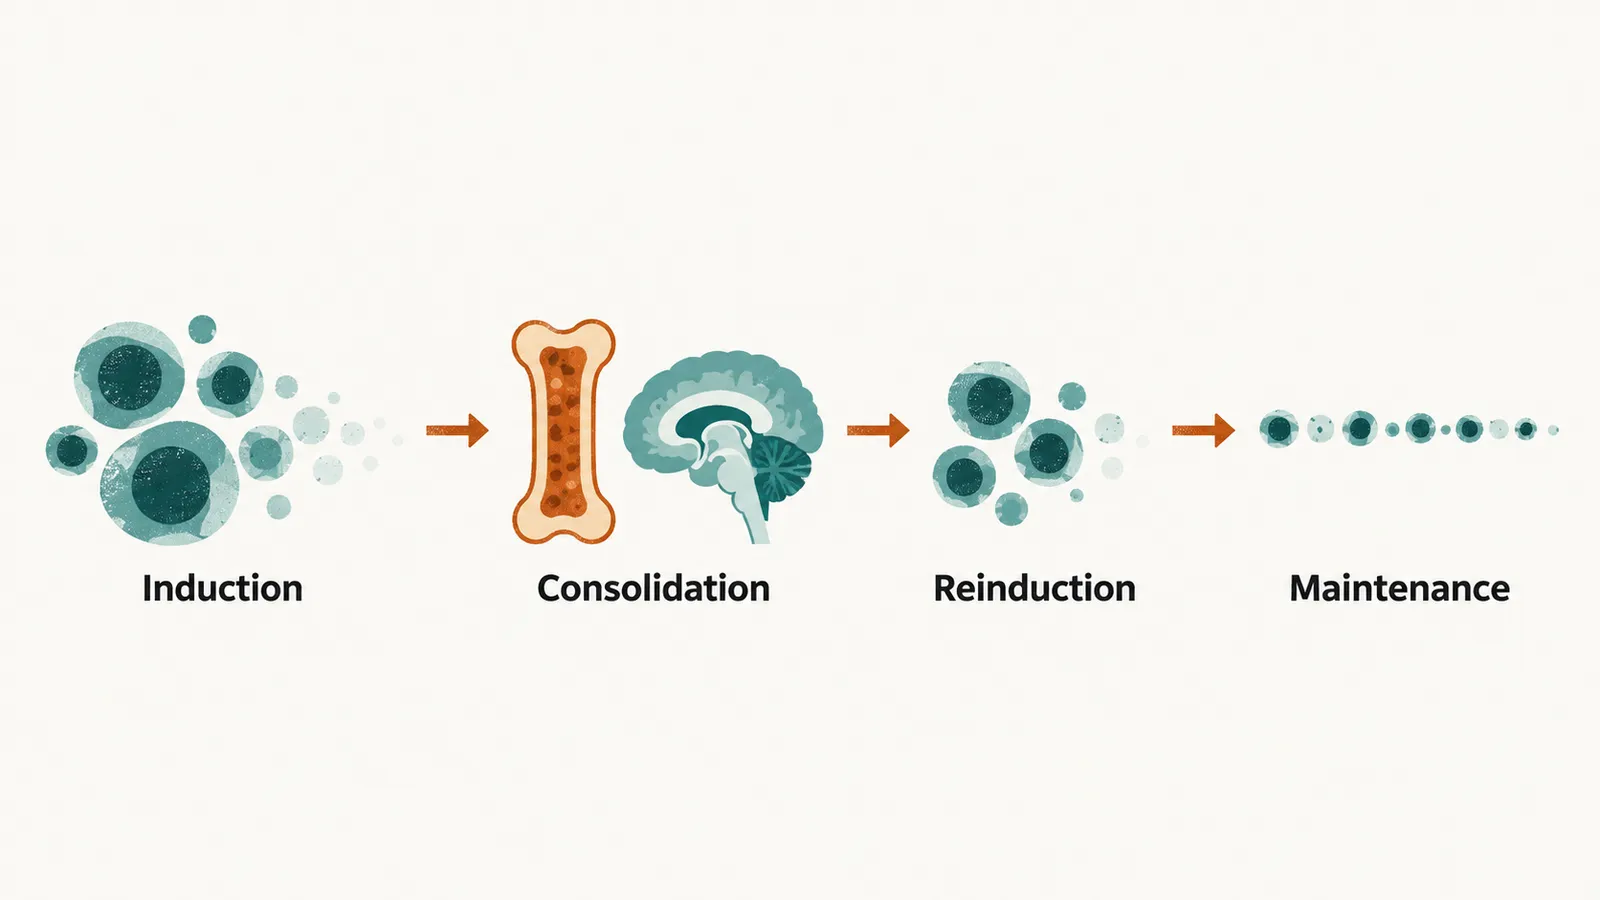
Induction (protocol IA) aims at remission. It combines vincristine, a corticosteroid (prednisone or dexamethasone), L-asparaginase and an anthracycline such as daunorubicin. Because blasts crowd out normal blood-cell production, remission means the marrow has recovered: fewer than 5% blasts and recovering peripheral counts. Remission is conventionally assessed around day 33.
Consolidation (protocol IB) aims to deepen the remission while treating the CNS. It uses cyclophosphamide, cytarabine, mercaptopurine and intrathecal methotrexate, which is methotrexate injected into the cerebrospinal fluid.
Reinduction or delayed intensification (protocol II) repeats the induction strategy with several agents added. Its aim is to attack residual disease again with a different drug combination.
Maintenance (protocol M) is daily oral mercaptopurine with weekly methotrexate, plus periodic vincristine and corticosteroid pulses. Its aim is to suppress regrowth of any dormant clone. It continues for about 2 years from the start of therapy.
Why does the CNS get its own treatment?
Consolidation treats the CNS too. That needs its own route because the CNS is reached poorly by systemically given chemotherapy. Leukemic cells there can stay out of reach of drugs that clear the marrow.
So CNS prophylaxis is delivered intrathecally, at lumbar puncture, on a fixed schedule. In BFM-based protocols the intrathecal methotrexate dose is age-banded:
- around 8 mg for age 1 to under 2 years;
- around 10 mg for 2 to under 3 years;
- around 12 mg from 3 years onward.
The bands follow age because cerebrospinal fluid volume tracks age more closely than body surface area does.
How can such a high dose of methotrexate be given safely?
Intrathecal injection is one way to reach the CNS. High-dose methotrexate is another, because a sufficiently high dose reaches the CNS from the blood. It is given at 2 or 5 g/m² per course.
Methotrexate blocks the folate pathway, in which dihydrofolate is converted to tetrahydrofolate. At this dose it would also damage normal tissue. So leucovorin (folinic acid) follows at set doses and hours after the infusion starts. Leucovorin supplies the reduced folate that methotrexate blocks, which lets cells continue past the block.
Why give it after the infusion rather than with it? Given at the same time, it would blunt the antitumor effect as well as the toxicity. Given afterwards, it makes the high dose tolerable. Normal tissues such as marrow and mucosa recover, while much of the antitumor effect is already established.
The AIEOP-BFM schedule for the 5 g/m² dose is leucovorin 15 mg/m² at hours 42, 48 and 54 after the start of the infusion. When the levorotatory form (levoleucovorin) is used, the dose is 7.5 mg/m². During the high-dose blocks, oral mercaptopurine continues at about 25 mg/m²/day.
What decides how hard the backbone is pushed?
The backbone is the same for every child, so something else must set the intensity. Measurable residual disease (MRD) has come to decide it.
By microscopy, a marrow in remission can look clear while leukemic cells remain at a depth microscopy cannot reach. Those cells can regrow. MRD is therefore the in vivo test of whether treatment is working in this child’s clone.
Two methods find those cells. In the first, each leukemic clone carries immunoglobulin and T-cell receptor gene rearrangements that are unique to it. Because every cell of the clone shares them, they act as a fingerprint and can serve as PCR targets. PCR amplifies a chosen DNA sequence until it can be detected. It can find one leukemic cell among 10,000 or more normal cells, a sensitivity better than 10⁻⁴.
In the second, flow cytometry reads the markers carried by individual cells. It is the method used for the earliest MRD timepoint.
Why trust this measurement? In the late 1990s, work showed that residual disease detectable after induction was a stronger predictor of relapse than age, white cell count or cytogenetics at presentation. Later trials confirmed the relationship at a threshold of 10⁻³, one leukemic cell in a thousand, after consolidation.
MRD is typically measured at three timepoints:
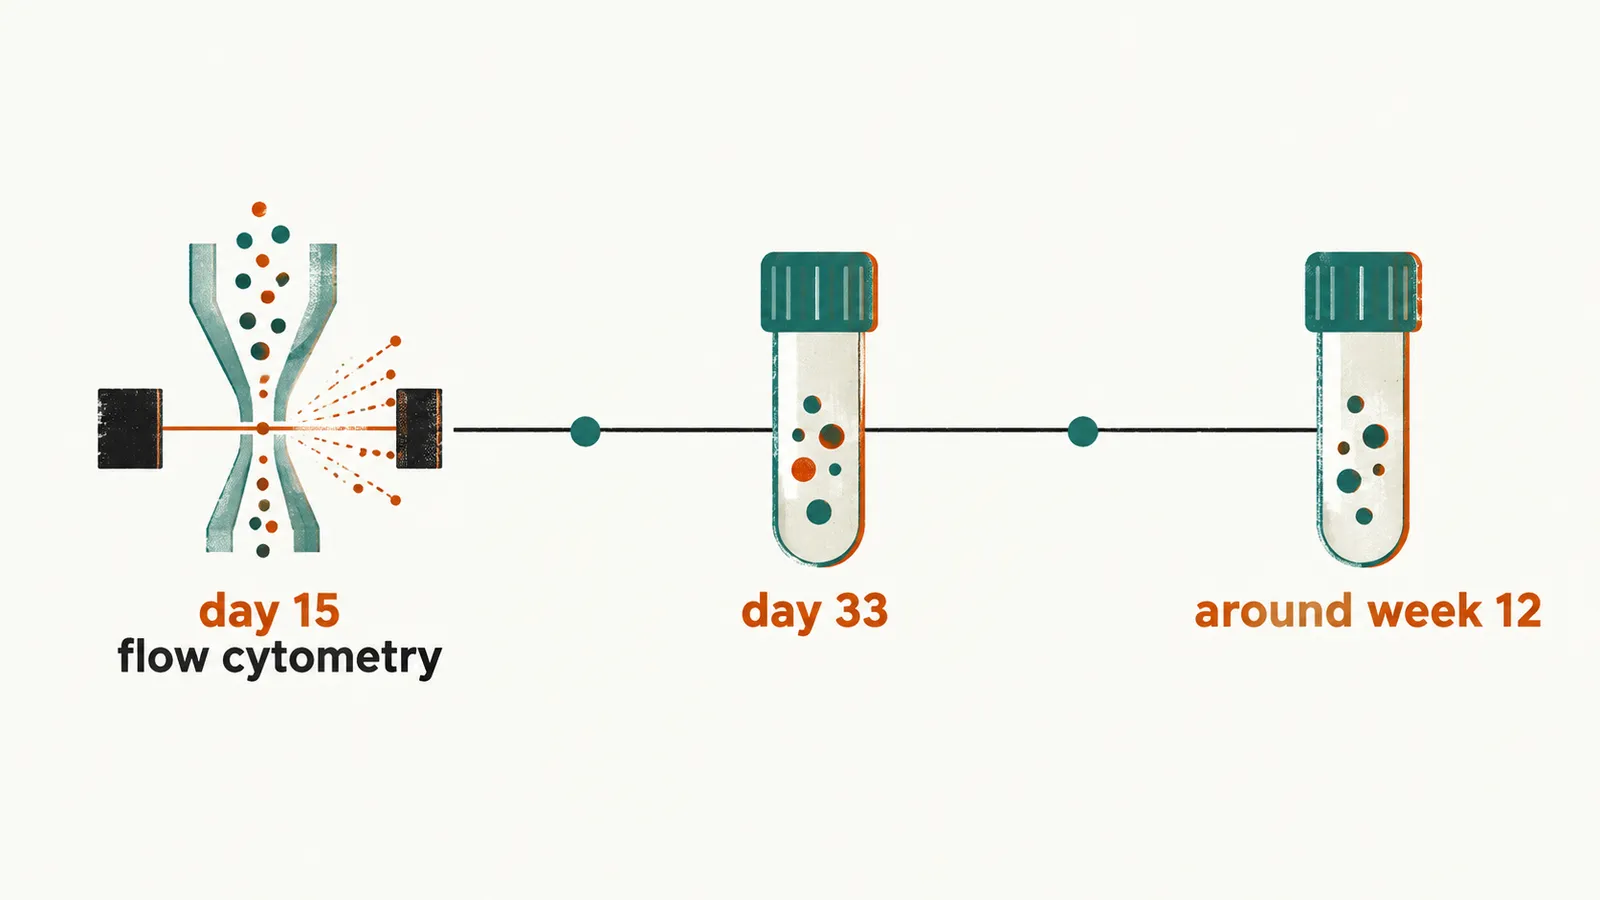
- day 15, by flow cytometry;
- day 33, the end of induction;
- around week 12, before or at the end of consolidation.
The timepoints matter because the same result means different things at different times. Children with no detectable disease do well. Children with persistent disease are intensified and considered for transplantation.
How do risk groups combine this information?
MRD is one piece of information. Modern protocols assign risk from three kinds together: baseline cytogenetics, early response and MRD. Baseline cytogenetics means the chromosomal and genetic lesions of the leukemic clone at diagnosis. Each kind sees something different: the biology at diagnosis, the speed of clearance, and the depth of the remission.
The AIEOP-BFM ALL 2000 scheme, from the joint Italian (AIEOP) and BFM trial group, defined three groups:
| Group | Definition |
|---|---|
| Standard risk | No high-risk features, and negative MRD at both timepoints |
| Medium risk | No high-risk features, but positive residual disease after induction |
| High risk | Any of the high-risk features below |
The high-risk features are different ways in which treatment can fail:
- prednisone poor response, meaning blasts persisting in the blood after the initial prednisone phase;
- BCR::ABL1-positive disease (Philadelphia chromosome);
- ;
- failure to reach remission by day 33;
- residual disease at or above 10⁻³ after consolidation.
Prednisone poor response and failure to reach remission by day 33 show slow clearance. BCR::ABL1 and KMT2A mark adverse biology. Residual disease at or above 10⁻³ shows that disease persists despite consolidation.
Within the high-risk group, sub-strata determined which children were offered allogeneic stem cell transplantation in first remission.
The 2009 revision simplified the algorithm around the same variables: lineage, high-risk cytogenetics, and residual disease measured by flow cytometry at day 15. It added hypodiploidy to the high-risk criteria.
What has changed since 2000?
The 2009 revision also changed the CNS strategy. Cranial irradiation was replaced in most children by intensified systemic cyclophosphamide and intensified intrathecal methotrexate. Prophylactic cranial irradiation was reduced to selected subgroups. Where it is still used, the dose is lower: 12 Gy instead of the historical 18–24 Gy.
Five shifts since 2000 explain most of the improvement in outcome:
- Residual disease, rather than age and white cell count alone, decides intensity.
- Cranial irradiation was replaced by intensified systemic and intrathecal therapy.
- Dedicated protocols appeared for infants and for BCR::ABL1-positive disease, with a tyrosine kinase inhibitor added to chemotherapy.
- Dexamethasone was intensified and pegylated asparaginase was introduced. PEG-asparaginase is given as 2500 IU/m² every 2 weeks in place of native E. coli asparaginase. It has a longer half-life, so asparagine stays depleted for longer between doses.
- Residual disease–based indications were set for stem cell transplantation in first remission.
What did this achieve? AIEOP-BFM ALL 2000 enrolled about 4,800 children aged 1–17 years. Reported 5-year outcomes were roughly 80% event-free survival and roughly 90% overall survival. These were an improvement on pre-2000 figures for the same disease.
What does the current protocol try to change?
With results this good, what is left to improve? The successor protocol, AIEOP-BFM ALL 2017, built on the revised residual-disease stratification. It treats early and final residual-disease results differently according to biological subgroup.
It also asks a randomized question in high-risk disease: whether two cycles of post-consolidation blinatumomab can replace two conventional high-intensity chemotherapy courses. Blinatumomab is given at 15 µg/m²/day by continuous infusion for 28 days.
The rationale is a trade-off across the field. New treatment elements are needed that reduce treatment-related mortality and morbidity while holding the cure rate.
Is cure the end of the story?
Cure is not the end of the clinical story. The drugs and intensified schedules behind these survival figures leave behind health problems that appear years later: osteonecrosis, anthracycline cardiomyopathy, secondary malignancy and thrombosis. Survivors carrying these will live with the consequences for decades. So what exactly do these treatments leave behind in a child who is cured, and why does it take years to show?