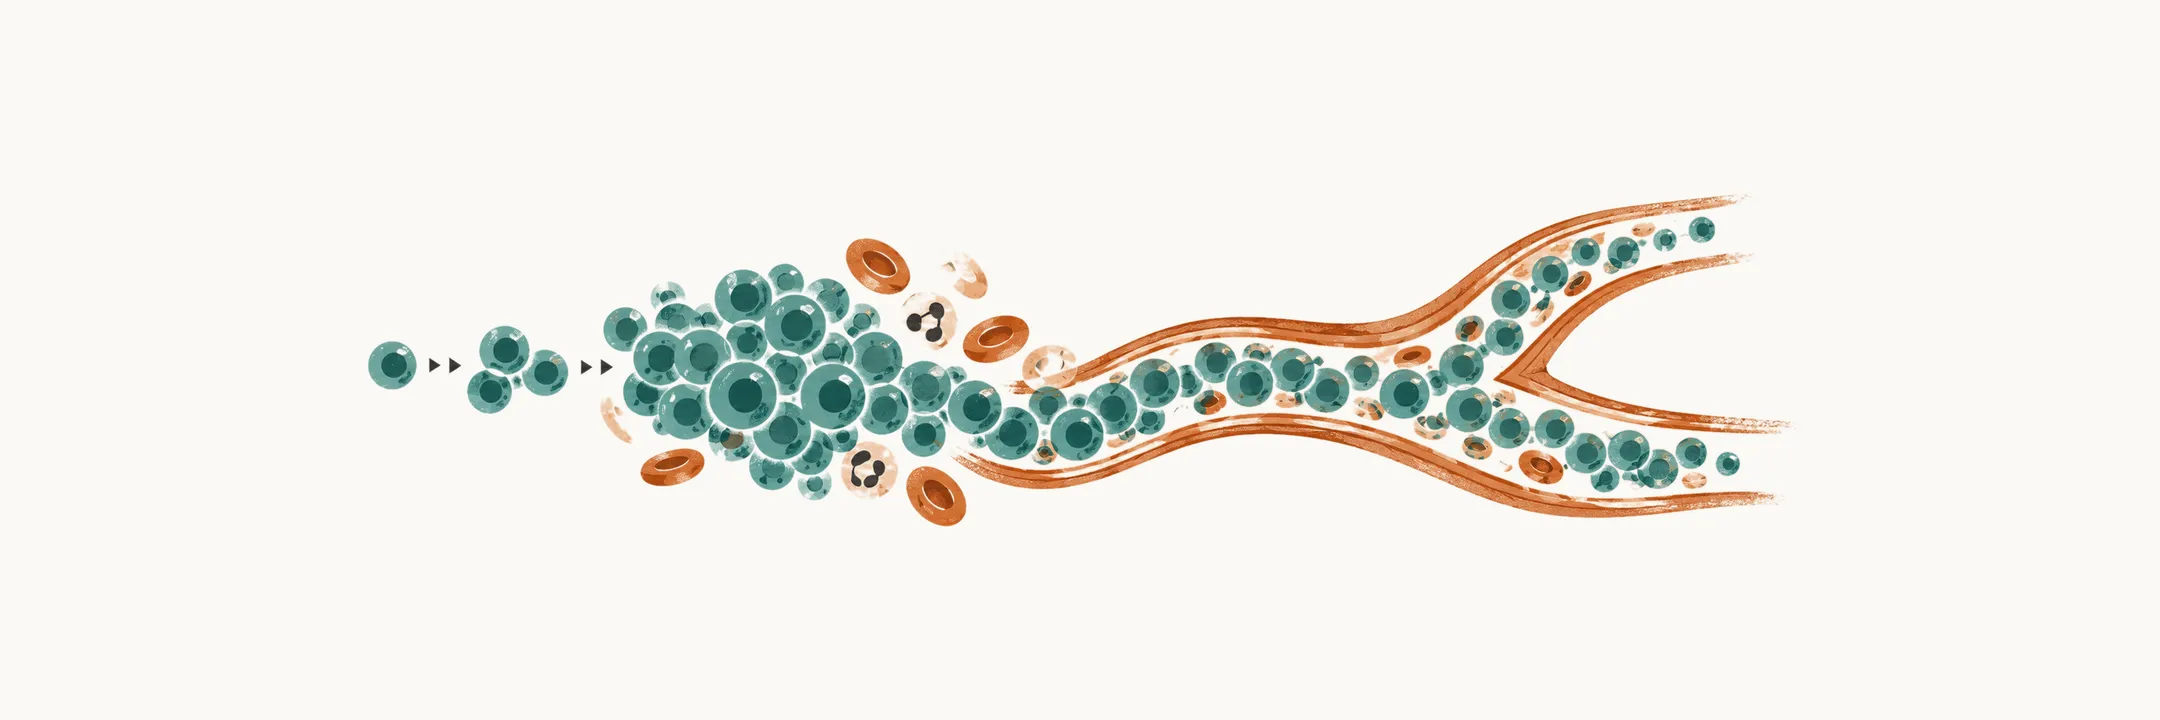
Leukemia is the malignant transformation and clonal proliferation of hematopoietic precursor cells. The precursors are the immature marrow cells that normally give rise to blood cells. Clonal means that the leukemic cells all descend from a single transformed cell.
What goes wrong in the marrow?
The bone marrow is a factory for blood cells. It starts from stem cells, and each stem cell commits to a line: a myeloid line or a lymphoid line. In leukemia, one cell in a line is transformed, and its clone fails to mature. The cells that accumulate are blasts, immature precursors arrested at an early stage.
The blasts fill the bone marrow. Because they take up the room, they displace normal hematopoiesis. They also spill into the peripheral blood, where a blood film can show them.
This one picture explains most of what follows. A marrow full of blasts makes too few normal cells, and a clone that spills into the blood can also settle in tissues. Where does this disease sit among childhood cancers?
How common is leukemia in children, and which kinds occur?
Cancer in childhood is rare, around 1% of all cancers. Even so, in high-income countries it is the leading cause of death from disease in children. Leukemia is the most common childhood cancer, roughly 30% of childhood cancers, close to one in three.
Most childhood acute leukemia is acute lymphoblastic leukemia (ALL), about 80%. Acute myeloid leukemia (AML) makes up 15–20%. Chronic leukemias are uncommon in children, so the word leukemia in a child nearly always means an acute one. In adults the picture differs: myeloid leukemias are relatively more prominent and chronic leukemias are common. In children it is the lymphoid, acute end of the spectrum that dominates.
Two further points help in practice. A high lymphocyte count in a child is far more often reactive than leukemic, and the blood film together with the rest of the count usually separates the two. And when a chronic myeloid picture does appear in a child, BCR::ABL1-positive chronic myeloid leukemia is the entity to think of.
Some children carry a higher risk from birth. Down syndrome brings a markedly increased risk of acute leukemia, and acute megakaryoblastic leukemia is over-represented. This is a leukemia of the precursors of platelet-producing cells. It is a form of childhood AML with its own biology and treatment.
If there are several kinds, how are they told apart?
Tempo and lineage: how is leukemia classified?
Leukemia is classified on two axes at once, tempo and lineage, and both carry information.
- Tempo is how fast the blasts accumulate. In acute leukemia they accumulate quickly and the illness unfolds over days to weeks. In chronic leukemia the expansion is slower and the illness unfolds over months. Almost all childhood leukemia is acute.
- Lineage is the branch the clone came from: lymphoblastic (a lymphoid precursor) or myeloid (a myeloid precursor).
Lineage decides the distinction between ALL and AML. That distinction sets the treatment backbone, and it sets the markers used to confirm the diagnosis. Lymphoblastic and lymphocytic name the same lineage, and the WHO classification calls the acute precursor neoplasms lymphoblastic. Because ALL is the most common childhood type, most of the treatment literature in this field is about ALL.
What does a child with this disease look like?
Why does a child with leukemia look the way they do?
Almost all presenting signs are consequences of a marrow full of blasts. Normal blood-cell production is crowded out, and the same clone infiltrates tissue.
The crowding-out produces three patterns:
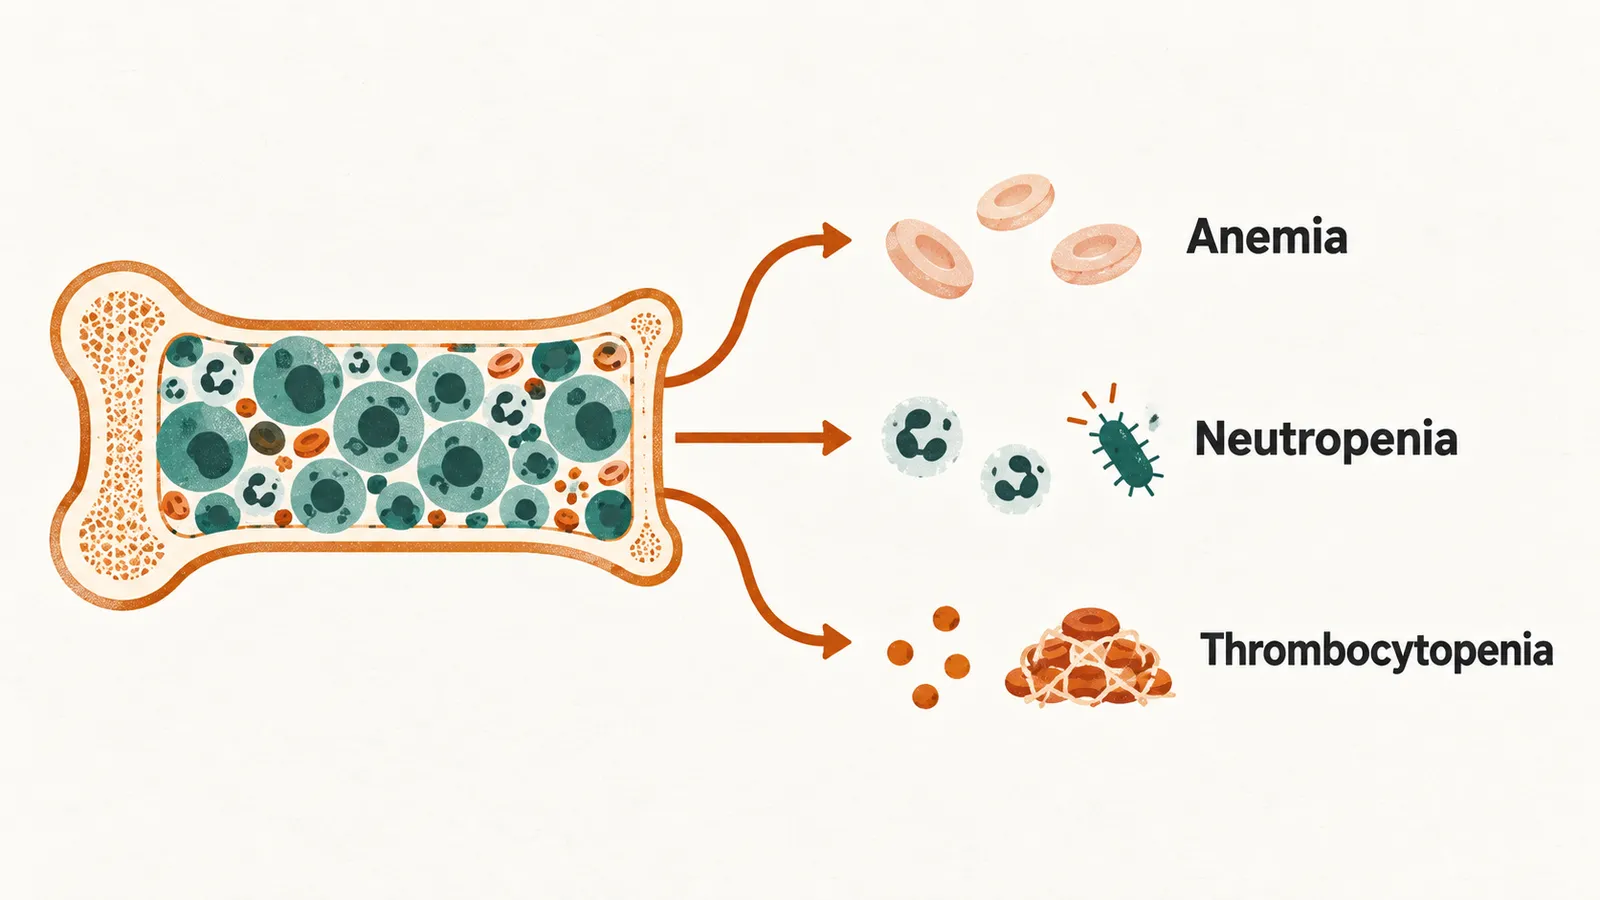
- Anemia gives pallor, fatigue, lassitude and breathlessness on exertion.
- Neutropenia gives fever and infection. The blasts are not working defenders, so a child can sometimes be ill with systemic signs that look disproportionate to the apparent source.
- Thrombocytopenia gives bruising, petechiae, mucosal bleeding and prolonged bleeding from minor cuts. Platelets stop bleeding by forming clots, so too few of them means easy bleeding.
The infiltration produces its own signs. Hepatosplenomegaly is the most common physical finding. Lymphadenopathy is also a sign, and testicular enlargement occurs in boys. Bone or joint pain can present as a limp or a refusal to walk.
The spleen and lymph nodes are not primarily diseased. They are involved by the same clone that occupies the marrow. The marrow is where the diagnosis is made.
Infiltration can also be dangerous in its own right. Where does that matter most?
Why can T-cell ALL cause a chest mass?
ALL arises from T or B lymphoblasts in tissues that hold progenitor cells, such as the marrow and the thymus. The thymus lies in the middle of the chest. So in T-cell ALL, a mediastinal mass is the feature to keep in mind.
Such a mass can compress the trachea or the superior vena cava. A child with a wide mediastinum, breathlessness and facial or upper-limb swelling is a clinical urgency, not an outpatient referral.
How, then, is leukemia confirmed?
How is the diagnosis made?
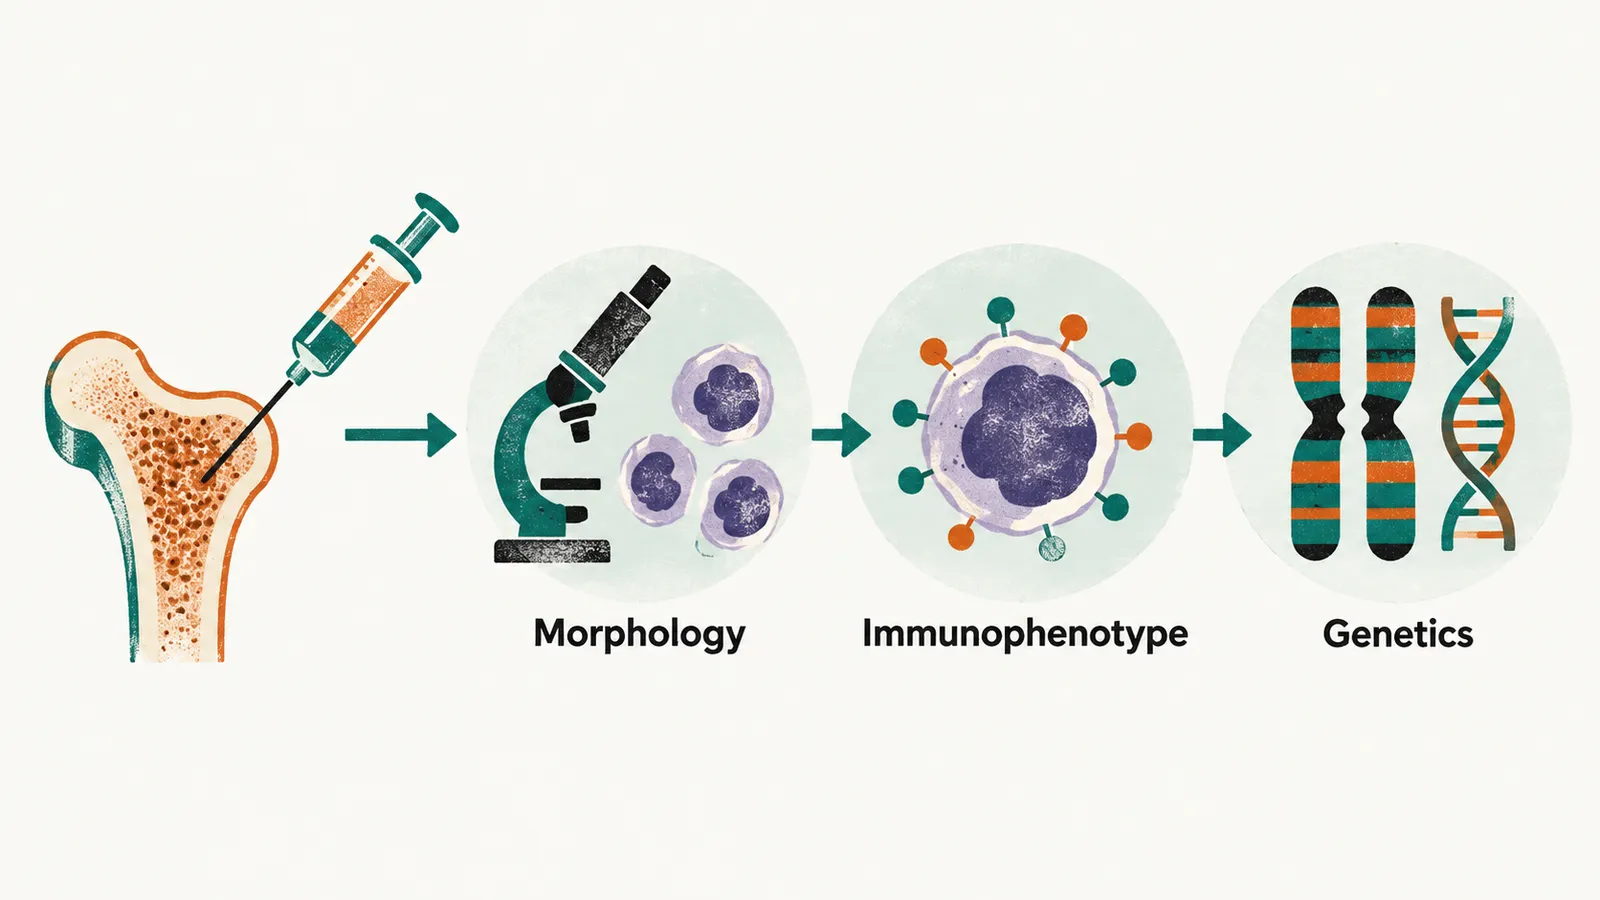
The peripheral blood count and film come first. They may be entirely suggestive: anemia, neutropenia, thrombocytopenia and circulating blasts. But the film shows only what reaches the blood, and the factory is the marrow. So a normal film does not exclude leukemia, and the diagnosis rests on the bone marrow aspirate.
One aspirate supplies three independent lines of information. The first is morphology: light microscopy describes what the blasts look like. The historical divided ALL into L1, L2 and L3 on this basis. Modern classification is biology-based. It integrates immunophenotype and genetics rather than appearance alone.
What do the other two lines add?
What do markers and genes add?
The second line is immunophenotyping by flow cytometry, which reads the marker proteins carried by individual cells. Surface and cytoplasmic markers are named by CD (cluster of differentiation) numbers.
- B-cell lineage markers: CD19, CD22, CD79a, CD10.
- T-cell lineage markers: CD2, CD3, CD7.
The markers identify the maturation stage at which the clone is arrested. On a single sample, flow cytometry distinguishes B-ALL from T-ALL from AML.
The third line is cytogenetics and molecular genetics. Recurrent genetic abnormalities define biological subtypes, they carry prognostic weight, and they increasingly determine treatment.
A blast count of 20% or more in marrow or blood is the conventional threshold for acute leukemia. The WHO classification has exceptions: certain recurrent lesions are definitional: PML::RARA, RUNX1::RUNX1T1, CBFB::MYH11 and some KMT2A rearrangements. With such a lesion the diagnosis can be made at a lower blast count, and these children are treated as acute leukemia even though the marrow looks less involved.
Which genetic findings change the outlook?
Which genetic findings change the outlook?
The genetics of the blasts is where a few findings change prognosis. A translocation such as t(12;21) involves two chromosomes, here 12 and 21. When the exchange joins two genes, the fusion gene is written with a double colon, as in ETV6::RUNX1 (formerly TEL-AML1).
This is the most frequent chromosomal alteration in childhood B-cell precursor ALL, found in roughly 20–25% of cases, and it carries a favorable prognosis. It is cryptic: the karyotype does not show it, because standard chromosome analysis looks at chromosomes and large changes, not at a swap this fine. FISH (fluorescence in situ hybridization) or molecular testing is needed to detect it.
The t(9;22) BCR::ABL1 fusion is the Philadelphia chromosome. It joins ABL1 on chromosome 9 to BCR on chromosome 22 and encodes an oncogenic protein with tyrosine kinase activity. Historically it was the worst-prognosis pediatric ALL subtype. It is now redirected to tyrosine kinase inhibitor therapy, which targets that protein, and with these inhibitors outcomes are substantially better than before the drugs existed.
Other chromosomal findings fall into two sets.
- Favorable: hyperdiploidy (more than 50 chromosomes).
- Adverse: hypodiploidy (too few chromosomes), KMT2A (MLL) rearrangement, and iAMP21 (intrachromosomal amplification of chromosome 21).
These findings matter because of what they do to the overall outlook. How good is it?
Why is the prognosis in children so good?
Contemporary protocols in children achieve of the order of 80% event-free survival, meaning alive without relapse or another defined event. Overall survival is above 90%, and some series report it in the mid-90s.
The reason is part biological and part therapeutic. Biologically, the favorable subtypes ETV6::RUNX1, hyperdiploidy and TCF3::PBX1 are common in children and rare in adults. They are concentrated in the standard-risk B-ALL group.
Therapeutically, treatment is response-adapted: intensity is assigned by baseline biology and by MRD early in therapy. The favorable group receives less treatment and so less toxicity, while high-risk children are intensified. The same features decide how much treatment each child needs, together with how quickly the disease responds to the first phase of treatment.
If these features decide how much treatment each child needs, what does that treatment consist of, phase by phase?