Neuroblastoma is a malignant embryonal tumor derived from precursor cells of the sympathetic nervous system: the adrenal medulla and the sympathetic ganglia. These ganglia form a chain beside the spine from the neck to the pelvis, and the adrenal medulla is the sympathetic tissue that makes catecholamines. So the tumor can sit anywhere along that chain or in the adrenal, and it keeps some of the habits of its tissue: it usually produces catecholamines, and it takes up mIBG.
The tumor is also a failure of maturation. Its cells should have finished developing before birth, and how far they have matured, and how abnormal their genes are, shapes how the tumor behaves. That behavior changes with the age of the child. Each section below applies this one idea: where the tumor grows decides the signs, what it secretes decides the tests, and age and biology decide risk and treatment.
What family of tumors does it belong to?
Neuroblastoma arises from embryonal sympathetic tissue, so it belongs to a family ordered by degree of cell differentiation. The more mature the cells, the more benign the tumor.
| Tumor | Differentiation | Behavior |
|---|---|---|
| Ganglioneuroma | Fully differentiated | Benign |
| Ganglioneuroblastoma | Intermediate, mixed | Intermediate |
| Neuroblastoma | Undifferentiated | Malignant |
Pheochromocytoma shares the sympathetic origin. It is a tumor of the catecholamine-secreting chromaffin cells of the adrenal medulla, and it is far more common in adults than in children.
The name follows the same convention as nephroblastoma (Wilms tumor), medulloblastoma and retinoblastoma: a malignant tumor of tissue that should have finished differentiating before birth.
Why does the same tumor regress in a baby and kill an older child?
Neuroblastoma is the most common solid tumor outside the brain in early childhood, and the most common cancer diagnosed in infancy. It behaves in ways no leukemia does. In a baby it can regress without treatment. In an older child it kills despite the most intensive therapy in pediatrics.
This is the central fact of the disease. Neuroblastoma behaves in two opposite ways depending on the age of the child. In infants under 1 year it can regress spontaneously, or differentiate into a benign ganglioneuroma, without treatment. In older children it is one of the most aggressive solid tumors in pediatrics. The same disease at the same anatomical site can be self-limited in a baby and lethal in a school-age child.
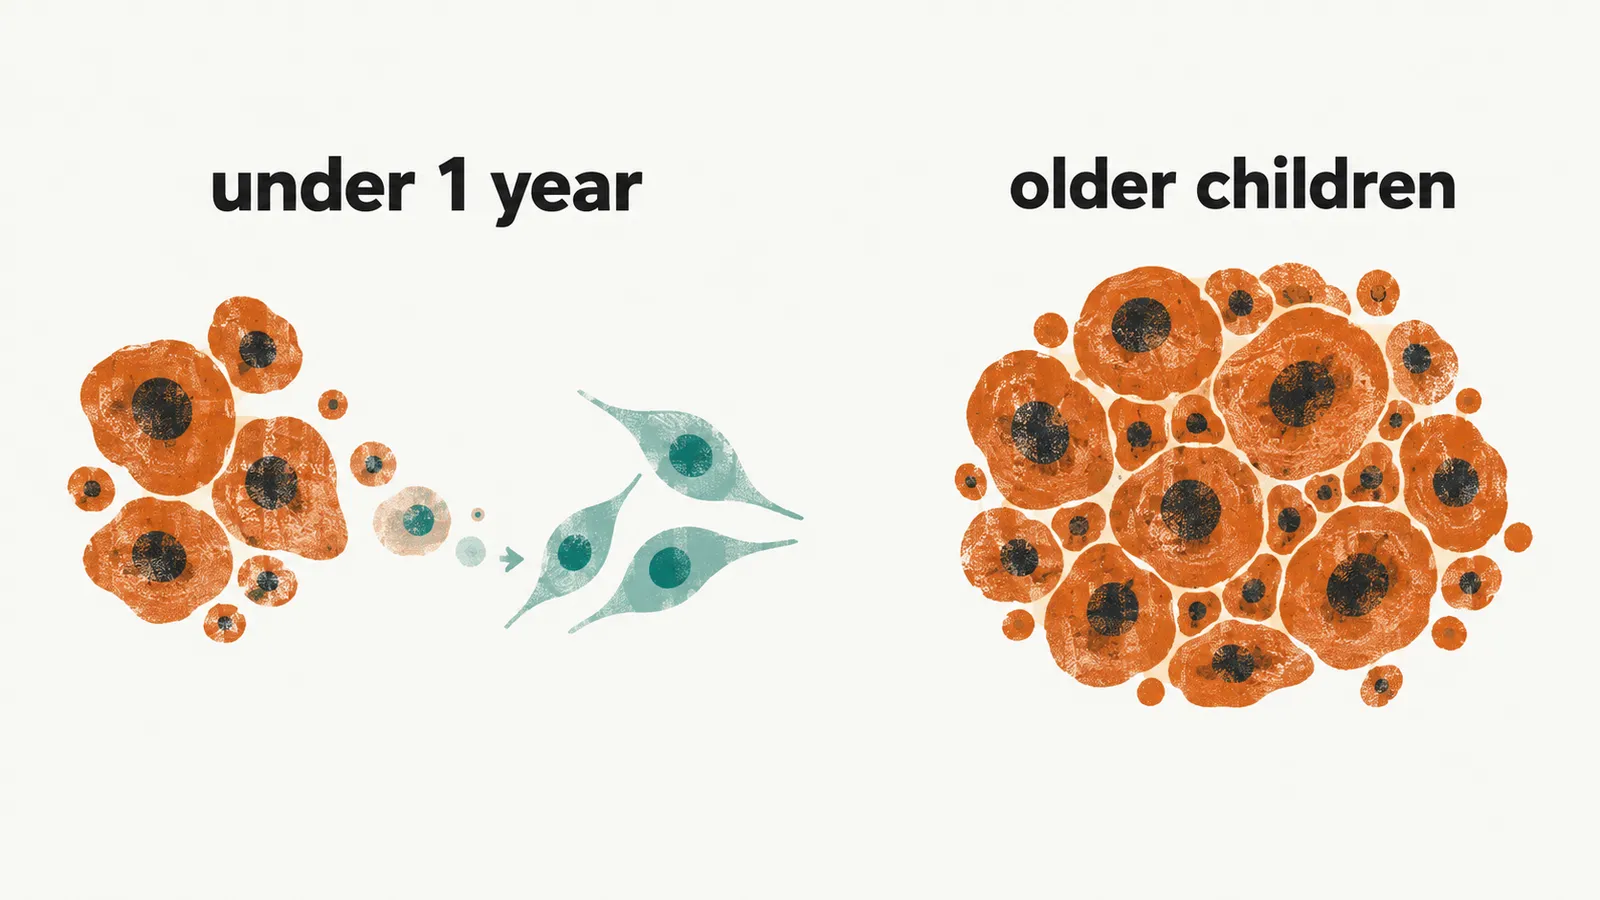
The biology of spontaneous regression is not fully established. Differences in neurotrophin receptor signaling are part of the explanation. Favorable infant tumors tend to express high levels of the nerve growth factor receptor TrkA, whereas aggressive tumors signal through other neurotrophin pathways. Immune mechanisms and telomere maintenance have also been proposed. Whatever the mechanism, age at diagnosis is one of the strongest prognostic factors, so age will return in every section that follows.
Who gets it, and when?
Neuroblastoma is roughly 7-8% of all childhood cancers, and it is the most frequent malignancy of infancy. Approximately 90% of cases are diagnosed before age 5 years, more than a third during the first year of life, and the median age at diagnosis falls in the second year. That age distribution is why an abdominal mass in a young infant should raise the possibility immediately.
How does the site decide the signs?
An abdominal mass is one way in, not the only one. Presentation depends on the primary site, on spread, and on whether the tumor secretes anything. So the signs fall into three groups: local effects, systemic effects and paraneoplastic syndromes.
Sympathetic tissue runs along the whole spine, but most tumors arise in the abdomen, and the adrenal medulla or the sympathetic ganglia there are the commonest single site. After the abdomen come the posterior mediastinum, the pelvis and the neck.
Local effects. An abdominal tumor causes distension, a palpable mass or pressure symptoms. The main alternative in the abdomen is Wilms tumor. It is renal rather than adrenal or paravertebral, and it usually presents in the preschool years. Imaging usually separates the two, and so does the tumor-marker pattern, which is described below.
A posterior mediastinal or paravertebral tumor can compress the trachea and cause cough and dyspnea. Such a tumor can also grow through an intervertebral foramen into the spinal canal. It then lies on both sides of the foramen as a dumbbell tumor, and it compresses the cord. Oncologic Emergencies in Children takes up how this is handled.
The sympathetic chain also carries the sympathetic supply of the eye. A tumor in the neck or the apex of the chest can compress the chain and produce Horner syndrome: ptosis, miosis and enophthalmos. Periorbital involvement gives yellow-brown ecchymoses known as raccoon eyes, which can be mistaken for injury.
Systemic effects. Metastatic disease is present at diagnosis in a substantial proportion of children, around 60% overall, and metastases are more common in children over 1 year. The usual sites are bone marrow, bone, liver and skin.
Marrow involvement and tumor burden produce weight loss, fever, pallor, lassitude, irritability, bone and joint pain, and cytopenias. The logic is the same as in Leukemia in Children: Definitions, Presentation, Diagnosis, and Prognosis: a tumor crowding the marrow leaves less room for normal blood cells. Bone pain can present simply as a child who will not stand or walk, a sign worth taking seriously in a toddler. Infants may present with bluish subcutaneous nodules, the blueberry muffin lesions of metastatic skin involvement.
The tumor mass and its metastases are not the whole picture, because some signs arise at a distance.
What can the tumor do from a distance?
Paraneoplastic syndromes are effects produced away from the tumor, by antibodies or secreted substances rather than by tumor mass. Two are characteristic.
Opsoclonus-myoclonus is chaotic involuntary eye movements with myoclonic jerks, often with ataxia. It is antibody-mediated. It frequently persists after the tumor is removed, leaving long-term neurological sequelae even when the oncologic outcome is good.
VIP syndrome is profuse watery diarrhea with hypokalemia. It is due to vasoactive intestinal peptide secreted by the tumor.
How, then, is the diagnosis confirmed and the disease mapped?
How is it confirmed and mapped?
A suspected neuroblastoma is confirmed and mapped with three kinds of test: tumor markers, imaging of the primary tumor, and a search for metastases.
Markers. The tumor is derived from catecholamine-producing sympathetic tissue, so it usually makes catecholamines, and their metabolites are the classic test: urinary VMA and HVA. Dopamine, epinephrine and norepinephrine are also measured in urine and plasma. They are raised in the great majority of neuroblastomas. Pheochromocytoma raises catecholamines as well, but its metabolite pattern differs. , ferritin and lactate dehydrogenase are measured too. These reflect tumor burden rather than identifying the tumor.
Imaging of the primary. CT, ultrasound or MRI localize the mass and define its relation to surrounding structures and its extension, including through the neural foramina. Neuroblastoma typically shows calcification on CT.
Search for metastases. Marrow and bone are usual metastatic sites, so the evaluation includes:
- bone marrow aspiration and trephine biopsy (a core of marrow and bone) from two sites;
- a skeletal survey or technetium-99m bone scintigraphy;
- mIBG scintigraphy with radioiodine-labelled mIBG.
Scintigraphy is imaging of a radioactive tracer after the body has taken it up. Sympathetic tissue takes up mIBG. It is the most specific functional imaging test available. It demonstrates the primary tumor, residual disease, bone marrow infiltration, and skeletal or soft tissue metastases. Where mIBG is negative or unavailable, FDG-PET is an alternative; it is positron emission tomography with a radiolabeled glucose analogue.
A test as easy as a urine sample invited an obvious idea.
Why is screening not recommended?
VMA and HVA can be measured in a urine sample, so they were the basis of mass screening programs in infancy. Screening at 6 months of age finds more neuroblastoma but does not reduce deaths from the disease. This is the age paradox again: screening-detected tumors are mostly the biologically favorable ones that would have regressed or never caused symptoms. Screening is not recommended.
There is no established way to prevent the disease, and its risk factors and causes are unknown.
Once a tumor is found, how is its extent expressed?
How is the extent staged?
Extent of disease is expressed as a stage. Two systems are in use, and they answer slightly different questions.
The International Neuroblastoma Staging System (INSS) is surgical: it describes what the surgeon found.
| INSS stage | Meaning |
|---|---|
| 1 | Localized tumor, completely excised, negative lymph nodes |
| 2A | Localized tumor, incomplete gross excision, microscopically negative ipsilateral nonadherent nodes |
| 2B | Ipsilateral nonadherent nodes positive for tumor, contralateral nodes microscopically negative |
| 3 | Unresectable unilateral tumor crossing the midline, or localized tumor with contralateral node involvement, or midline tumor with bilateral extension |
| 4 | Any primary tumor with dissemination to distant nodes, bone, bone marrow, liver, skin or other organs |
| 4S | Localized primary tumor with dissemination limited to skin, liver or bone marrow, in an infant under 1 year |
Stage 4S is the staging counterpart of the infant paradox. Metastatic disease confined to skin, liver and bone marrow in a baby under 1 year can regress spontaneously and carry a good prognosis. The same pattern of spread in an older child would be stage 4 and high risk. That is why a period of observation can be legitimate management in a carefully selected infant.
The INRGSS is newer and image-based. It stages the tumor before any surgery, so it does not depend on what the surgeon removed. It relies on image-defined risk factors: imaging features that make up-front removal of the tumor hazardous.
| INRGSS stage | Meaning |
|---|---|
| L1 | Localized disease without image-defined risk factors |
| L2 | Localized disease with image-defined risk factors |
| M | Metastatic disease |
| MS | Special metastatic category; extends the infant 4S concept to children under 18 months |
Treatment decisions in current protocols are made on INRGSS stage together with age, MYCN status and other biology. So what does the biology add?
What does the tumor’s biology add?
Risk has three elements: stage, age, and the biology of the tumor cells, read from a small set of genetic features.
MYCN is an oncogene (a gene that drives cell growth when overactive) on chromosome 2p. MYCN amplification means the tumor carries many extra copies of it. It is found in about one fifth of neuroblastomas and is an independent adverse prognostic factor. It identifies aggressive, treatment-resistant disease even in an otherwise lower clinical stage. Amplification means worse, not more treatable.
DNA ploidy is the amount of DNA in each tumor cell. Hyperdiploid or near-triploid DNA content is associated with younger age, lower stage and better outcome, particularly in infants.
Chromosome 1 shows structural and numerical changes that are common. Deletion of 1p36 is the best studied and, like MYCN amplification, is adverse.
Modern risk classification also incorporates ALK alterations, segmental chromosomal changes and other lesions. These inform prognosis and, for ALK, targeted treatment.
Age, stage and biology together place the child in a low-, intermediate- or high-risk group, and management is adapted to the group.
How does treatment follow risk?
The range of treatment is unusually wide: from observation alone to the most intensive multimodal therapy in pediatrics.
- Low risk: often cured by surgery alone. Selected infants with stage 4S or MS disease can be observed, because spontaneous regression is expected.
- Intermediate risk: surgery plus moderate-intensity chemotherapy.
- High risk: treated in several steps.
The steps for high-risk disease, in order:
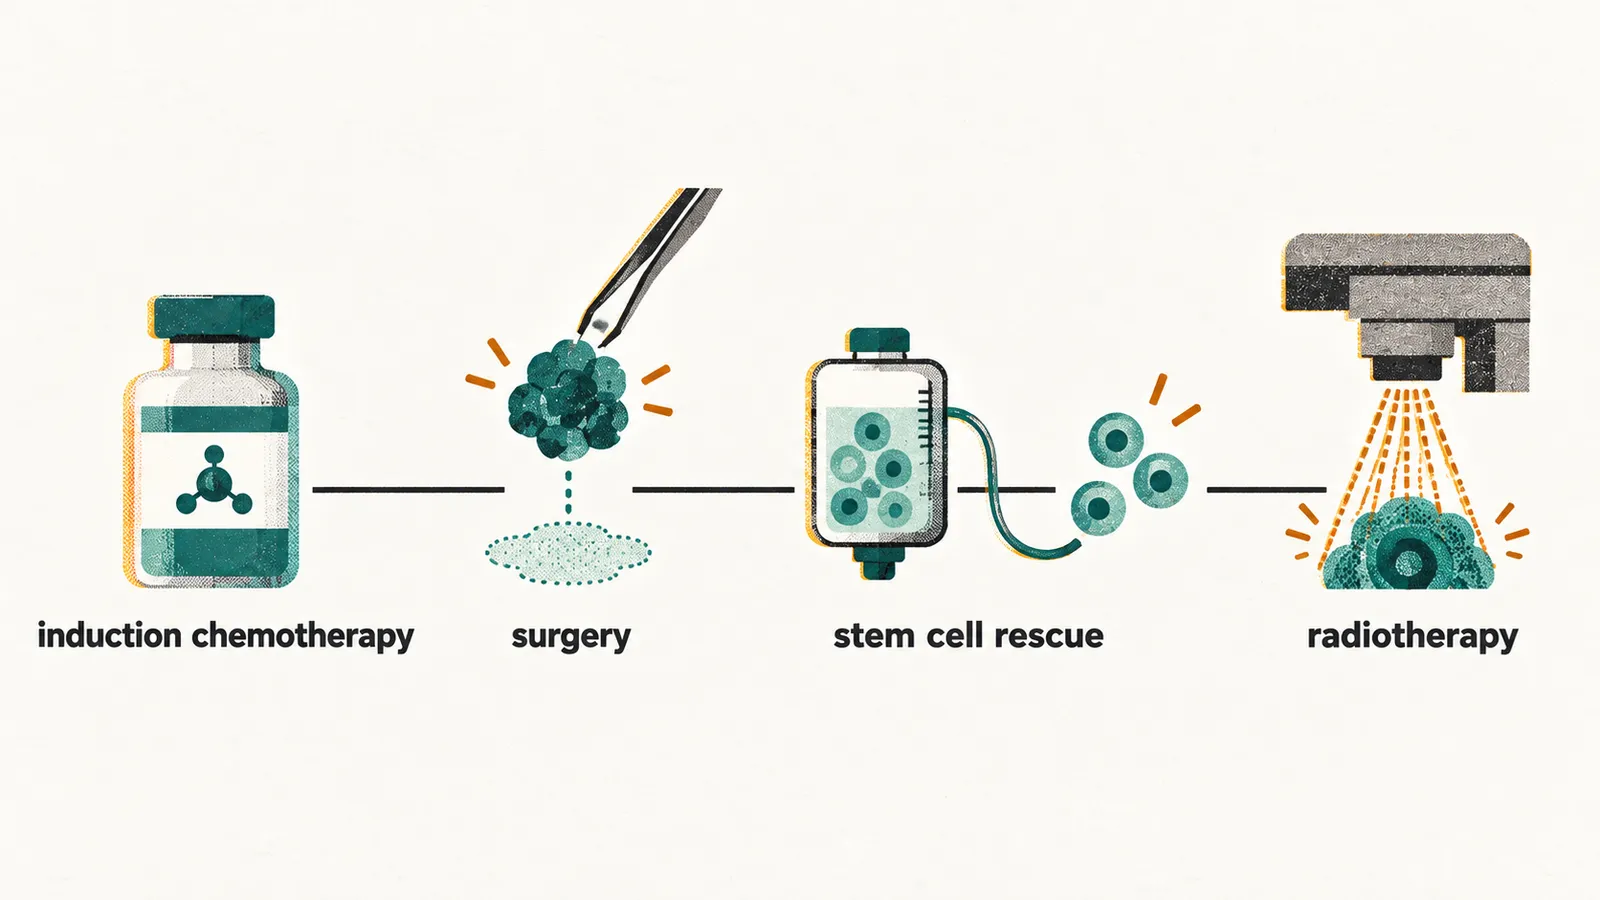
- Intensive induction chemotherapy.
- Surgery where feasible.
- High-dose chemotherapy with autologous stem cell rescue, that is, reinfusion of the child’s own previously collected stem cells.
- Radiotherapy to the primary site and to residual disease.
After consolidation, maintenance combines retinoids with anti-GD2 antibody immunotherapy. The retinoids are 13-cis-retinoic acid, and all-trans retinoic acid in some regimens. Because the tumor is a block in maturation, pushing residual neuroblasts toward differentiation is a fitting treatment. The anti-GD2 antibody is directed at GD2 on the surface of the neuroblastoma cell. Dinutuximab and naxitamab are the agents in current use, supported by GM-CSF, IL-2 and isotretinoin in the regimens that established their benefit.
Targeted radiotherapy with radioiodine-labelled mIBG is used in mIBG-avid disease, particularly in the relapsed setting; the uptake that makes the scan work carries the radiation to the tumor. ALK inhibitors have a role in ALK-altered disease.
What is the outlook?
The features that set the risk group also describe the outlook.
Favorable features:
- age under 18 months at diagnosis;
- a thoracic, cervical or presacral primary rather than an adrenal one;
- absence of lymph node involvement;
- hyperdiploidy;
- absence of MYCN amplification.
Unfavorable features: MYCN amplification, lymph node involvement, older age and high-risk image-defined disease.
Low-risk children have long-term survival of around 90%. High-risk disease remains the hard problem: despite the addition of myeloablative (high-dose) therapy, differentiation therapy and anti-GD2 immunotherapy, 5-year event-free survival in the high-risk group is roughly 50%.
What can threaten the child before staging is settled?
Risk group and survival describe the course of the disease over years. Beyond that biology, the position of the tumor decides what happens to the child. A paravertebral tumor growing into the spinal canal presents as an emergency in its own right, and so does a mass compressing the airway. Such an emergency has to be dealt with before staging and biology are settled.
When a mass presses on the cord or the airway, or a leukemia kills cells faster than the body can clear them, what has to be done within hours, before the diagnosis is complete? That is the subject of Oncologic Emergencies in Children.