Childhood ALL is a cancer of immature lymphoid precursor cells. When the precursors are of B-cell lineage, the disease is B-ALL. It is treated with a conventional chemotherapy backbone, a fixed sequence of combination-chemotherapy phases lasting about 2 years, and the backbone cures most children.
Why look beyond the backbone?
The cure has a cost: osteonecrosis, cardiomyopathy, secondary malignancy and thrombosis. These are the late effects that survivors carry for decades, and Late Effects of Childhood ALL Therapy explains them. So the question is whether part of the cytotoxic backbone can be replaced by something that kills the leukemic clone by a different mechanism.
The aim is that cumulative exposure to anthracyclines, alkylating agents and corticosteroids can come down without giving up on the cure rate. Blinatumomab, CAR-T cells and bortezomib exist for this purpose.
The backbone kills by damaging DNA or interfering with cell division. Most of these newer agents work differently: they recruit the immune system. A T cell is already a killer, and the agent tells it where to go. Blinatumomab and CAR-T cells redirect the patient’s own T cells against the leukemia. Bortezomib is the exception, because it acts on the leukemic cell directly.
This picture also explains the side effects. Because the agents work by recruiting the immune system, their side effects are mostly consequences of that recruitment.
How does blinatumomab turn a T cell on the leukemic cell?
Blinatumomab is an engineered antibody construct, a bispecific T-cell engager. It is built from two single-chain variable fragments joined by a flexible linker. A single-chain variable fragment is the antigen-binding part of an antibody reduced to a single protein chain, and the two fragments come from two different antibodies.
Because the two fragments differ, the two arms bind different targets. One arm binds CD3 on a T cell. The other arm binds CD19 on the leukemic cell. The molecule therefore holds the two cells together.
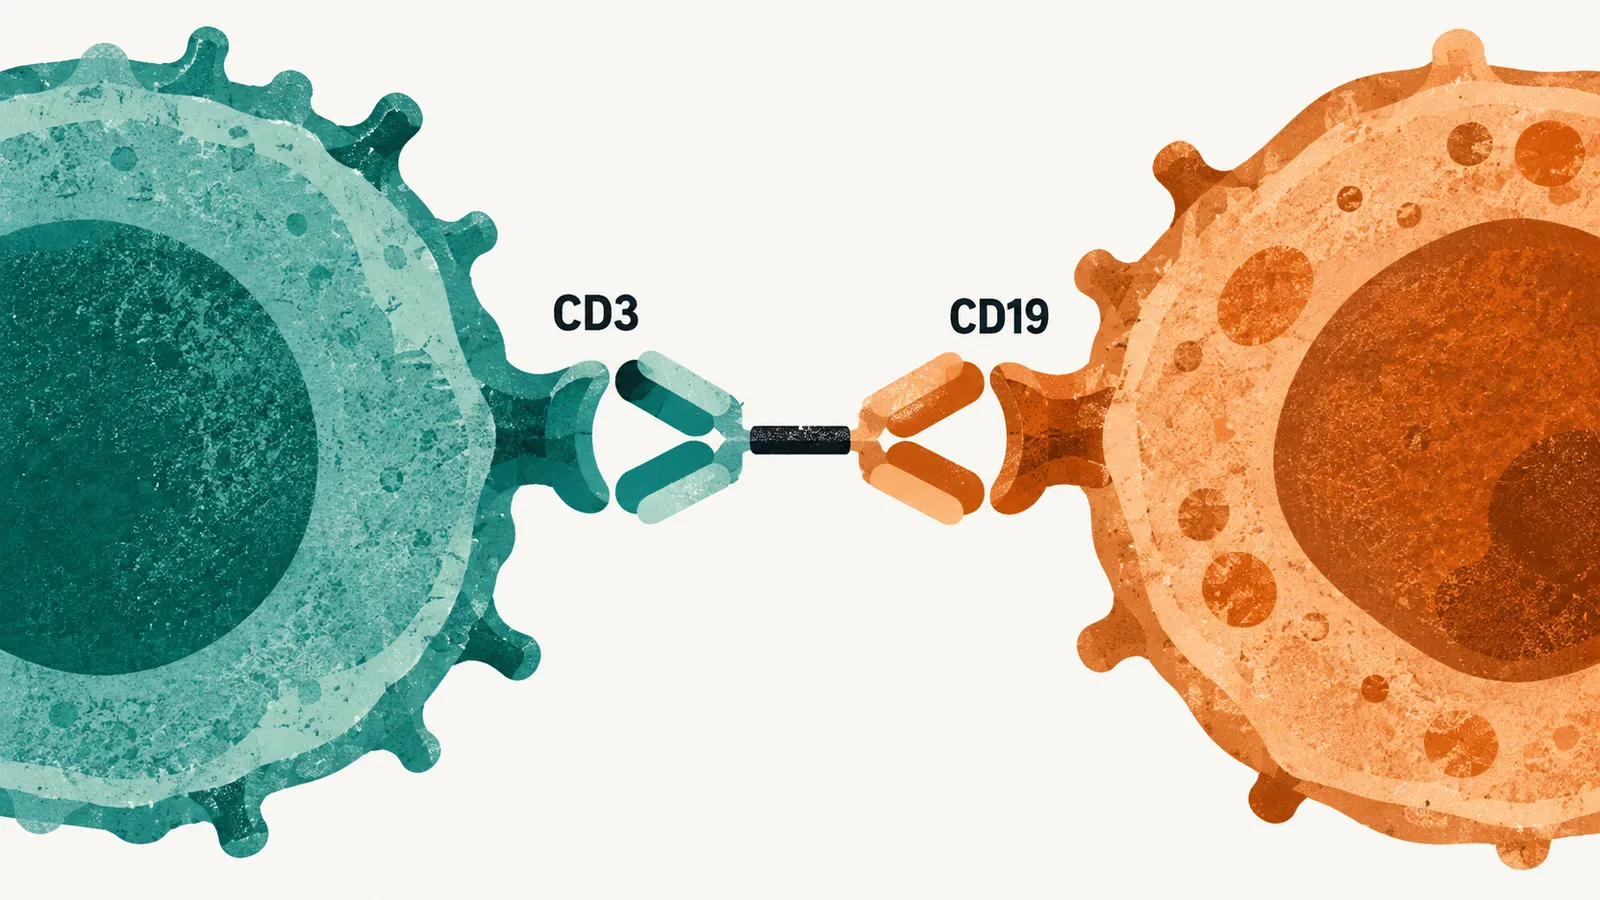
Why CD19? It appears from early B-cell precursors onward, and it is present on the great majority of B-ALL blasts. But CD19 is a lineage marker, not a tumor-specific one. Because it is a lineage marker, normal B cells are affected too, and this matters later.
Normally a T cell recognizes a tumor only when its receptor sees a tumor peptide presented on MHC class I. Bridging a T cell to a tumor cell triggers killing without that step. The T cell does not need to recognize a presented peptide, so receptor specificity is bypassed and MHC class I presentation is not required. This is the immunological point of the design.
Why is blinatumomab a continuous infusion?
Blinatumomab has no Fc portion, the constant tail of a normal antibody. Without it there is no Fc-receptor–mediated recycling. The half-life is short, a matter of hours. It is given as a continuous infusion, in 28-day cycles. An engager works only while the infusion runs.
The dose is escalated in a step-up phase at the start of a cycle, to limit early reactions. In the high-risk arm of the AIEOP-BFM ALL 2017 protocol, the dose is 15 µg/m²/day by continuous infusion over 28 days.
Why do the side effects follow the mechanism?
Blinatumomab shares the side-effect profile of the whole class of redirected T-cell immunotherapies. Four effects matter:
- Cytokine release syndrome (CRS): fever, hypotension, hypoxia and capillary leak. It comes from cytokines released by activated lymphocytes. Supportive care manages it. Severe CRS is treated with tocilizumab, an anti-interleukin-6-receptor antibody, or with corticosteroids.
- Neurotoxicity: encephalopathy, confusion, speech disturbance, tremor and seizures. It is graded through the (ICANS) framework.
- Liver derangement: elevation of transaminases and bilirubin, which can require treatment interruption.
- Hypogammaglobulinemia: low immunoglobulin and so a higher risk of infection, because normal B cells are lost alongside the leukemic clone. It may need immunoglobulin replacement.
These four follow from the mechanism, not from an idiosyncratic drug reaction. The first three reflect an immune system switched on more strongly than intended. The fourth reflects the target being a lineage marker rather than tumor-specific.
What if the T cell itself carries the receptor?
CAR T-cell therapy takes redirected immunity one step further. Instead of a bridging drug, the T cell itself is engineered.
The process is autologous, made from the patient’s own cells, and it takes weeks. T cells are collected from the patient and transduced with a viral vector carrying the CAR gene. The cells are expanded outside the body and then reinfused after lymphodepleting chemotherapy, which empties the niche the infused cells need to expand into.
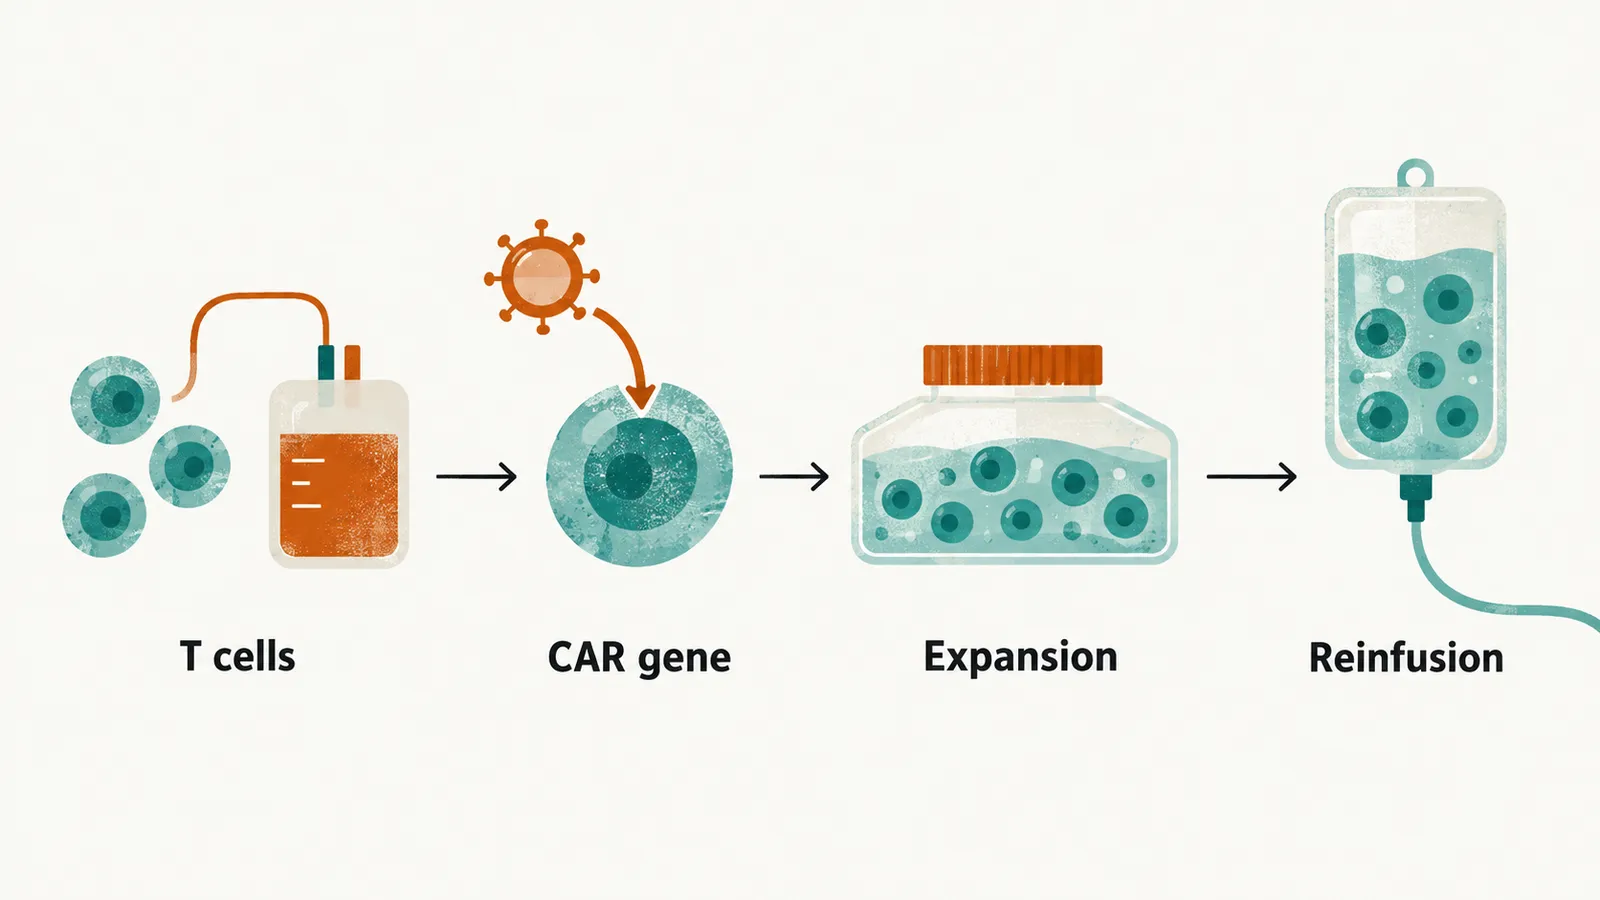
The CAR has three functional parts:
- An extracellular antigen-binding domain, usually a single-chain variable fragment derived from an antibody. For B-ALL it is almost always anti-CD19.
- A transmembrane region that anchors it in the membrane.
- An intracellular signaling domain, typically CD3ζ, which provides the activation signal.
One or more costimulatory domains (CD28 or 4-1BB) are added to the signaling domain. This addition defines . Without a costimulatory domain, the cells do not persist or expand well in the patient.
Like a bispecific engager, a CAR bypasses MHC presentation. The difference is in time. The CAR effect is cellular and self-renewing, so it persists as long as the engineered T cells survive, months to years. An engager works only while the infusion runs.
Tisagenlecleucel in practice, and what persistence costs
Tisagenlecleucel was the first CAR-T product approved for pediatric B-ALL. It is anti-CD19. It is approved for children and young adults up to 25 years with B-cell precursor ALL that is refractory or in second or later relapse. The pivotal trial ELIANA reported high remission rates in a population that had exhausted conventional options. Since then CAR-T has moved earlier in treatment for some high-risk and poor-response children, and the field is now testing CAR-T against intensive chemotherapy, not only in the relapsed setting.
The side effects are the same two as with blinatumomab, CRS and neurotoxicity (ICANS), and they are managed the same way. Two additional side effects are specific to the persistence of the engineered cells.
The first is B-cell aplasia with hypogammaglobulinemia. It is expected rather than incidental, because CD19 is on normal B cells as well. It can last months to years while the CAR-T cells survive, and it requires immunoglobulin replacement.
The second is secondary T-cell malignancy from insertional mutagenesis, the disruption of the cell’s own genes where the vector inserts into its DNA. It is rare. It has been reported following CD19- and BCMA-directed (B-cell maturation antigen) CAR-T products. After an FDA safety review in late 2023, regulators required a class-wide boxed warning for these products in January 2024. Permanent genetic modification carries a long-term risk that a bridging antibody does not.
Can the clone be killed without recruiting any immune cell?
Bortezomib pursues the same goal, a different way of killing the clone, without recruiting any immune cell. It acts inside the leukemic cell. It is a proteasome inhibitor, developed and approved for multiple myeloma, and used in ALL off-label, usually in relapsed or refractory disease or within a trial combination.
The 26S proteasome is the cell’s machinery for degrading regulatory proteins. These include cyclins, cell-cycle checkpoint proteins and IκB. IκB is the inhibitor of NF-κB, a transcription factor that drives a survival program. Inhibiting degradation lets these proteins accumulate. The cells then lose the ability to progress through the cell cycle and the ability to sustain the NF-κB-driven survival program.
In vitro, bortezomib is synergistic with dexamethasone against ALL cell lines, and additive with cytarabine, vincristine, doxorubicin and PEG-asparaginase. The hypothesis is sensitization: adding bortezomib to chemotherapy may deepen the remission in disease that responds poorly to the standard backbone. Whether laboratory synergy translates into better event-free survival in children remains a trial question.
The principal side effect is neurotoxicity, specifically a peripheral neuropathy that is dose-limiting and cumulative. The subcutaneous formulation produces less neuropathy than the intravenous one. Route and dose reduction are the standard mitigations.
Is the antibody only a way to engage T cells?
No. An antibody can also be used as a carrier. Conjugating a cytotoxic drug to an antibody against a B-lineage surface antigen delivers a selective hit to cells carrying that antigen. Inotuzumab ozogamicin targets CD22 and is used in relapsed B-cell ALL.
Antibody-drug conjugates are not the same as redirecting T cells, because no immune effector is involved. They belong to the same movement away from blanket cytotoxic exposure.
Bortezomib and the immunotherapies are not the only ways to spare the backbone. Gemtuzumab ozogamicin carries its payload to CD33 on myeloid blasts, so conjugation is not confined to the lymphoid lineage. Acute myeloid leukemia is a different disease, with a backbone of its own, and its biology decides intensity in a different way. How is it told apart from ALL in a child, and what decides how intensively it is treated? Childhood Acute Myeloid Leukemia takes that up.