Neonatal infection means bacterial infection during the first 28 days of life. The most important forms are sepsis and meningitis. In preterm infants the useful division is by timing rather than by organism, because the time of onset points to where the infection came from: the mother’s tract at or around birth, or the unit after admission.
Why split the infections by timing?
Timing is the first split, and it says where the infection came from. Early-onset infection appears in the first 72 hours. It is the infection the infant brings from birth. Late-onset infection appears after 72 hours. It is the infection acquired later in the stay. The two groups differ in the source of the organism, in which organisms are involved, and in treatment.
Why is a preterm infant so easy to infect?
Prematurity raises the risk of infection in three ways. The infant’s defences are immature. The care the infant needs opens routes for bacteria. And the cause of the preterm birth may itself be infective. Three routes open at once, so each one is taken in turn.
What the infant’s own defences lack
The first route is the infant’s own defence, which is the one that arrives late. Most maternal IgG crosses the placenta in the third trimester, so the amount the fetus receives builds up over those last weeks. An infant born before about 32 weeks has missed much of that build-up and receives little of the antibody repertoire that protects a term infant. As the corrected-age note showed, gestational age marks how far each organ had come.
The cells and proteins that act with antibody are also weaker. In the preterm infant, neutrophil numbers and function are reduced. Opsonization is reduced too. With less IgG and less complement, the coating of bacteria is thin. Complement activity is itself reduced.
The result is that a bacterium which a mature immune system would contain can spread instead. An infection that would stay in one place can pass from its local origin into the blood.
Where the barriers are breached
Once the defence is thin, the barriers and the devices become the way in. The skin is thin and easily macerated. It is also repeatedly broken by tape, electrodes and needles. The gut mucosa is permeable. The airway is instrumented with a tube.
Central venous catheters, endotracheal tubes, parenteral nutrition and repeated blood sampling give organisms a route into the circulation and a surface to colonize. A catheter passes the skin’s barrier and sits in the blood, so organisms that normally live on the skin have a direct path in.
What starts before birth
The third route is the pregnancy itself. Preterm labor, preterm premature rupture of membranes and chorioamnionitis are often infective or inflammatory in origin. So infection is part of the differential from the first minutes of life, not a complication that arrives later.
What causes early-onset infection?
Early onset starts at birth, so the organisms are those of the birth canal. Early-onset sepsis is acquired before or during birth, typically from the maternal genital tract, so the organisms are those that live there.
A prospective network study of very preterm infants found an incidence of 13.5 per 1000 very preterm births, about 1.4%. Escherichia coli accounted for 46.5% of the organisms and group B streptococcus for 18.8%. Group B streptococcus remains the more common cause in term infants, whereas E. coli predominates among preterm infants.
How does early-onset infection present?
The question is how an infant shows the infection. The presentation is often respiratory: grunting, retractions, apnea, a rising oxygen requirement, or an infant who is difficult to stabilize after delivery. The history gives risk factors: ruptured membranes, maternal fever or chorioamnionitis, and known group B streptococcal colonization.
Because early-onset infection can present as respiratory distress, it sits alongside respiratory distress syndrome in the differential of the first hours. The respiratory note explains why an immature lung struggles from its first breaths.
How does late-onset infection start?
Late onset is acquired after admission, so the unit is the source rather than the mother. Reported rates vary widely between units and are highest at the lowest gestational ages. In very-low-birth-weight infants, cohort studies commonly report roughly 15% to 25%. Late-onset infection is a risk of the weeks in the unit rather than of the first days, so its timing follows the length of the stay.
Which organisms and routes cause late-onset infection?
Many of the organisms that come from the unit enter through its devices. Coagulase-negative staphylococci are the most frequent isolates. They live on normal skin and a catheter carries them into the blood, which is why they are usually line-associated. They are followed by Gram-negative bacilli, Staphylococcus aureus and, in the most immature infants, Candida species.
Central venous catheters, mechanical ventilation, parenteral nutrition and long hospitalization all contribute. A central line is a direct route past the skin into the blood, and each device or feed adds another. The infections that follow are bloodstream infection, ventilator-associated pneumonia, and sepsis arising from necrotizing enterocolitis.
How are the gut and the blood linked?
One of those routes is the gut. Necrotizing enterocolitis and bloodstream infection frequently accompany each other. A damaged bowel wall lets organisms into the circulation, and infection worsens bowel perfusion. The two can be difficult to separate at the bedside. The nutrition note explains the bowel side of this.
Which signs point to infection?
Infection shows in the infant as general signs. No single sign identifies neonatal sepsis in a preterm infant. The pathogen spreads through the blood, so the signs are general rather than local, and the features that matter are those the infant cannot localize.
The features that matter are these:
- Temperature instability: fever or, more often in a preterm infant, hypothermia. A cold infant spends oxygen and glucose to keep warm.
- Increasing apnea, new respiratory distress or a rising oxygen requirement. Apnea in a preterm infant can be a control problem rather than a lung problem.
- Lethargy, hypotonia, poor perfusion, mottling, prolonged capillary refill or hypotension.
- Feeding intolerance, increasing gastric residuals or abdominal distension. Distension and rising residuals point to the bowel.
- Metabolic acidosis, unstable glucose, jaundice or a sudden drop in platelet count. Glucose falls when use outruns production and reserves are low.
Why can signs not settle the question?
Because the signs are shared, the decision is made with tests. Most infants investigated and treated for sepsis are not infected. Fear of missing infection leads to early antibiotics. A preterm infant with proven sepsis often looks no different from several others in the same unit, and preterm infants often show non-specific systemic signs first.
Assessment therefore rests on repeated examination and on trends rather than single values. Sepsis, necrotizing enterocolitis and metabolic decompensation must be held in mind together, since they present with the same instability, as an infant who has suddenly become less stable. No sign is decisive on its own. Signs cannot confirm or exclude infection.
What is taken before treatment starts?
The culture is the key test, and it has to be taken well. Diagnosis rests on samples taken before treatment begins and on how the infant and tests evolve afterwards. Cultures should ideally be collected first, but treatment is not held back while waiting for them.
Blood culture is the reference standard, and it should be taken before the first antibiotic dose. Guidance asks for about 1 mL of blood from a small infant. A smaller sample misses low-grade bacteremia, because it is less likely to contain the organisms.
When a central line is in place, blood is taken from the line lumen as well as peripherally. Catheter-related infection is proposed to start with organisms forming a biofilm on the catheter, so the line can carry the organism when peripheral blood does not. A line-associated infection may therefore be detectable only from the line.
What do inflammatory markers add?
A marker helps as a trend, and it has limits. C-reactive protein is measured at the start and repeated at 18 to 24 hours in an infant who remains a concern. The liver makes it in response to cytokines, so its level lags the illness. The pair of values is more informative than either alone.
C-reactive protein rises late and is raised by many non-infective causes, because any inflammatory stimulus can trigger the liver’s response. So it must not be used by itself to decide whether to start, continue or stop antibiotics.
When is a lumbar puncture done?
Meningitis is a separate question. A lumbar puncture is considered with signs suggesting meningitis, when infection is strongly suspected on clinical grounds, or when the blood culture is positive.
Meningitis changes the choice and duration of treatment. In an unstable infant, the decision is weighed against the risk of the procedure.
When does treatment start?
Once the decision to treat is made, the first doses cannot wait. Antibiotics are given as soon as possible and always within 1 hour of the decision to treat, and treatment is not delayed while waiting for cultures. But the decision is not made for every infant with a risk factor, since most are not infected.
What is given for early-onset infection?
The early-onset choice is the empirical combination, because treatment starts before the organism is known. It is intravenous benzylpenicillin plus gentamicin, the first choice in United Kingdom guidance. Ampicillin plus gentamicin is used in the same role in the United States. Local resistance data override the default.
The reference penicillin regimen is 25 mg/kg every 12 hours, and the interval may be shortened to 8-hourly on clinical judgement. Gentamicin is started at 5 mg/kg. These are unit protocols, not doses to prescribe from a note. The exact dose and interval depend on gestational age, renal function and local policy.
What is given for late-onset infection?
Late onset calls for a different combination, chosen from the unit’s data. An infant already on a neonatal unit is treated with a narrow-spectrum combination covering Gram-positive and Gram-negative organisms, such as flucloxacillin plus gentamicin. The combination is chosen against local susceptibility data rather than by habit. If necrotizing enterocolitis is suspected, the regimen follows the unit’s gut-oriented protocol.
When is treatment reassessed and stopped?
Treatment is a decision with an end point, not a default. Current guidance reassesses the need for antibiotics at 36 hours for early-onset and 48 hours for late-onset infection. If the cultures stay negative and the infant stays well, the suspicion that started treatment has not been supported. Treatment is then stopped if the blood culture is negative and the initial suspicion was not strong.
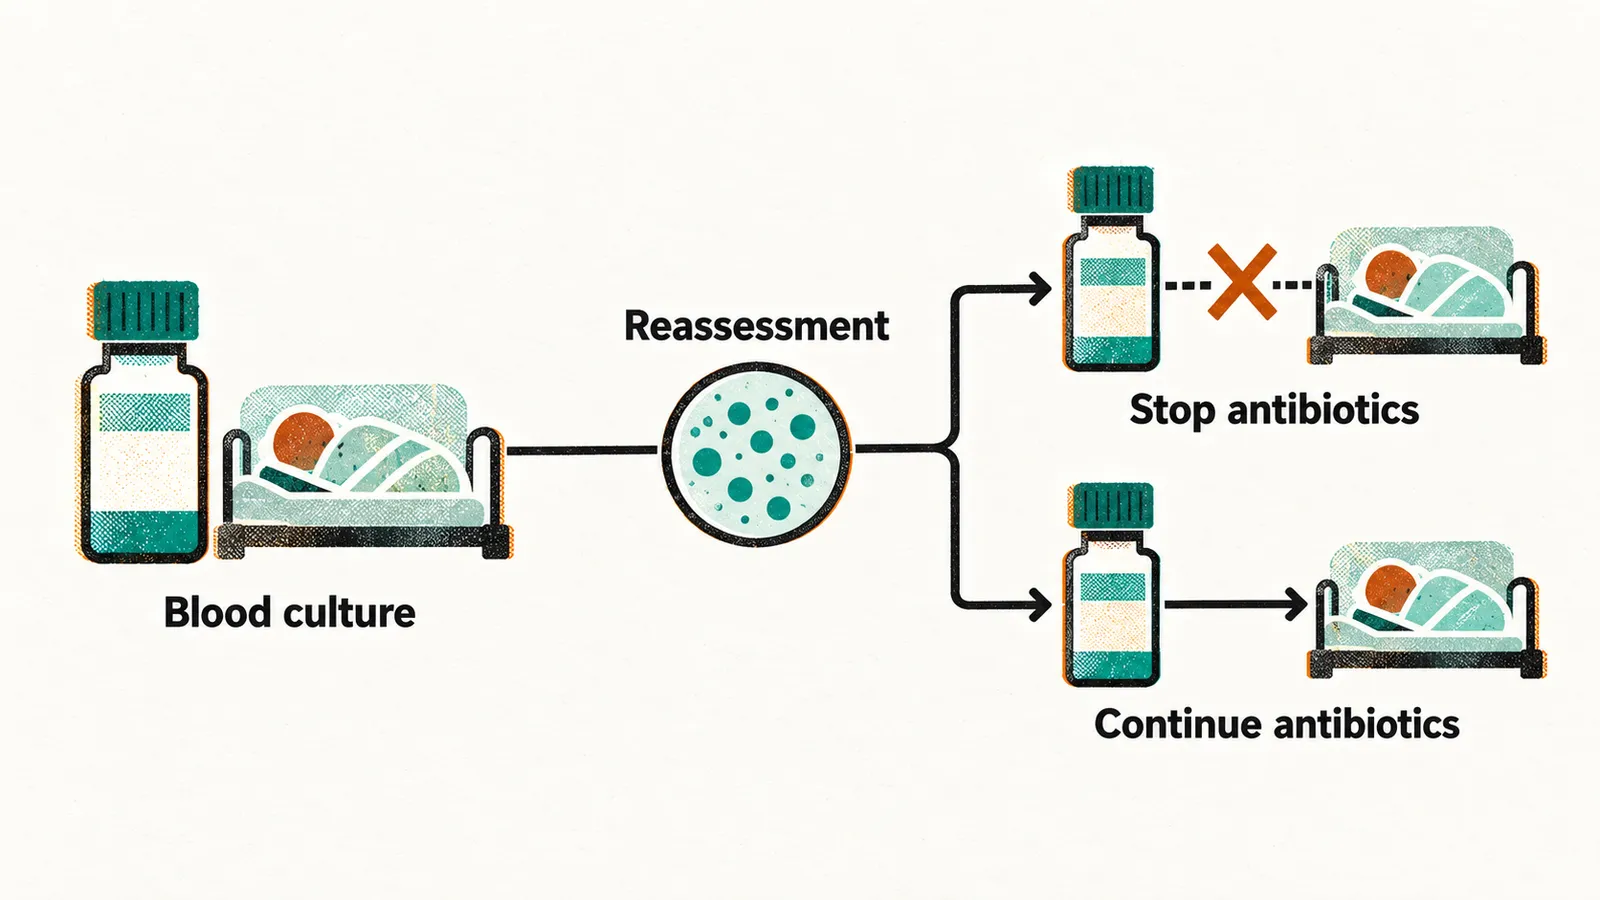
Treatment continues for 7 days if the culture is positive or if sepsis was strongly suspected despite a negative culture. It is extended beyond 7 days when the infant has not recovered or the organism requires it. Meningitis is treated for longer than sepsis. Stopping antibiotics is part of the treatment, not a failure of it, because it is the recommended course when the cultures and the infant’s course do not support infection.
Why does a longer course carry its own harm?
The harm of a long course is one reason stopping matters. Every extra day of an unnecessary course selects resistant organisms and disturbs the developing intestinal microbiome, as the nutrition note describes. Extra days of an unnecessary course are associated in cohort studies with necrotizing enterocolitis.
How is infection kept out of the blood?
Fewer routes mean fewer chances for organisms to enter. Hand hygiene remains the most effective single measure. The aim is to reduce the number of ways into the bloodstream, because each line, tube and feed is one.
Central lines are inserted aseptically, reviewed every day and removed as soon as they are no longer needed, following the unit’s central line-associated bloodstream infection bundle. A line in place is a route, so removing it removes that route. Unnecessary procedures are avoided, since each is another opening for organisms, and so are unnecessary antibiotics. Feeding with human milk lowers the risk of necrotizing enterocolitis, one of the routes to late-onset sepsis.
What else develops quietly in those weeks?
Late-onset infection is not the only risk of the weeks in the unit. Other injuries of prematurity develop quietly over those weeks while organs continue to mature outside the uterus. The brain keeps building itself outside the uterus, under the load of light, handling and instability. Some of these injuries can be found only by looking for them on a schedule, and units scan by protocol because the bleed gives no sign. The retina is still building its blood vessels in those same weeks. What happens to those vessels in the unit?