
Retinopathy of prematurity (ROP) is abnormal development of the retinal blood vessels in an infant born before the vessel network had finished growing. It is not an injury to a mature retina. It is a disorder of vessels interrupted in the middle of their growth. As the corrected-age note explains, the week of birth is a record of how far each organ had got before the placenta stopped supporting the infant, and the retinal vessels are one such organ. The disease develops over weeks, not hours. Untreated severe disease can detach the retina and cause blindness.
The whole disease can be pictured as one growing edge caught between too much oxygen and too little. The first question is where that edge lies.
Where do the retinal vessels grow?
The retina is vascularized from the optic disc outward. The vessels therefore start at the centre and spread toward the periphery, and a baby born early is delivered while the network is still under construction. The vessels reach the nasal periphery by about 36 weeks of gestation. They reach the temporal periphery not until around term.
This explains where the gap is. The temporal retina is the last to be vascularized, so it is the part most often left without a blood supply when a baby is born early.
What happens at the unfinished edge?
The outer retina is fed from the choroid. The inner retina is the layer that depends on the retinal vessels. So where the vessels have not grown, the inner retina is ischemic. That ischemic tissue is the engine of the disease.
The disease therefore begins at the border between the vascularized and the avascular retina.
What does birth do to the vessels?
The disease runs through two phases that pull in opposite directions. The first is vaso-obliteration. The fetus develops in a low-oxygen environment, so after birth the retina is exposed to an oxygen tension well above that, even in room air. At the same time the retina loses the placental growth factors it was receiving. Vessel growth stops or regresses.
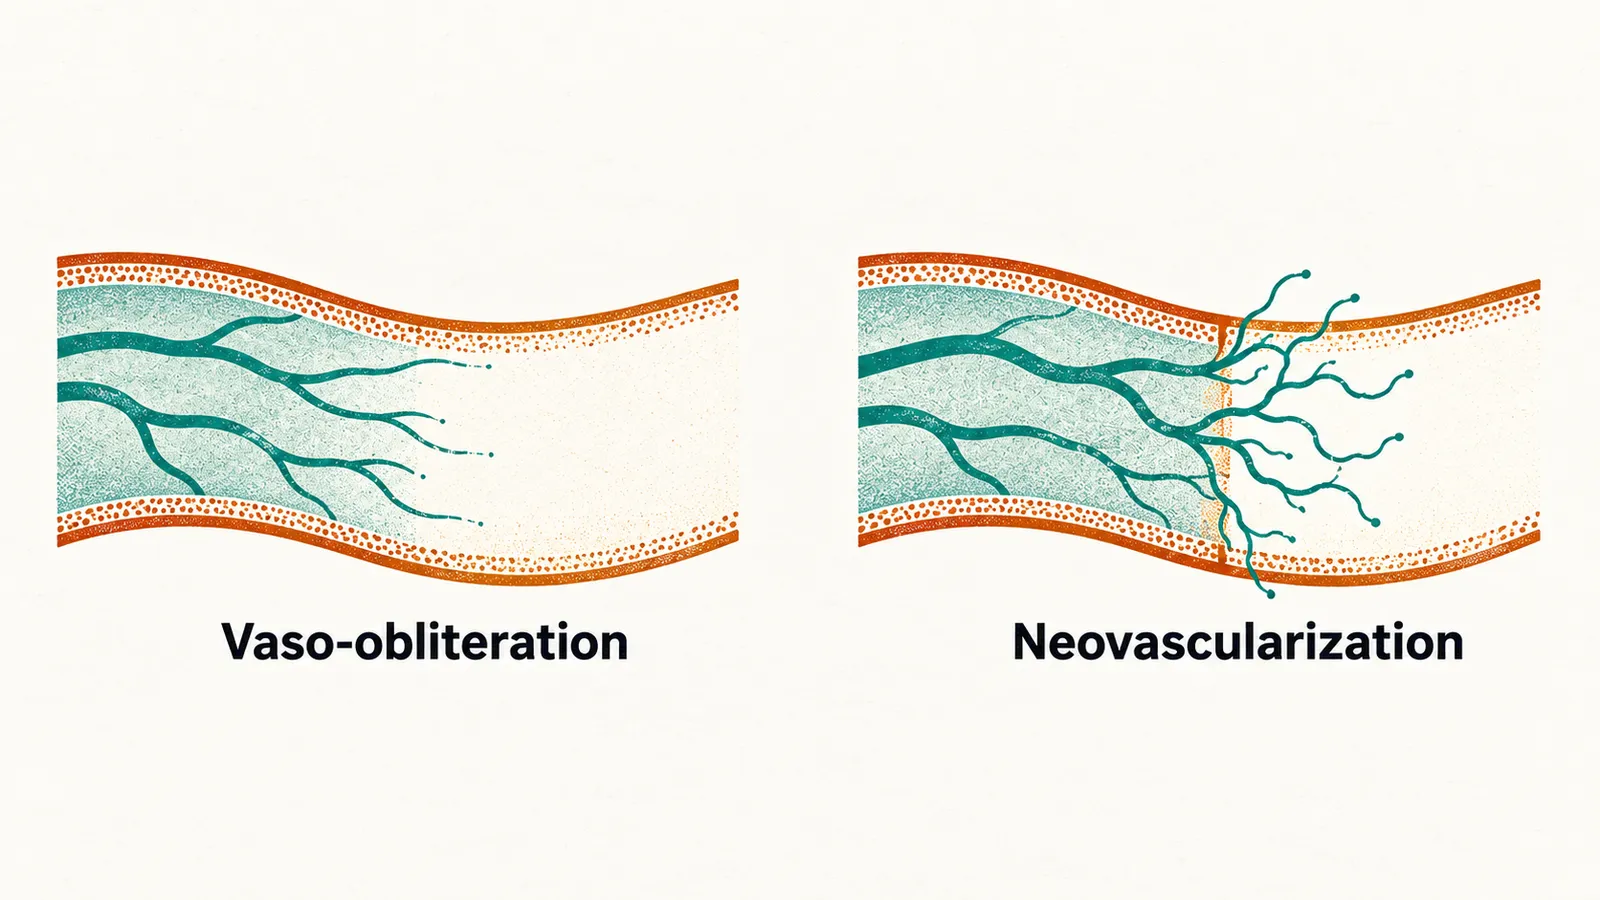
Vaso-obliteration removes vessels that already exist. The avascular area therefore ends up larger than birth alone would imply.
What does the starved retina do next?
The enlarged ischemic edge sets off the second phase, neovascularization. The ischemic peripheral retina releases VEGF. Because the signal comes from the starved tissue, new vessels form at the junction of the vascularized and the avascular retina.
These new vessels are abnormal. They leak and they bleed. Fibrovascular tissue can also form with them, and it can contract and pull the retina off the underlying wall.
Why is oxygen a risk in both directions?
The two phases have opposite causes, so oxygen is on both sides of the disease. As the golden-hour note explains, oxygen is thought to disturb the unfinished retinal vessels, and this is how. Too much oxygen arrests vessel growth and creates ischemia. Too little oxygen drives the second, proliferative phase.
The same tension shapes the saturation target from the delivery room onward. Oxygen is titrated to a protocol-defined range, not pushed as high as possible, because both extremes cause harm. Units rely on alarm limits, nursing vigilance and avoidance of sustained hyperoxemia and hypoxemia, since a swing in either direction can start one of the phases.
Why is there a target range instead of one number?
Because both extremes harm, several large trials compared a lower saturation target (85% to 89%) with a higher one (91% to 95%) in extremely preterm infants. The lower target reduced severe retinopathy. This fits the mechanism: less oxygen means less of the hyperoxia that shuts vessels down in the first phase. But the lower target also increased mortality. A pooled analysis of those trials confirmed that the two effects cannot be separated.
No single target has been adopted as safe. Units choose a range, commonly about 90% to 95%. The two harms pull in opposite directions, so any single setting trades one against the other. The best setting for a population is a compromise, and it is not safe for every infant.
How is the disease described?
Once the border is found, the examination describes where it lies, what it looks like and how active the retinal vessels are. Severity depends on all three, so findings are recorded by zone, stage and vascular activity, using the international classification.
The zone records how posterior the disease is. The zones are rings spreading outward from the optic disc, and the vessels fill them in that order.
- Zone I surrounds the optic disc and the macula.
- Zone II extends to the nasal periphery.
- Zone III is the temporal crescent, which vascularizes last.
Posterior disease is more dangerous.
What do the stages mean?
Within a zone, the disease is described by stage.
- Stage 1: a flat demarcation line.
- Stage 2: a raised ridge.
- Stage 3: extraretinal fibrovascular proliferation into the vitreous.
- Stage 4: partial retinal detachment.
- Stage 5: total retinal detachment.
What is plus disease?
Stage alone does not say how urgent the disease is. Plus disease adds that. It is increased venous tortuosity and arterial dilatation in the posterior pole. Plus disease is a marker of severe vascular activity. It is not a stage. Its presence changes the urgency.
Can the disease skip the usual sequence?
Sometimes the sequence of stages is compressed. Aggressive posterior ROP, previously called rush disease, is a rapidly progressive posterior form. It is most often seen in the least mature infants, and it compresses the usual staging sequence.
Why is screening needed at all?
Stages can only be written for infants who are examined, so the next question is who is examined. The infant cannot report failing vision, and ROP is invisible from outside until retinal detachment is advanced. As the brain-injury note explains, an infant with a brain bleed usually looks no different at the bedside, so scans are done by protocol rather than when a sign appears. The eye is screened for by protocol in the same way, not when poor vision is noticed.
Screening is therefore defined by risk rather than symptoms. Birth weight and gestational age show how unfinished the infant is. The screening population is infants with a birth weight of 1500 g or less or a gestational age of 30 weeks or less. It also includes selected heavier or more mature infants with an unusually unstable neonatal course, at the clinical team’s judgement.
Pooled population-based estimates show any retinopathy in about 30% of very-low-birth-weight infants and severe disease in about 9%. The programme therefore examines many infants to find the minority who need treatment. That is the practical argument for protocol-driven examination of every infant who meets the risk criteria. ROP remains a leading cause of childhood blindness where screening or treatment is unavailable.
When is the examination done?
The timing follows the vessel growth, because the retina is still being vascularized after birth. As the corrected-age note explains, postmenstrual age is gestational age plus the completed weeks since birth, and the schedule is set in those terms.
- Infants born at 22 to 27 weeks have a first examination due at about 31 weeks postmenstrual age.
- Infants born at 28 to 30 weeks have a first examination at 32 to 34 weeks postmenstrual age, or at 4 weeks of chronological age, whichever is later.
Examinations then continue at intervals set by the findings. Screening ends only when the temporal retina is fully vascularized or the disease has clearly regressed.
How is the examination carried out?
An ophthalmologist examines the infant with indirect ophthalmoscopy. The pupils are dilated in advance. The infant is monitored during and after the procedure.
Does every case need treatment?
No. Most ROP regresses on its own, so treatment is directed at type 1 disease. The current indications come from the Early Treatment for ROP trial. Type 1 disease is any of these:
- any stage in zone I with plus disease;
- stage 3 in zone I without plus disease;
- stage 2 or 3 in zone II with plus disease.
Type 1 disease can progress to retinal detachment within days, so a type 1 threshold is treated promptly, generally within 72 hours of diagnosis.
How is type 1 disease treated?
Two treatments are in use, and each acts on the starved tissue or on its growth signal.
Laser photocoagulation of the avascular peripheral retina destroys the tissue that is short of blood. This removes the ischemic tissue that drives VEGF production, so the growth signal stops. Laser has been the standard treatment since trials showed that early treatment of type 1 disease preserves vision better than observing until threshold disease.
Intravitreal anti-VEGF injection blocks the growth factor directly. It acts on the signal rather than destroying the tissue that makes it. It produces faster regression, and it is often used for posterior disease, where laser is technically difficult. Its effect is temporary, however, and reactivation can occur later, after the usual screening period. Infants treated with anti-VEGF therefore need prolonged ophthalmological surveillance.
Treatment of severe disease markedly reduces the blindness it would otherwise cause.
What if the retina detaches?
Stage 4 and stage 5 disease, with retinal detachment, requires vitreoretinal surgery. The visual outcome after surgery is much less predictable than after timely treatment of type 1 disease.
What lasts after the eye is treated?
Regression is the usual outcome of treated type 1 disease, but it is not the end of the story. Children who had any ROP, including disease that resolved without treatment, carry a higher risk of myopia, strabismus and refractive error. Ophthalmological follow-up therefore continues well beyond the neonatal period.
What else from the neonatal unit carries on into childhood, beyond the eyes?