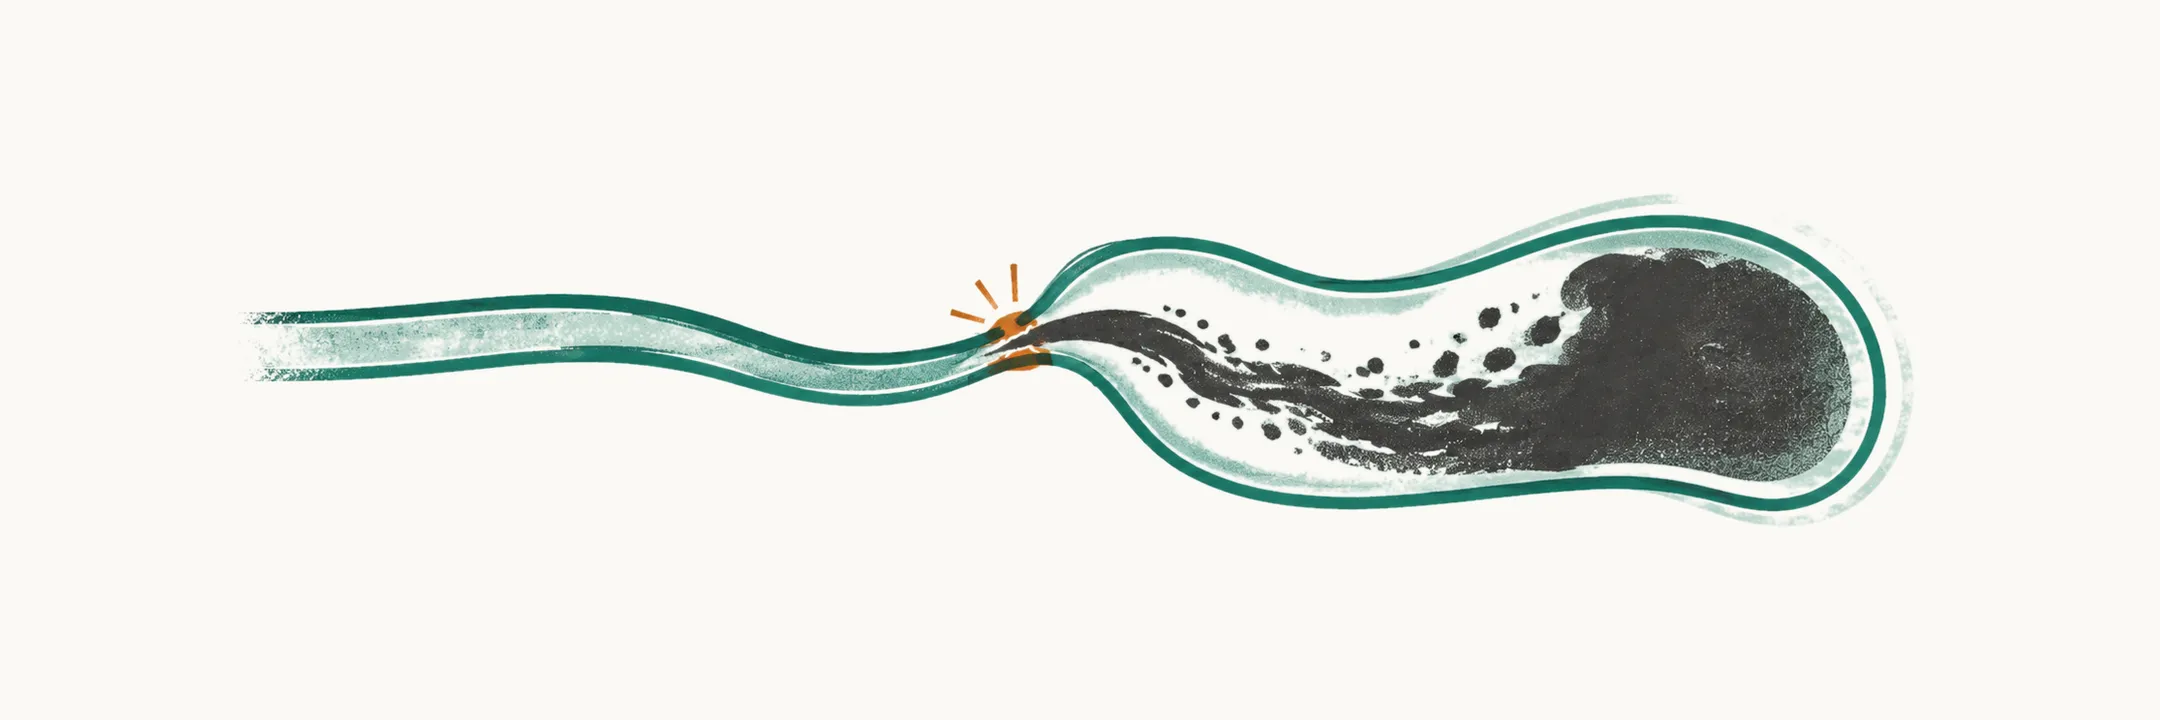
Intraventricular hemorrhage (IVH) is bleeding that begins in the germinal matrix of the very preterm brain and reaches the ventricular system. It is the characteristic hemorrhagic injury of extreme prematurity. Cystic periventricular leukomalacia (cPVL) is the characteristic ischemic injury of the white matter of the same brain, and it arises because that tissue loses its blood supply and oxygen. These are the findings that most consistently predict later cerebral palsy and cognitive difficulty in infants born at the earliest gestations. Start where the bleed begins.
Where does the bleed begin?
The bleed begins in one specific layer, so that layer comes first. The germinal matrix is a thick, densely vascular region beneath the ependyma, beside the lateral ventricles. It is a richly vascularized layer of precursor cells, and the bleed usually begins there. Because it lies against the ventricles, blood that escapes from it reaches the ventricular system.
The same layer is where neurons and glia are generated, so it is both the brain’s cell factory and its blood-rich bed. It is at its largest between roughly 24 and 32 weeks of gestation, and it involutes before term.
Why do these vessels break so easily?
That layer is the one that bleeds, and its vessels are the weak point. They are fragile, thinly walled and poorly supported, so they rupture more easily than mature vessels. Fragile vessels tear more readily under pressure, and this fragility is one of the factors strongly associated with IVH.
The second weakness is autoregulation. Premature infants are born with immature autoregulation, so the brain’s vessels cannot yet hold flow steady as blood pressure changes. The circulation is pressure passive: a change in pressure passes straight into the vessels instead of being buffered. A sudden rise in arterial pressure, a fluid bolus, a change in carbon dioxide tension, a pneumothorax or a painful procedure can therefore all be transmitted to the fragile vessels of the germinal matrix.
Who bleeds, and when?
Knowing the mechanism, the next question is how often this happens and when. Most hemorrhage occurs within the first 72 hours after birth, and about half is already visible on the first day.
As the corrected-age note showed, the risk climbs as gestational age falls. Here, risk falls steeply as gestational age rises. Roughly 20% to 25% of very-low-birth-weight infants develop IVH. The proportion with a severe bleed is highest at the earliest gestations. In one population cohort, severe hemorrhage affected about 36% of infants born at 22 to 23 weeks, 21% of those born at 24 to 25 weeks, and just under 10% of those born at 26 to 27 weeks.
How is the bleed graded?
Once the bleed is known to happen, the next question is how it is described. Cranial ultrasound grades the lesion, using the classification introduced by Papile and colleagues. It began as a CT-based scheme and was later adapted to ultrasound, and cranial ultrasound is the imaging modality of choice for diagnosing and classifying the bleed.
- Grade I: blood confined to the germinal matrix (subependymal hemorrhage). The bleed has not yet entered the ventricle.
- Grade II: blood within the ventricle without ventricular dilatation.
- Grade III: blood within the ventricle with ventricular dilatation. Clots block the cerebrospinal fluid channels, so the ventricles swell when blood is in them.
- Grade IV: periventricular hemorrhagic infarction.
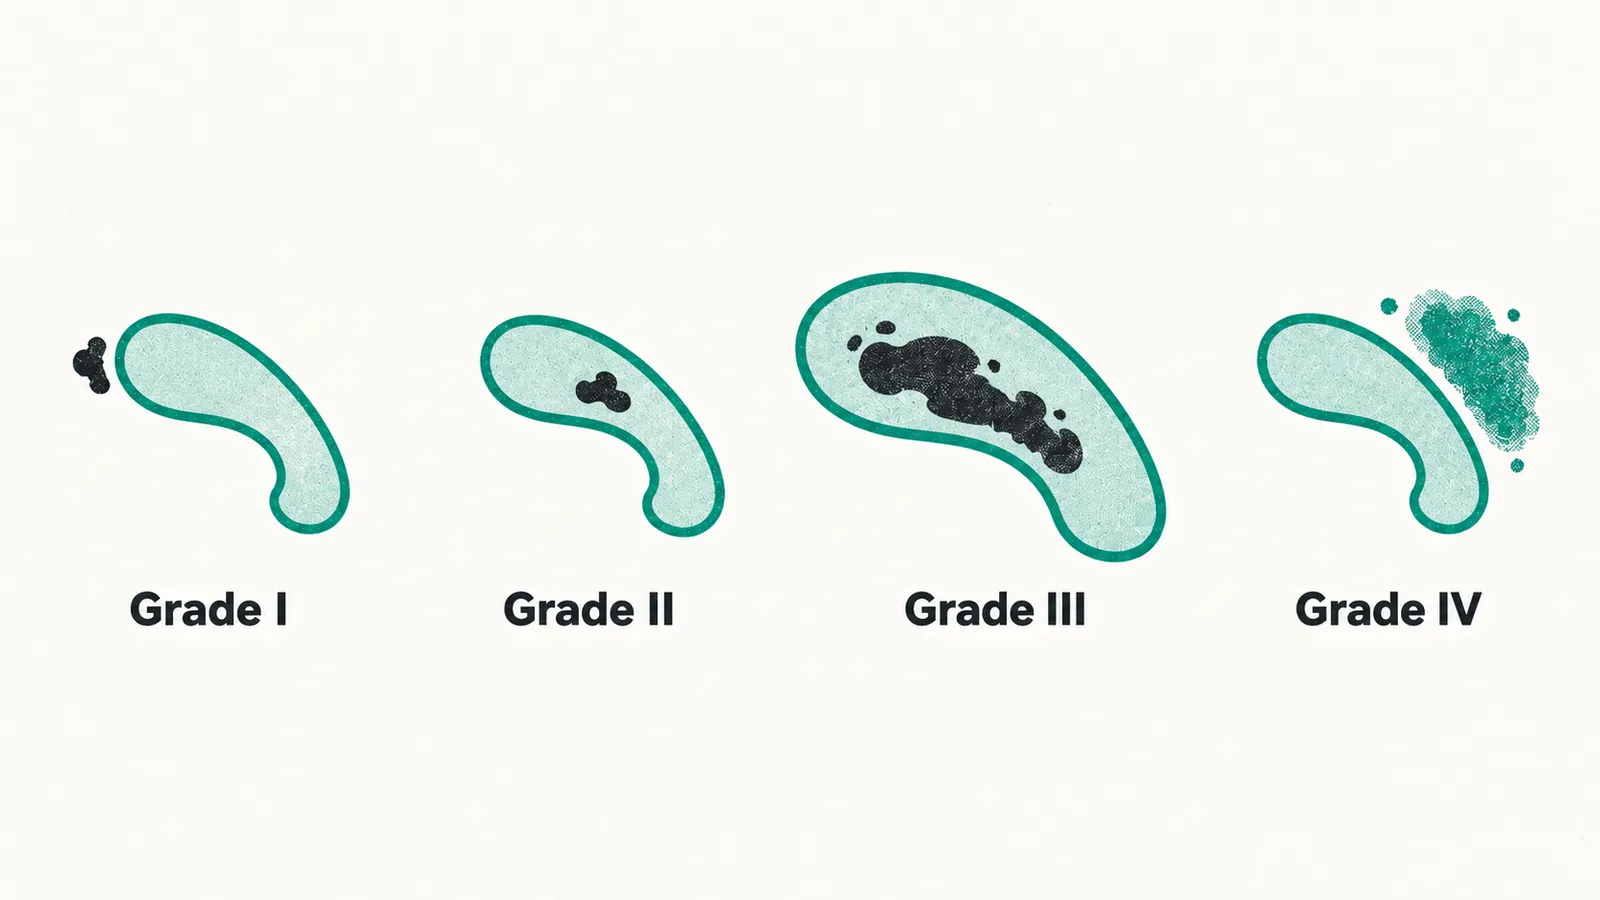
The label “grade IV” is historical. It comes from the original scheme, which is why the older name remains. The parenchymal lesion of grade IV is now understood as periventricular hemorrhagic infarction, usually a venous infarction beside the ventricle rather than blood simply spilling out of the ventricle. The periventricular hemorrhagic infarction component, not the intraventricular blood itself, carries the worst prognosis.
Why scan a baby who looks well?
Since the grade is found on a scan, the next question is why a scan is needed at all. An infant with IVH usually looks no different at the bedside. Apnea, a fall in hemoglobin, a bulging fontanel or a seizure appear only with large bleeds. So units scan by protocol instead of waiting for a sign. National guidance agrees on the principle of screening and differs on the timetable.
When are the scans done?
A scan shows the grade at one time, so the next question is when to look again. The two bodies differ as follows.
- AAP: scans infants born at or before 30 weeks, with the first scan by 7 to 10 days, a repeat scan at 4 to 6 weeks, and a later scan at term-equivalent age or before discharge.
- Canadian Paediatric Society: scans all infants born at or before 31 weeks and 6 days, with the first scan at 4 to 7 days, a repeat scan at 4 to 6 weeks, and a later scan at term-equivalent age for the most immature infants.
The first scan is done early, because the bleed happens early. Imaging is repeated, because ventricular dilatation and white-matter injury evolve after the first few days. A normal scan in the first week does not close the question.
What does blood in the ventricles do?
The first scan shows blood, and the blood’s next effect is on the ventricles. Blood in the ventricular system obstructs the flow and reabsorption of cerebrospinal fluid. Multiple small clots throughout the cerebrospinal fluid channels impede its flow. A grade III or grade IV hemorrhage may therefore be followed by post-hemorrhagic ventricular dilatation, a progressive complication of intraventricular bleeding.
How is the enlargement followed?
Enlargement is followed by measurement, not by the head. Because the dilatation is progressive, the ventricles have to be measured again to see whether they keep growing. This is done with serial ultrasound measurements of the ventricular index and the anterior horn width. It is tracked this way rather than by head circumference or the fontanel alone, because physical signs of raised pressure appear late in a very preterm infant.
What is done if the ventricles keep growing?
If the ventricles continue to enlarge, cerebrospinal fluid is drained first with a temporary device such as a ventricular access reservoir or a ventriculosubgaleal shunt. Later, in a minority of infants, drainage is done with a permanent ventriculoperitoneal shunt. Serial lumbar punctures, acetazolamide or furosemide, and intraventricular fibrinolytic therapy are not recommended for preventing death or shunting. Early ultrasound-guided drainage and surgery are the measures in use.
Can the bleeding be prevented?
Because most of the bleeding is early, protection has to start at birth. Most bleeding happens in the first days, so protection has to be in place from birth. Much of protection is arranged before birth, through obstetric management of threatened preterm delivery and delivery in a center with neonatal intensive care. The antenatal part of prematurity belongs with the obstetric side of the subject rather than here.
What can the neonatal unit do?
The unit’s measures follow from the fragile vessels and the immature autoregulation just described. A pressure-passive circulation is vulnerable to swings, so the neonatal unit aims to avoid them. The measures are those of gentle intensive care:
- Avoid rapid volume expansion and swings in blood pressure. A rapid fluid bolus raises pressure in a circulation that cannot buffer it, so the pressure reaches the fragile vessels.
- Avoid hypocarbia and large fluctuations in carbon dioxide.
- Use the least injurious form of ventilation.
- Keep the head midline.
- Handle the infant as little as possible.
Delaying cord clamping at birth is associated with less intraventricular hemorrhage. The evidence for individual postnatal measures is weaker than for antenatal ones. Postnatal measures are used together as a bundle of practices rather than as single proven interventions.
Why does handling matter for the brain?
Handling is one of the measures, and it is part of a larger load on the brain. As the corrected-age note showed, the developing brain and retina are exposed to oxygen swings, light, noise, pain and hemodynamic instability. Light, noise, handling, pain and cardiorespiratory instability during a period that would normally be spent inside the uterus are part of the load on a brain that is still building itself. Developmental care is designed to reduce that load, and handling is one of the stresses it aims to reduce.
Is hemorrhage the only injury?
The same immature brain can also be injured without any bleed. Hemorrhage is not the only injury of this brain. Premyelinating oligodendrocytes are concentrated in the white matter beside the lateral ventricles during the same 24- to 32-week window. They are unusually vulnerable to low perfusion, inflammation and free-radical injury. This vulnerability is tied to the cell’s immature stage, so insults other than bleeding can injure the white matter. A fall in cerebral blood flow, a systemic infection, or the inflammatory response accompanying necrotizing enterocolitis can damage the white matter even when there is no hemorrhage at all. Necrotizing enterocolitis is inflammatory necrosis of the immature bowel.
What does white-matter injury look like?
That injury is seen as cysts, and sometimes only as diffuse change. The classic result is cystic periventricular leukomalacia: small cysts in the periventricular white matter that become visible on ultrasound days to weeks after the insult. Diffuse, non-cystic white-matter injury is more common than the cystic form and also affects outcome. It is harder to see on ultrasound and may be recognized only on MRI at term-equivalent age.
Which bleed leads to which problem?
Both injuries affect the same brain, so the outcome has to weigh both. As the corrected-age note showed, complications share one cause and interact rather than simply adding up. Hemorrhage and white-matter injury affect the same immature brain, so prognosis has to weigh both. The grade and the location of the lesion matter, and neither is a prediction of an individual child’s future on its own.
Grade I and II hemorrhage without parenchymal involvement is associated with a measurable increase in neurodevelopmental impairment, cerebral palsy and sensory deficits compared with no hemorrhage at all. That increase is larger than older teaching suggested, but much smaller than with severe bleeding. Grade III and IV hemorrhage, and especially periventricular hemorrhagic infarction, carries a substantially higher risk of motor impairment and of the hydrocephalus that may follow. This fits what the grades mean: these are the bleeds that enlarge the ventricles, and progressive dilatation is a complication of intraventricular bleeding.
Why does white-matter injury cause cerebral palsy?
White-matter injury is the lesion behind the most serious motor outcome. Because the corticospinal tracts pass through the periventricular region, the resulting motor deficit is predominantly spastic. Cerebral palsy in preterm infants has long been considered to result from damage to the periventricular white matter, the lesion called periventricular leukomalacia. Cystic periventricular leukomalacia is the lesion most consistently associated with later cerebral palsy, and bilateral and extensive disease carries the highest risk.
Cystic periventricular leukomalacia carries the highest motor risk and is often accompanied by cognitive, visual and language difficulty. Cerebral palsy is more common the more immature the birth, and both IVH and white-matter injury contribute to that excess risk.
Is the outcome decided by the scan?
Outcome is never decided by the ultrasound label alone. It depends on the extent and laterality of the lesion, later imaging, seizures, hearing and vision, the family and social environment, and the child’s own developmental trajectory. High-risk developmental follow-up and early therapy matter as much as the neonatal scan. Why is the immature gut also vulnerable, and how can such an infant be fed?