
A patent ductus arteriosus (PDA) is the fetal vessel that connects the pulmonary artery to the descending aorta, still open after birth. The vessel is normal and essential in the fetus. It becomes a problem only when it stays open after the neonatal period.
Why does blood skip the lungs before birth?
Before birth the fetus gets its oxygen from the placenta, not from its lungs. The lungs are fluid-filled and do not perform gas exchange, so fetal pulmonary vascular resistance is high. Blood entering the pulmonary artery therefore has little reason to go through the lungs. It bypasses them through the ductus and flows right to left into the aorta.
What changes at birth?
The fetal route works only until birth changes the pressures. Cord clamping removes the low-resistance placental circulation, so systemic vascular resistance rises. The first air in the lungs lowers pulmonary vascular resistance, and lung aeration is what starts the change. Flow across the ductus first reverses to left to right. The vessel then constricts, because oxygen tension rises and placental prostaglandin input falls. The rise in oxygen is what allows the vessel to constrict.
When does the ductus close?
Once the lungs open, the vessel is set to close, and the next question is how fast. Functional closure normally begins within hours of birth, as rising oxygen tension and falling flow let the vessel constrict soon after the first breaths. Anatomical closure follows over days to weeks.
Why does the ductus stay open in a preterm infant?
Closure needs signals, and a preterm infant may not have them. In a preterm infant the ductus often remains open because the closing signals are weak or delayed. Preterm birth disrupts the maturation process, so the immature vessel cannot answer the postnatal cues that would close it.
The closing signals are:
- lung aeration;
- rising oxygen tension;
- falling prostaglandin exposure;
- reversal of the fetal pressure gradient.
Which three signals keep it open?
The closing signals fail for three reasons, and each one is a signal that stays on. These three mechanisms reinforce each other to keep the ductus open in prematurity.
The first is low oxygen tension. The respiratory note explains why the immature lung cannot oxygenate the blood. Oxygen is the signal that allows constriction, so when oxygen is low the constricting signal is weak. Hypoxia is also a potent ductal vasodilator.
The second is persistent prostaglandin activity. Prostaglandin E2 vasodilates the ductus, so it, together with prostacyclin, holds the vessel open. The immature lung metabolizes and clears these mediators more slowly, so vasodilator tone persists.
The third is a delayed fall in pulmonary vascular resistance, which the next section takes up.
Why does poor lung inflation keep the pressures high?
The lung is also what sets the pressure, so the lung’s state keeps the vessel open. Poor lung inflation keeps pulmonary pressures high. Lung aeration comes before closure, so poor inflation delays the pressure reversal that normally accompanies the change in flow direction, the change the vessel waits for.
The link runs both ways. As the respiratory note explains, lung disease itself keeps the ductus open. And as that note also explains, the extra blood adds to the fluid the immature lung already struggles with. An open ductus increases pulmonary blood flow and worsens lung edema, which makes respiratory support more difficult.
Does the ductus always stay open after a preterm birth?
A preterm ductus may stay open, but not always. An immature ductus cannot respond to postnatal cues, so spontaneous closure is common but not the rule at the earliest gestational ages. In extremely low-birth-weight infants managed without intended closure, roughly one third close in the first one to two weeks. Further closures occur over the subsequent weeks.
Which way does the blood cross once it stays open?
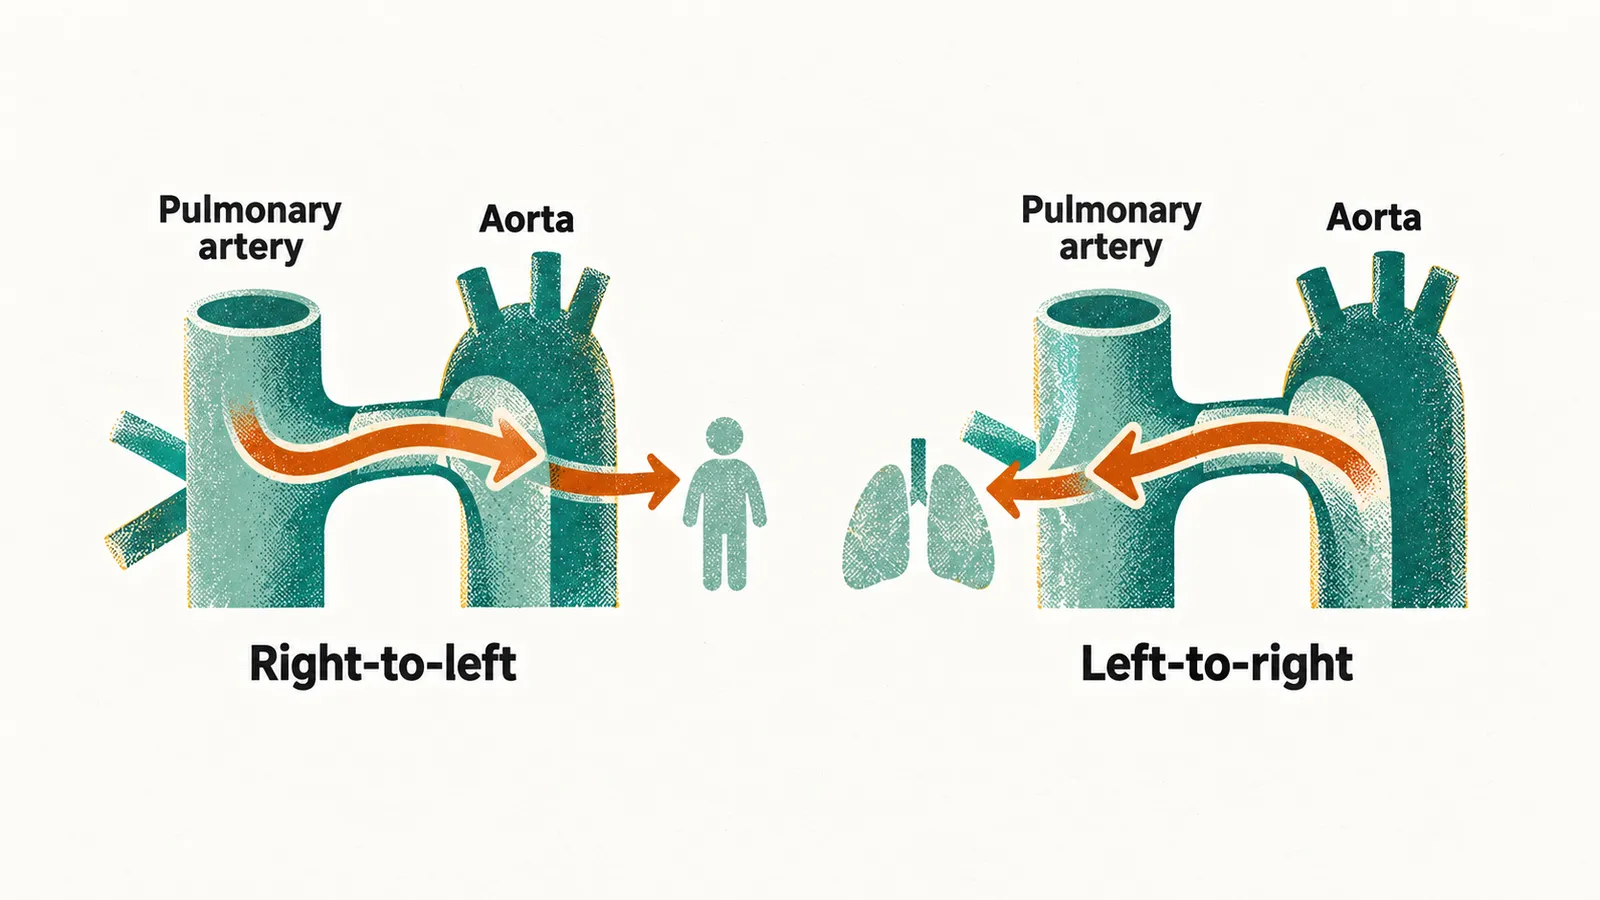
The direction of the crossing depends on which side has the higher pressure. Once the ductus stays open, blood crosses from the side with the higher pressure, and each shunt direction produces a different problem.
Right-to-left shunting persists when pulmonary pressure remains above systemic pressure. Blood that has bypassed the lungs goes straight to the body, so systemic saturation falls in the organs distal to the ductus.
How does the bedside show the shunt?
Right-to-left flow shows in the right hand compared with the lower body, and left-to-right flow shows in the pulse.
The right-hand reading is the preductal one, as the golden-hour note explains. The right-arm saturation reflects blood that has not passed the ductus. It is compared with a lower limb or the left arm, which are postductal. The lower body is supplied with blood from after the ductus, so the comparison shows what came through the vessel. A difference suggests that blood reaching the body has skipped the lungs. That suggests persistent fetal-type shunting or pulmonary hypertension.
Left-to-right flow gives a different set of signs: a systolic murmur, a bounding pulse, a wide pulse pressure and a hyperactive precordium. A wide pulse pressure can be associated with blood running off into the pulmonary circulation. These signs appear late and are unreliable in small infants.
What happens when blood crosses the other way?
Once the lungs are open, blood crosses from the aorta into the pulmonary artery, and the lungs receive too much. Left-to-right shunting develops when systemic pressure exceeds pulmonary pressure while the ductus stays open. Blood runs from the aorta into the pulmonary artery.
This produces pulmonary overcirculation and pulmonary edema, because extra blood is pushed through the lungs and loads them. It also increases pulmonary venous return to the left atrium. The left atrium can enlarge and eventually fail.
Why does blood get stolen from the body?
The extra flow to the lungs is paid for by the rest of the body. Left-to-right flow can steal systemic blood during diastole. Blood the body needs escapes into the lower-pressure pulmonary circulation at the moment the systemic circulation should be perfusing the organs, so the organs get less.
Doppler studies may show absent or reversed diastolic flow in systemic vessels. Steal is the hemodynamic link between a hemodynamically significant PDA and renal dysfunction, reduced gut perfusion and cerebral vulnerability. Steal lowers flow to the organs, which is why the kidney, gut and brain are linked to the ductus.
Why is the ductus not only a heart problem?
The steal reaches the kidney, gut and brain, so the question widens. Whichever route is chosen for managing it, the ductus is not only a heart problem. Steal already links the ductus to renal dysfunction, reduced gut perfusion and cerebral vulnerability.
The cerebral vulnerability linked to the PDA includes its ischemic contribution to necrotizing enterocolitis. Reduced blood flow to the bowel is the link, and a proposed explanation for the bowel association is this ischemia.
How is the ductus confirmed on echo?
A bedside suspicion is confirmed by echocardiography, which also estimates the shunt. Echocardiography is the standard tool. It confirms the ductus, identifies the direction of flow and measures the ductal diameter. It also estimates whether the shunt is hemodynamically significant, through left atrial enlargement and altered diastolic flow in systemic vessels. These are signs of pulmonary overcirculation and of load on the left heart.
Is an open ductus always a problem?
Echo shows the vessel, but the question is whether it hurts the body. An open ductus matters when the shunt causes systemic hypoperfusion or pulmonary overcirculation. So the bedside question is not simply whether the ductus is open. It is whether the ductus is worsening pulmonary disease or reducing systemic organ perfusion enough to justify closing it. A small ductus in a stable infant is often observed.
What is done first?
Supportive care comes first, and it works on the same signals as before. Optimizing ventilation and lung recruitment lowers pulmonary vascular resistance. Lung aeration comes before closure, so better ventilation also strengthens the oxygen signal for constriction. Fluid and diuretic management limits pulmonary congestion. Oxygen is deliberately not pushed high, because excess oxygen contributes to retinopathy of prematurity, as the golden-hour note explains.
How do drugs close the ductus?
If supportive care does not close the ductus, drugs can block the prostaglandin signal. Prostaglandin synthesis inhibition is the pharmacological route, using a cyclooxygenase inhibitor. Blocking the enzyme lowers the prostaglandin signal that holds the vessel open.
Ibuprofen is widely used: 10 mg/kg, then 5 mg/kg at 24 hours and again at 48 hours. This is a standard neonatal protocol, not a prescription to dose outside a unit’s own policy.
Indomethacin has similar efficacy to ibuprofen, so the difference between them lies in side effects. In pooled trials its profile is less favorable. It causes more transient renal impairment and oliguria, and it is associated with reduced blood flow to several organs, the kidney among them. Ibuprofen is often preferred over indomethacin.
Why does closing it harm the gut and kidney?
A drug that closes the ductus can also reduce flow to organs, and the gut is the sharpest conflict. Closing drugs reduce the prostaglandin signal, which is associated with reduced blood flow to several organs. A drug that closes the ductus therefore reduces pulmonary overload but can worsen renal and bowel perfusion. This is especially likely at the lowest gestational ages.
Necrotizing enterocolitis is the sharpest conflict with ductus closure, because the bowel and the ductus pull in opposite directions. Indomethacin and ibuprofen may worsen bowel ischemia or perforation. When active necrotizing enterocolitis is present or strongly suspected, closure is deferred.
Why is paracetamol sometimes used instead?
Paracetamol (acetaminophen) acts on a different part of the same enzyme. It is considered when the other drugs are unsuitable. It blocks the peroxidase part of the enzyme, not the cyclooxygenase part that ibuprofen and indomethacin block.
In pooled evidence, paracetamol achieves closure rates similar to ibuprofen with fewer renal and intestinal adverse effects. Intravenous paracetamol has been less effective than the enteral route in some trials. The quality of the evidence remains limited. Paracetamol is often considered when bleeding risk, thrombocytopenia, renal risk or bowel disease makes cyclooxygenase inhibitors unsuitable.
What if drugs fail or are unsafe?
When drugs cannot close the ductus, or cannot be used, the vessel may be tied off, and that has its own risks. With active necrotizing enterocolitis, the open ductus is managed supportively with fluids and diuretics until the bowel recovers.
Surgical ligation is reserved for infants in whom medical closure has failed or is contraindicated. It is also reserved for infants who remain ventilator-dependent because of the shunt. Ligation closes the vessel immediately. That sudden change forces an immature circulation to adapt in seconds rather than over days. Postoperative hemodynamic instability is the main concern after ligation, and the immediate complications of surgical closure are often serious.
Why is the preterm brain at risk too?
The ductus steal reaches the brain, and the brain is itself poorly protected. The very preterm brain has immature regulation of its own blood flow. It is also poorly protected against swings in blood pressure. Why does a very preterm brain bleed when its blood pressure swings?