
Neonatal respiratory distress syndrome (RDS) is acute respiratory failure caused by an immature lung. It is principally caused by too little surfactant and by gas-exchange architecture that is not yet complete. It is the dominant early complication of very preterm birth, and it is also called surfactant-deficient hyaline membrane disease. It is a different disease from adult ARDS, with a different mechanism and definition. Both produce hypoxemic respiratory failure, but the two are not interchangeable.
The lung ends in many small air sacs, and oxygen passes from them into the blood. Each sac has to stay open between breaths, and surfactant is what keeps it open. Preterm birth arrives before the lung has built enough air sacs or made enough surfactant. The sacs then collapse, the lung becomes stiff, and every breath has to reopen them. That one problem explains the effort, the tests, and the support.
Why does the preterm lung fail to hold air?
The lead named surfactant deficiency as a principal cause, so the next question is why a preterm lung lacks it.
Lung development runs through overlapping stages. At 23 to 28 weeks the lung is in the late canalicular to early saccular phase. The airways are present, but the region that exchanges gas is still being built. Saccular development continues to roughly 36 weeks, and alveolarization carries on after birth.
Surfactant is made by type II pneumocytes. Small amounts can be detected from about 22 to 24 weeks, and the amount rises substantially toward term.
This explains the gradient. Lung maturity arrives in stages, so fewer weeks means less built air-sac tissue and less surfactant. RDS therefore becomes more common and more severe as gestational age falls. As the corrected-age note showed, the risk climbs as gestational age falls.
What does surfactant do, and what happens without it?
Once the lung is known to be short of surfactant, the question is what that shortage does to each breath.
Surfactant lowers surface tension at the air–liquid interface. Without enough of it, much higher pressure is needed to open each small airspace. Nothing holds the unstable units open at the end of expiration, so they collapse again.
The result is widespread atelectasis and reduced lung compliance. The result also includes ventilation–perfusion mismatch, hypoxemia, carbon dioxide retention and respiratory acidosis.
Why does every breath cost so much?
Collapse means every breath must reopen the lung, which raises the question of what that costs the infant.
The infant spends a large amount of energy reopening the lung with every breath. The infant tires within hours.
Birth adds a second burden. Fetal lung fluid must be absorbed while gas exchange starts, and the clearance of that fluid is less efficient in an immature lung. The first breaths must establish aeration in a lung that is still partly fluid-filled, as the golden-hour note also explained.
What does the effort look like?
The cost shows up as visible effort, so the question is what the effort looks like at the bedside.
An infant reopening collapsing airspaces with every breath shows that effort. The signs escalate as the effort becomes harder to sustain:
- a respiratory rate above 60 breaths per minute;
- retractions of the soft chest wall between the ribs, below the costal margin or over the sternum;
- nasal flaring, which reduces inspiratory resistance.
Cyanosis, pallor, lethargy, reluctance to feed and apnea are later signs. They belong to an infant who is tiring or already failing.
What does grunting do?
Grunting is one of these signs, so the question is what it does for the lung.
The grunt during expiration is produced by partial closure of the vocal cords. Partial closure holds air in at the end of expiration, so a small pressure stays in the airways. That is intrinsic positive end-expiratory pressure, the same pressure a ventilator provides as PEEP, but produced by the infant. Keeping the alveoli open at the end of expiration slows their collapse.
So grunting is a sign of disease that the infant is actively compensating for.
How is the effort scored?
The signs can be added up, so the question is what such a score can and cannot tell us.
Severity can be graded by scoring systems such as the Silverman–Andersen score, which sums the visible work of breathing. Any such score records effort, not gas exchange, so it is read together with saturation and blood gases. The examination shows how hard the infant is working.
How do the tests show that gas exchange has failed?
Effort is a first clue, and the question is what shows whether gas exchange has failed.
Investigations show whether gas exchange has failed and what the lung looks like. Preductal pulse oximetry on the right hand measures blood that has not yet passed the ductus arteriosus. It is combined with blood gas analysis, which may reveal hypercapnia with respiratory acidosis.
What does the chest X-ray show?
The X-ray shows what the lung looks like.
In surfactant deficiency the chest radiograph develops a reticulogranular or ground-glass pattern. It also shows air bronchograms, which are air-filled bronchi standing out against airless lung. In the most severe stage the lungs become diffusely opaque, and the cardiac border is hard to distinguish.
What does lung ultrasound show?
Ultrasound is a bedside alternative to the X-ray, and it is increasingly used.
A normal lung shows horizontal A-lines. RDS produces dense vertical B-lines. In severe disease the ultrasound shows a “white lung”. Because ultrasound can be repeated without moving a critically ill infant, it suits the bedside.
How is the lung supported?
The test results decide the treatment, so the question is how support is stepped up.
The treatment logic is a ladder. An infant who breathes but cannot keep the airspaces open receives nasal continuous positive airway pressure (CPAP). It delivers distending pressure through prongs or a mask, and it avoids an endotracheal tube. Pressure holds the airspaces open at the end of expiration, which is the job of PEEP. If CPAP fails, invasive mechanical ventilation becomes necessary.
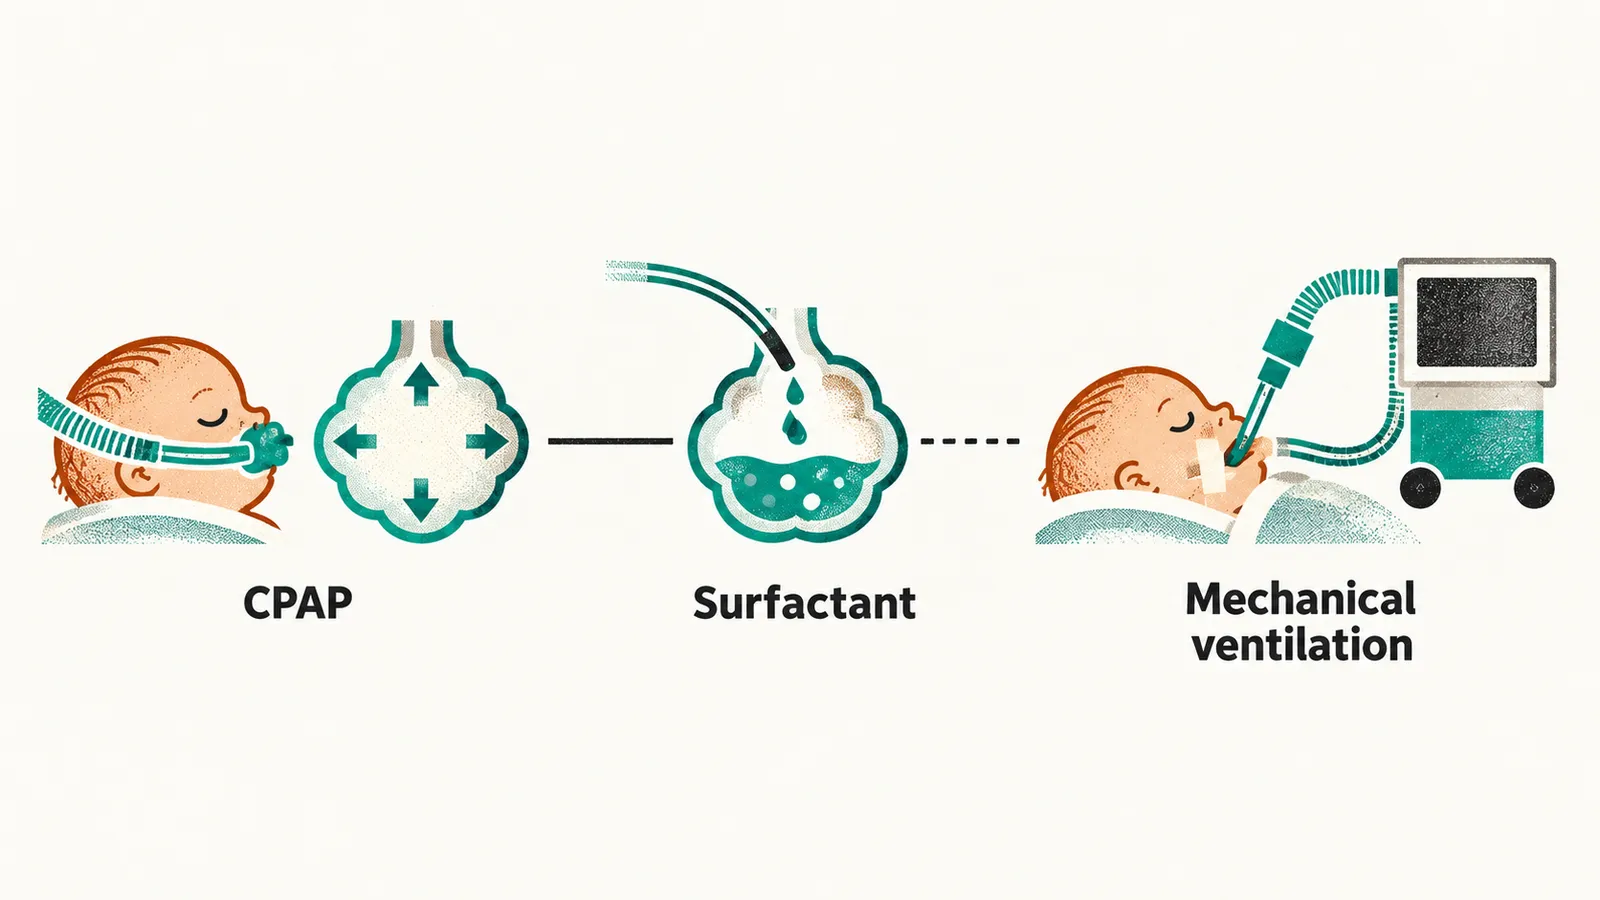
Surfactant treats the deficiency behind the airspace collapse, so replacing it treats the collapse itself.
Why not simply use more pressure?
Pressure has to be enough to hold the airspaces open but no more.
High pressures and large tidal volumes (the volume of each breath) injure the immature lung. Modern practice therefore aims for the gentlest support that maintains gas exchange.
Why does surfactant have to go down a tube?
Surfactant treats the collapse, so the question is how it reaches the lower airway.
Surfactant has to reach the lower airway. Nebulisation was not a reliable route, because much of the nebulised material deposits in the upper airway. Surfactant is instead instilled through an endotracheal tube or a thin catheter.
INSURE, which stands for intubation, surfactant, extubation, gives surfactant through a brief intubation. The tube is removed once the infant can continue on non-invasive support. An infant who already needs invasive ventilation receives surfactant through the existing tube.
What can the support itself damage?
The pressure that opens the lung can also rupture it, so the question is what that damage looks like.
Air leak is a complication that pressure can create. In a surfactant-deficient lung some regions over-distend while others stay collapsed. An over-distended airspace can rupture into the pleural space.
A sudden deterioration in oxygenation, heart rate or blood pressure during respiratory support raises the possibility of pneumothorax. It may require immediate drainage with a chest tube. The risk of air leak is one reason to prefer CPAP and shorter periods of invasive ventilation when the clinical situation allows.
Is every breathing pause a lung problem?
Pauses are another kind of breathing problem, so the question is whether they come from the lung.
Not every breathing problem in a preterm infant comes from the lung. Apnea of prematurity, pauses in breathing, has a separate mechanism: an immature respiratory control center. The pauses occur even without worsening parenchymal disease.
Apnea of prematurity is common at the earliest gestations. It usually improves as the infant approaches term, because respiratory control matures around 34 to 35 weeks.
How are the pauses treated?
A control problem needs a different treatment, so the question is what treats it.
Apnea is treated with respiratory support, positioning and caffeine citrate. Caffeine citrate stimulates respiratory drive and reduces apneic episodes. A proposed route is stimulation of the respiratory center, which strengthens breathing drive.
The standard reference dosing is a loading dose of 20 mg/kg, then a maintenance dose of 5 mg/kg once daily. Maintenance may be increased to 10 mg/kg per day if apnea persists. Doses are prescribed by unit protocol, not by the study material.
The large trial that established neonatal use reported less bronchopulmonary dysplasia. It also reported a lower rate of death or neurodevelopmental disability at 18 to 21 months.
How does acute lung disease become chronic?
A lung that survives the acute phase can keep needing support, so the question is what turns this into chronic disease.
Bronchopulmonary dysplasia (BPD) is the chronic lung disease of prematurity. It is the chronic respiratory consequence in infants who survive immature-lung disease and prolonged oxygen or ventilatory support. Acute RDS can resolve while the infant remains dependent on respiratory support and saturation monitoring for weeks or months.
BPD is cumulative injury to a lung that is trying to grow. Alveolarization continues after birth, so the injury lands on a lung still under construction. The contributors are oxygen exposure, ventilator-induced stress, infection, inflammation, fluid overload and a persistent ductus arteriosus.
How is bronchopulmonary dysplasia defined?
Chronic disease needs a definition before it can be counted.
Definitions of BPD vary, so reported incidence differs widely. Among extremely preterm infants surviving to 36 weeks postmenstrual age, about half meet the oxygen-use definition of BPD. Postmenstrual age is gestational age at birth plus the completed weeks since birth, as the corrected-age note explained.
What does chronic lung disease cost the infant?
Once the disease is defined, the question is what it does to the infant’s course.
Severe disease prolongs admission and delays feeding autonomy. It may require discharge with home oxygen or technology dependence. In the most severe cases, tracheostomy and long-term ventilatory support may be required.
Respiratory support and feeding are connected: an infant working hard to breathe has little energy left to feed.
How do the lung and the ductus affect each other?
The chronic lung and the circulation interact, and the last question is how closing the ductus helps the lung and what it does to the gut.
RDS and BPD interact with the cardiovascular transition. Lung disease promotes ductal patency. A hemodynamically significant patent ductus arteriosus increases pulmonary blood flow and worsens the pulmonary edema that the immature lung already struggles with.
The circulation that determines lung edema also determines bowel perfusion. So the treatment of the ductus and the risk of necrotizing enterocolitis meet at bowel perfusion. How does closing the ductus help the lung, and what does it risk for the bowel?