
Feeding a preterm infant is a developmental problem before it is a calorie problem. The infant needs substrates for rapid growth, but the coordination needed to feed is incomplete, and the tolerance of the immature intestine is incomplete too. So the plan combines human milk, tube feeding, cautious progression of enteral volume and intravenous nutrition, and it watches throughout for necrotizing enterocolitis (NEC).
Before birth the placenta fed the infant. After birth the gut has to take over, but it is still maturing. The milk that trains the gut is also one of the things that can injure an immature bowel wall. The question is therefore not whether to feed, but how to feed without injuring the gut.
Why can a preterm infant not simply feed at the breast?
The first obstacle is the mouth. Feeding needs sucking, swallowing and breathing to be timed together, and that coordination is an immature system that matures late, as the corrected-age note explains. It is not reliably mature until about 34 weeks postmenstrual age, which is gestational age plus the completed weeks since birth, as that note set out.
Younger infants may suck non-nutritively, but they cannot transfer a full feed safely. The suck, swallow and breathe sequence can become discoordinated, and the result is aspiration or desaturation. So a very preterm infant usually cannot breastfeed directly, even when human milk is strongly preferred.
How is milk given, and why is human milk preferred?
A tube solves the problem of the mouth, but the milk still has to be chosen. The mother expresses milk, and it is given through a nasogastric or orogastric tube. When maternal milk is not available, donor human milk is the preferred substitute. So the route is adapted to the infant’s maturity, while the nutritional substrate stays as close as possible to human milk.
Why this preference? Human milk feeding is associated with lower NEC risk than formula in preterm infants. Lower NEC risk is one reason human milk is preferred when available. One proposed route is that human milk carries components that can modify the gut’s microbiota, but this is an association, not a proven cause.
Why does the gut need time to be fed?
Human milk is preferred partly for its lower NEC risk, but the gut still has to adapt to any milk. Motility, enzyme activity, mucosal barrier function and the ability to tolerate a full enteral volume all develop after birth, and feeding is part of what drives that development. Early enteral feeding is thought to help by stimulating hormone secretion and motility.
That is why the feed starts small. Tiny early enteral feeds are often called minimal (trophic) enteral feeding. The enteral volume is then increased slowly. Small feeds expose the gut to milk and support mucosal adaptation.
Why is intravenous nutrition needed as well?
Small feeds cannot meet the whole need, so the rest comes through a vein. Practice combines parenteral nutrition, given intravenously, with the tiny early enteral feeds. Intravenous nutrition supplies what the gut cannot yet absorb safely. The enteral feeds are kept alongside it because they have trophic effects that can reduce some intestinal problems caused by total parenteral nutrition. The intravenous part of the plan depends on reliable access to a vein.
Where does the line go?
The vein has to be reached, and the first route is the umbilical vein. Immediately after birth it offers rapid central access for fluids and parenteral nutrition, and umbilical venous catheters are a standard route in the NICU. The catheter is usually kept for about five to seven days.
A percutaneously inserted central catheter is a thin line passed through a peripheral vein into a central vein. It is used for prolonged support.
What does each line cost?
Every line is a route for infection. Bloodstream infection risk rises with the dwell time of the umbilical venous catheter, because a line that stays longer is a longer exposure. Many units therefore follow a recommendation to remove the umbilical venous catheter at or before seven days if it is still needed.
Each line adds infection and vascular risk, and central lines in the NICU are associated with significant morbidity because of bloodstream infection. So the indication and duration of every line are reviewed daily.
What is necrotizing enterocolitis?
The lines and feeds exist to protect the bowel, and the disease they protect against is NEC. It is inflammatory necrosis of the immature bowel: an acute inflammatory disease in which the bowel wall becomes injured and necrotic. It most often affects the terminal ileum and proximal colon. The feeding plan watches for it.
Why does the bowel get injured?
NEC is one injury with several contributors. Its cause is multifactorial, and its pathogenesis is still poorly understood, so no single cause explains it. Feeding is a contributor rather than the cause.
The immature mucosal barrier and immune response react abnormally to enteral substrate. The premature gut’s response to bacterial colonization is described as hyper-reactive. Antibiotic exposure and other factors alter the developing intestinal microbiome, the community of microorganisms that colonizes the gut. Infection and dysbiosis, a disturbed balance of that community, are thought to amplify inflammation.
The bowel’s blood flow is another contributor. Reduced bowel perfusion makes the bowel wall more vulnerable to ischemic injury, and one cause is ductal steal. As the ductus note explains, an open ductus can divert blood away from the bowel. A hemodynamically significant patent ductus arteriosus diverts blood away from the organs.
How common is NEC, and how often is it fatal?
NEC affects roughly 7% to 10% of very-low-birth-weight infants. Reported mortality is in the region of 20% to 30% overall. Pooled mortality is around 35% for infants needing surgery, and about 50% in extremely low-birth-weight infants with surgical disease. These figures vary by population and era.
Prevention and early recognition dominate feeding decisions in the neonatal unit.
Why do the first signs look like everything else?
The early picture is non-specific, so the team cannot rely on one sign. Preterm infants often show non-specific systemic signs first: temperature instability, more frequent apnea, lethargy, poor perfusion, hypotension, metabolic acidosis, respiratory failure or shock. NEC signs are non-specific and can be confused with sepsis.
Sepsis, NEC and metabolic disease can all present as an infant who has suddenly become less stable, and they may coexist. The abdomen and imaging help separate them. Cultures, blood tests and repeated examination remain necessary.
What does the bedside examination show?
The abdomen gives the specific signs that the general picture lacks. These point to bowel disease:
- abdominal distension;
- increasing gastric residuals, meaning milk still in the stomach when the next feed is due, which suggests the gut is not moving milk on in time, and motility is one of the functions still maturing;
- bilious (bile-stained) drainage from the feeding tube;
- blood in the stool;
- abdominal tenderness;
- abdominal wall discoloration.
What does the X-ray show?
Abdominal radiography may show pneumatosis intestinalis, gas within the bowel wall. It is thought to follow microperforation, and it is the radiographic hallmark of NEC. Gas may also appear in the portal venous system.
Free intraperitoneal air indicates perforation. That converts the illness into a surgical emergency.
How is the severity graded?
The stages of injury set how the treatment escalates. Staging systems such as the modified Bell classification separate suspected disease, definite disease with characteristic intestinal signs, and advanced disease with systemic deterioration, shock or perforation. The practical learning boundary is that distinction rather than every numbered substage. It corresponds to escalation of treatment and to the decision about surgery.
How is NEC treated?
Treatment addresses the injured bowel, the possibility of infection and the systemic illness at once. It combines several steps:
- stop enteral feeding, so the injured bowel is no longer challenged metabolically;
- switch nutrition to total parenteral support while enteral feeding is held;
- start broad-spectrum antibiotics while cultures are pending, because the signs can be confused with sepsis;
- support circulation and ventilation, treating shock, acidosis and respiratory failure.
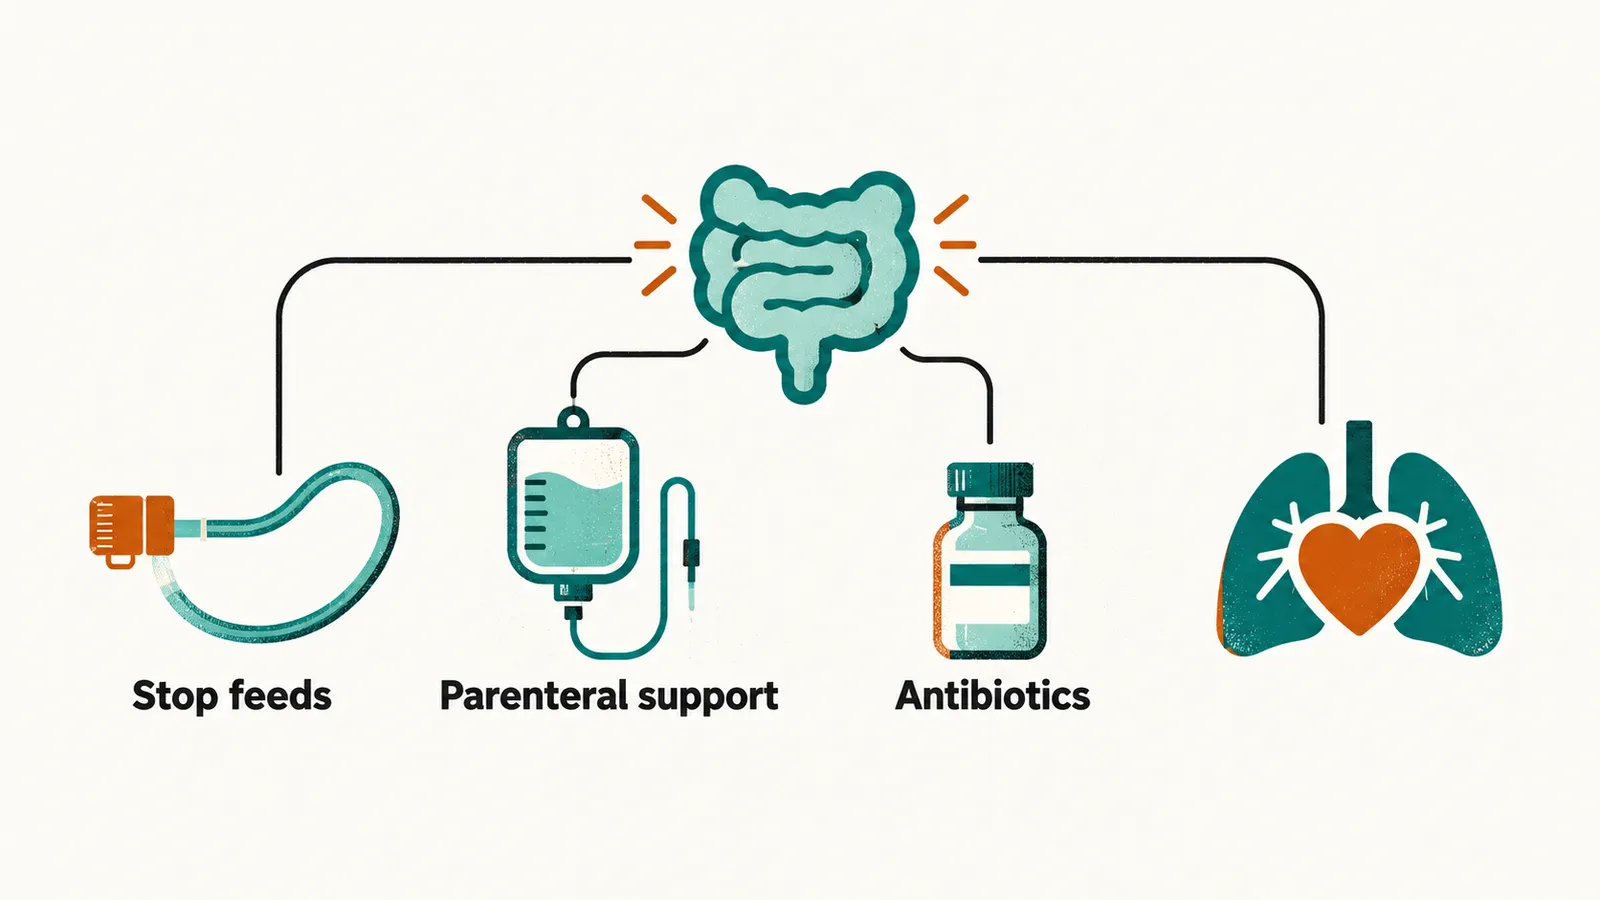
The infant is reassessed repeatedly, because deterioration can be rapid.
Why must perforation not be missed?
Treatment is aimed at stopping progression before perforation. Progression to perforation is the event that must not be missed. Perforation requires drainage or resection of necrotic bowel. Extensive resection leaves infants at risk of later strictures and short-bowel syndrome. The aim is to stop progression before tissue is lost.
Why is the ductus left open during NEC?
The drugs used to close the ductus reduce bowel blood flow, so the bowel’s needs come first. Indomethacin and ibuprofen close the ductus by inhibiting prostaglandin synthesis. As the ductus note explains, they also reduce bowel and renal perfusion. In the presence of active NEC they may worsen ischemia or perforation.
Closure is therefore deferred and the patent ductus is managed supportively. The team may have to accept an open ductus temporarily rather than treat the heart at the bowel’s expense.
Why does NEC reach beyond the bowel?
Severe intestinal inflammation is not confined to the abdomen. Shock, acidosis and circulating inflammatory mediators are associated with white-matter injury, and as the brain-injury note explains, low blood flow and inflammation can injure the white matter of the preterm brain even without bleeding. White-matter injury is one reason NEC matters well beyond the bowel.
Why do infection and NEC look the same?
The damaged bowel wall can let organisms into the circulation. That bloodstream infection can be clinically indistinguishable from NEC. Infection may be the cause, a consequence, or clinically indistinguishable from NEC. So cultures are taken and antibiotics started before the two can be told apart. Why are preterm infants so easily infected in the first place?