The previous note described what celiac disease does: it is a permanent, immune-mediated intolerance of gluten, and it damages the mucosa of the small intestine. The question now is how that is proved in a child.
Two things mark the disease. One is the immune response to gluten, which shows in the blood as antibodies. The other is the damage that response leaves in the lining of the small intestine, which shows under the microscope. A blood test is easy; a biopsy is invasive. So diagnosis works as a ladder. It starts with serology. The biopsy is added when the blood result cannot carry the diagnosis alone. Since 2020, a defined group of children can be diagnosed without a duodenal biopsy.
Two rules govern the whole process.
- Rule 1: the child must be eating gluten in normal amounts when the tests are taken. The antibodies and the lesion both follow the response to gluten. An already-restricted diet can normalize both the antibodies and the histology, and that produces a false negative.
- Rule 2: the antibody titre decides whether a biopsy can be avoided. What counts is the measured level, not merely whether the result is positive.
Who is tested?
If the disease can be silent, who should be looked for before symptoms point to it? Testing is indicated for three groups, and they are the children in whom the disease is more likely than in others:
- children with suggestive symptoms;
- children with associated conditions;
- first-degree relatives of a person with celiac disease.
The suggestive symptoms include chronic diarrhea, faltering growth, unexplained iron-deficiency anemia, and the other presentations described in Celiac Disease in Children.
The associated conditions are:
- type 1 diabetes;
- autoimmune thyroid disease;
- Down syndrome;
- Turner syndrome;
- Williams-Beuren syndrome;
- IgA deficiency.
Several of these, the autoimmune ones, are thought to share a genetic susceptibility with celiac disease.
The associated-condition group and the first-degree-relative group include children with no symptoms at all. In them the damage can exist without symptoms, so testing is how it is found. Testing these asymptomatic groups is how the silent form of the disease is found.
What is tested first, and what confirms it?
Once a child is to be tested, what is measured? The first-line serology is total IgA plus anti-tTG IgA. Anti-tTG IgA is an IgA-class antibody against tissue transglutaminase, the enzyme at the centre of the disease mechanism. Total IgA is included because the test reads an IgA-class antibody, so selective IgA deficiency produces false-negative results. If total IgA is low, screening switches to an IgG-based test: anti-tTG IgG, anti-deamidated gliadin peptide IgG, or EMA IgG.
Anti-endomysial antibodies (EMA) are a highly specific confirmatory test, and they are used second. Because the test is highly specific, it confirms; it is not the first screen, since it is costlier and more labour-intensive than anti-tTG IgA. It also relies on a demanding technique whose reading depends on the observer. That is why EMA is best performed in an experienced laboratory.
When can the biopsy be skipped?
When the antibody is high enough, is a biopsy still needed? The 2020 ESPGHAN (European Society for Paediatric Gastroenterology, Hepatology and Nutrition) guideline allows diagnosis without a duodenal biopsy when two criteria are met:
- anti-tTG IgA is at least 10 times the upper limit of normal, and
- EMA is positive in a second serum sample.
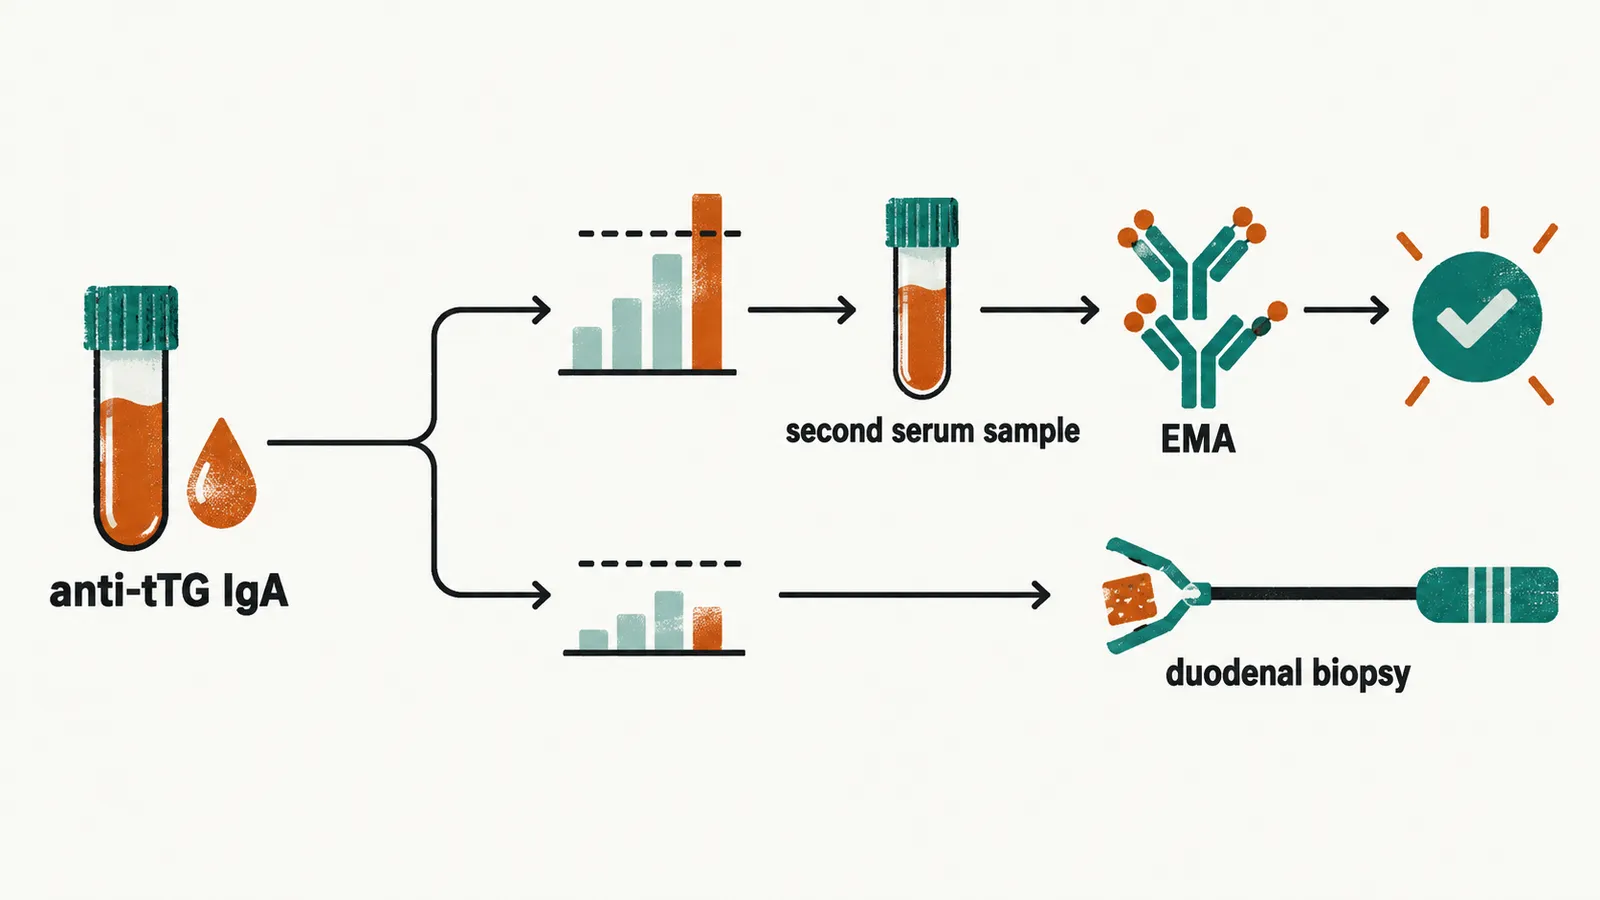
The upper limit of normal is the top of the laboratory’s reference range for the assay. The threshold is 10 times that limit, not simply “positive”. Below that value the false-positive rate is high enough that a biopsy is required, even when EMA is positive.
Two things that might be expected are no longer required. HLA typing is not a requirement for a no-biopsy diagnosis. Neither is the presence of symptoms: symptoms add little to diagnostic accuracy. So the no-biopsy pathway can be used in asymptomatic children, with the same criteria.
Because the numeric threshold is what makes the diagnosis, the assay matters. Some laboratories can only report a value above the measuring range. Such a result cannot show whether the 10-times line was reached. The guideline therefore requires an assay with a calibration curve whose range includes the 10-times-upper-limit value.
When is a biopsy still needed, and how is it taken?
When the rule cannot be used, the biopsy is required. The common thread is that the number or the confirmation is missing, so serology cannot carry the diagnosis alone. A biopsy is required in these cases:
- anti-tTG IgA is positive but below 10 times the upper limit of normal;
- serology is equivocal or discordant;
- EMA is negative;
- in every case, the child is IgA-deficient and tested positive on an IgG-based test.
Biopsies are taken during a gluten-containing diet. The protocol is to take at least four specimens from the distal duodenum and at least one from the duodenal bulb. The reason is that the lesion is patchy and can spare the bulb or spare the distal duodenum.
The same patchiness explains another point. A normal endoscopy does not exclude the diagnosis: the bulb and distal duodenum can look unremarkable while the histology is diagnostic. That is why the biopsy protocol is specified rather than left to the endoscopist’s impression.
A biopsy is preferred even when serology would permit skipping it. When histological proof is likely to be needed later to persuade the family to commit to a lifelong diet, the biopsy is preferred.
Where does HLA typing fit?
A blood test remains that does not rely on the child eating gluten: HLA typing. HLA-DQ2 and HLA-DQ8 are needed to display the gluten peptides to the immune system, yet many healthy people carry them. So typing belongs with equivocal cases, not first-line testing. These haplotypes are absent in only a small minority of people with celiac disease. Their absence therefore makes the diagnosis very unlikely, and that is the one question typing answers. Their presence confirms nothing, because the haplotypes are too common in the general population.
How is the biopsy read?
What does the pathologist report? The biopsy is graded with the modified Marsh-Oberhuber classification, which runs from normal mucosa to total villous atrophy. Flatter villi mean less absorptive surface; in total villous atrophy they are completely flattened. Each step of the scale adds one more feature of the same immune injury.
| Grade | Name | What is seen |
|---|---|---|
| 0 | Normal | Normal mucosa |
| 1 | Infiltrative | Normal villous architecture with increased intraepithelial lymphocytes |
| 2 | Hyperplastic | Increased intraepithelial lymphocytes with crypt hyperplasia; villi still present |
| 3 | Destructive | Villous atrophy with crypt hyperplasia: the typical celiac lesion |
Grade 3 is subdivided: 3a is mild, 3b is moderate, and 3c is total atrophy.
After the diagnosis
Whichever route confirms it, the diagnosis of celiac disease commits the child to a lifelong gluten-free diet. Once the diagnosis is made, what exactly must the child avoid, and how is the diet checked over the years? That is the subject of Treating and Monitoring Celiac Disease.