What is inflammatory bowel disease, and what makes the pediatric form different?
The gut wall has layers: the mucosa on the inside, and muscle and an outer coat beyond it. Inflammatory bowel disease (IBD) is chronic, relapsing inflammation of the gastrointestinal tract, and its cause is unknown. It is classified by its anatomical and histological pattern, because the forms are told apart by where they lie and which layers they involve. The three categories are ulcerative colitis (UC), Crohn’s disease (CD) and IBD-unclassified (IBDU).
In the work-up of chronic diarrhea in children, IBD is the inflammatory arm. The malabsorptive arm is celiac disease. The Definitions and Mechanisms of Chronic Diarrhea in Children note sets out these two patterns.
In children, IBD differs from adult disease in two ways.
- The presentation is often subtle and slowly progressive rather than dramatic.
- The inflammation interferes with growth during the years when growth is the point. Growth failure is thought to come from chronic undernutrition, through reduced intake and losses through the inflamed gut, and circulating inflammatory mediators are proposed contributors.
Both features push the diagnostic threshold down. The working rule in pediatric IBD follows: the more carefully you look, the more you find.
How do Crohn’s disease and ulcerative colitis differ?
Both are inflammation of the wall. They differ in how deep it goes and how far it spreads.
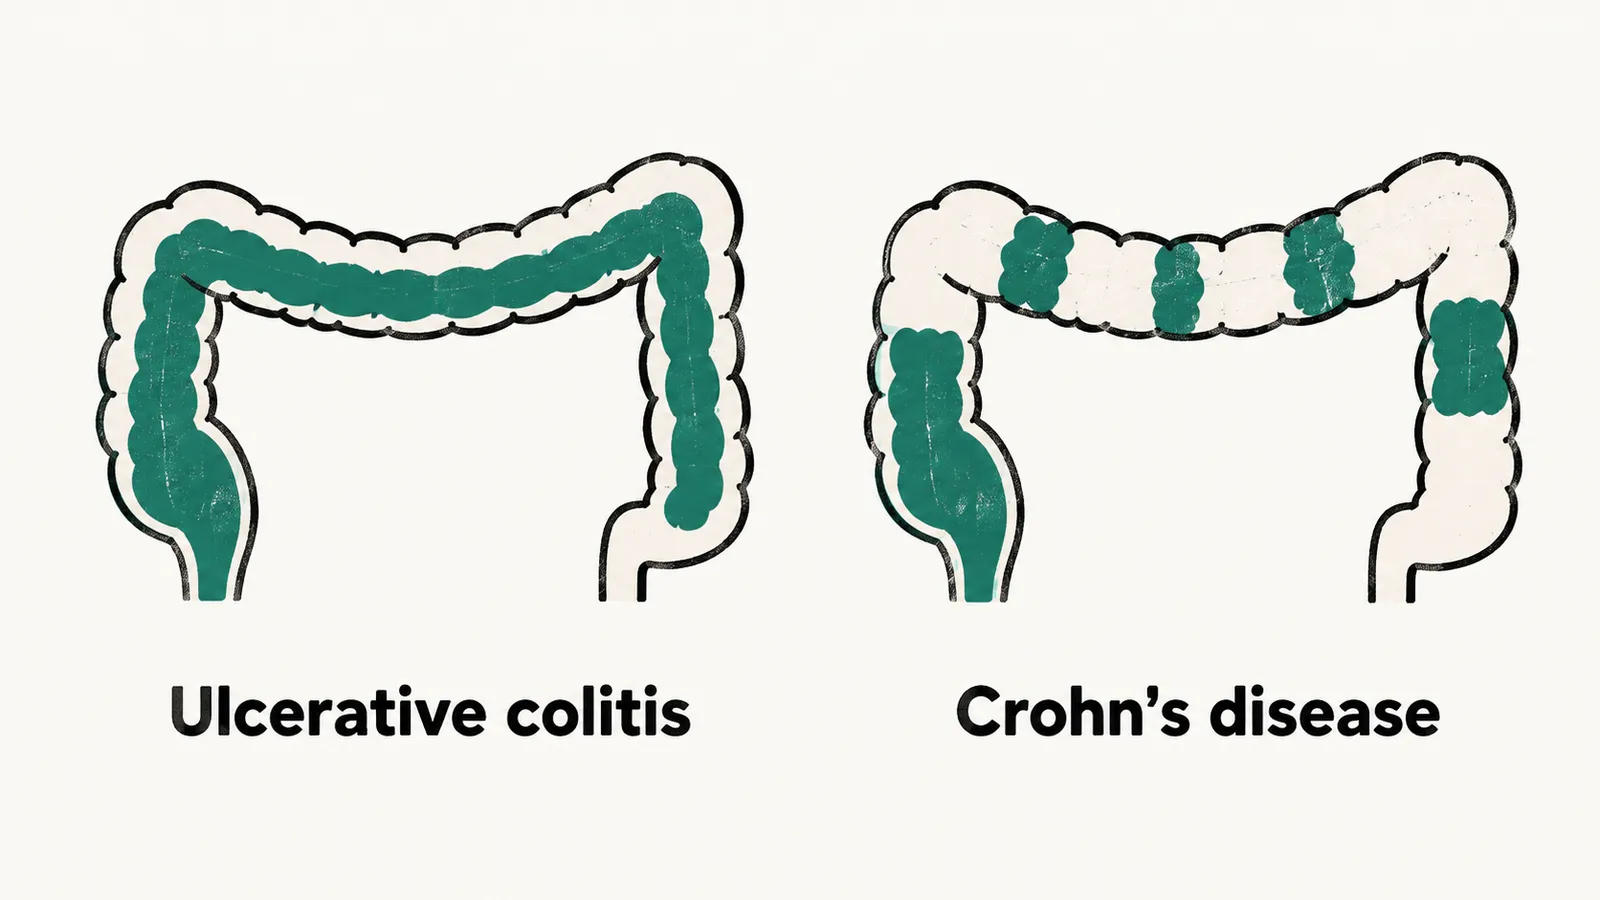
UC stays in the mucosa. It is continuous: it starts at the rectum and extends proximally without gaps. It lives in the colon, and its ulcers are superficial.
CD is patchy. Diseased segments alternate with normal bowel (skip lesions), and it can occur anywhere from mouth to anus. It is also transmural, involving the full thickness of the bowel wall. A process that runs through the whole wall produces deep, linear ulcers. It also explains the complications: the lumen narrows into strictures, and the inflammation can break through the wall to form fistulas and abscesses, including in the perianal region.
| Feature | Ulcerative colitis | Crohn’s disease |
|---|---|---|
| Distribution | Continuous, starts at the rectum, extends proximally | Patchy, skip lesions, anywhere from mouth to anus |
| Depth | Mucosa only | Transmural, full thickness of the bowel wall |
| Typical site | Colon | Terminal ileum, colon, upper GI tract, perianal region |
| Ulcers | Superficial | Deep and linear |
| Complications | Acute severe colitis, eventually colectomy | Strictures (narrowed segments), fistulas (abnormal tracts between bowel and other organs or skin), abscesses, perianal disease |
What if it fits neither, and how is the disease described?
Some children show features of both UC and CD at diagnosis. This is IBDU. It is a real category, not a diagnostic failure. The pattern may not have settled early on, and some IBDU children are reclassified as UC or CD as the disease declares itself over time.
To describe a child’s disease, the current pediatric standard is the , a pediatric modification of the Montreal classification. It records the phenotype: where the disease sits and how it behaves. A pediatric version exists because children differ from adults in how their disease presents.
Two findings point toward CD. Perianal disease (skin tags, fissures, fistulas, abscesses) points to CD because UC does not cause it. Anal disease is a full-thickness complication. Upper GI involvement is also a Crohn’s pattern, since CD can reach any segment. It is common enough in children that the diagnostic endoscopy includes the upper tract even when symptoms are colonic.
Who is diagnosed, and at what age?
Pediatric-onset IBD is being diagnosed more often. The increase is largest in the youngest children.
Very early onset IBD means onset before 6 years of age. It accounts for roughly 3–15% of pediatric IBD across reported cohorts.
Onset before 2 years is a distinct problem. A substantial minority of these children have a monogenic defect (a single-gene disorder) of immunity or epithelial function rather than idiopathic IBD. More than 70 genes are implicated. Such defects need a different treatment strategy, and the right choice depends on finding the gene. So very early onset disease, particularly with atypical features, prompts genetic testing and specialist referral rather than the standard work-up. The atypical features are:
- severe perianal disease
- recurrent infection
- a family history suggesting immunodeficiency
When should a child be suspected, and what does it look like?
Because the pediatric presentation is subtle and slowly progressive, the set of triggers is broader than bloody diarrhea. Any one of several quiet patterns can be the whole presentation. Suspect IBD in these situations.
- Chronic diarrhea with blood or mucus, with abdominal pain, urgency and tenesmus (a painful, persistent urge to pass stool).
- Unexplained delay in weight gain or linear growth, especially with fever or laboratory markers of malnutrition or inflammation.
- Chronic diarrhea without blood or mucus, particularly if nocturnal and accompanied by systemic signs or abnormal laboratory results.
- Severe, disabling abdominal pain with nocturnal symptoms and malnutrition.
- Any of the above together with extraintestinal manifestations: arthritis, uveitis, erythema nodosum, pyoderma gangrenosum or chronic liver disease.
Growth failure and nocturnal diarrhea carry the most weight in children. Both are unusual in functional and benign patterns, which is the red-flag logic of the Clinical Approach and Work-up of Chronic Diarrhea in Children note.
The symptoms depend on where along the gut the disease sits.
- Stomach and duodenum: nausea, vomiting, epigastric pain, poor appetite.
- Small bowel: malabsorption with chronic diarrhea and weight loss, pain and fever. A narrowed lumen can also cause sub-occlusion, with vomiting and distension.
- Colon: bloody diarrhea, urgency, tenesmus and pain. Inflamed colonic mucosa leaks blood and mucus, which is why the stool shows them.
- Perianal region: skin tags, fissures, fistulas, abscesses.
What happens outside the gut?
IBD is not confined to the intestine. It is an immune-mediated inflammation, so it can reach other organs. Extraintestinal features sometimes precede the GI ones and bring the child to medical attention first.
- Skin: erythema nodosum (tender red nodules under the skin) and pyoderma gangrenosum (painful ulcerating skin lesions).
- Joints: arthritis, arthralgia, sacroiliitis (inflammation of the joints between spine and pelvis).
- Eyes: uveitis, , iritis.
- Liver and biliary tract: including primary sclerosing cholangitis (chronic inflammatory disease of the bile ducts).
- Mouth: recurrent aphthous ulcers.
- Kidney: nephrolithiasis (kidney stones).
Erythema nodosum and pyoderma gangrenosum are associated with IBD but are not specific to it. A child with either is therefore not assumed to have IBD. Erythema nodosum also occurs in streptococcal infection, sarcoidosis and tuberculosis. Pyoderma gangrenosum also occurs in other immune-mediated diseases.
How is the diagnosis made?
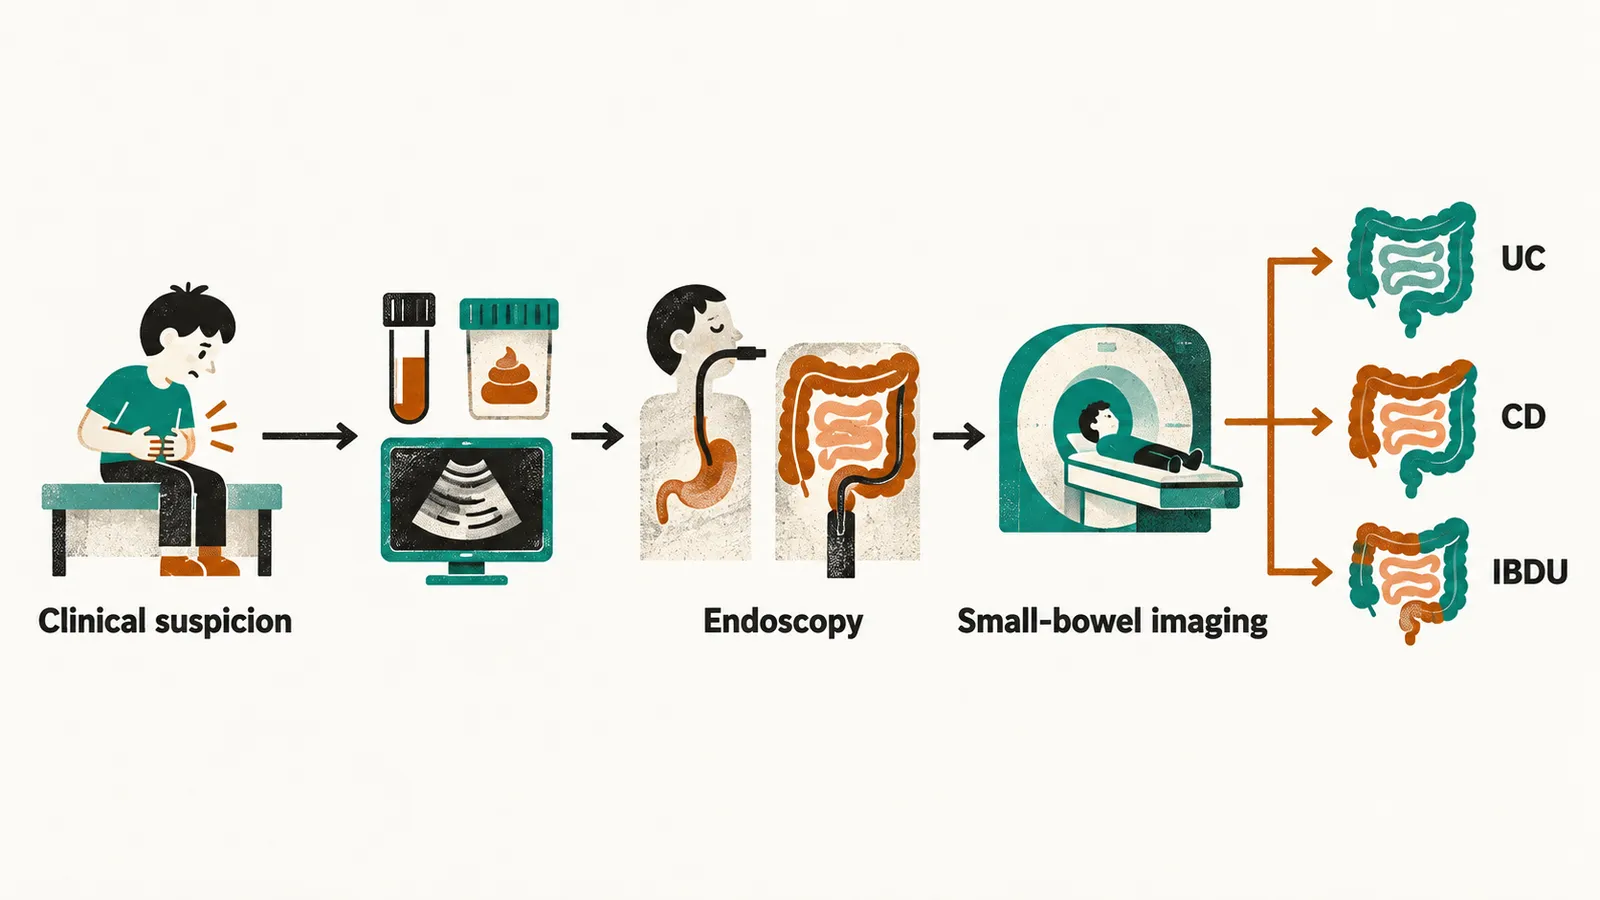
The European framework is the of ESPGHAN. They require the whole GI tract to be assessed before IBD can be classified. The reason is that a similar colitis picture can come from UC, CD or IBDU, and the answer may sit in the segments not yet examined. The steps are these.
- Clinical suspicion, from the trigger set above.
- Non-invasive work-up: blood count, CRP and ESR, iron studies, albumin and nutritional markers, fecal calprotectin and abdominal ultrasound. These show whether inflammation is present and what it has cost the child.
- Endoscopy: upper GI endoscopy and ileocolonoscopy (colonoscopy continuing into the terminal ileum), with segmental biopsies from the terminal ileum and from every colonic segment. Segmental sampling matters because CD is patchy.
- Small-bowel imaging: MR enterography (MRI of the small bowel), ultrasound or capsule endoscopy (a swallowed camera capsule). It is done when small-bowel involvement is suspected, and in all children unless the endoscopic and histological picture is typical of UC. Imaging reaches the small bowel that the colonoscope cannot.
- Classification as UC, CD or IBDU from the combined endoscopic, histological and imaging findings.
Skipping some of these steps has a known cost. Skipping upper endoscopy in suspected pediatric IBD is a known way to miss upper GI Crohn’s disease. Skipping small-bowel imaging is a known way to miss small-bowel disease the colonoscope cannot reach.
What does fecal calprotectin tell, and what can it not tell?
The non-invasive step does a great deal of the work, so it is worth understanding. Fecal calprotectin is a calcium- and zinc-binding protein. It makes up a large share of neutrophil cytosolic protein. In inflamed intestinal mucosa, neutrophils (the white cells of acute inflammation) migrate into the lumen and release it. The stool concentration therefore reflects the intensity of neutrophilic inflammation. It is the most useful non-invasive biomarker in pediatric IBD.
But it marks neutrophils, not IBD, so fecal calprotectin is also unspecific. Its reference values fall steeply with age. In the first year of life, values of several hundred µg/g can be found in healthy infants. From about 4 years of age the upper limit of normal is usually taken as roughly 50 µg/g. Published age-banded upper limits vary substantially between studies. One healthy-child dataset gave 910 µg/g at 0–12 months, 286 µg/g at 1–4 years and 54 µg/g at 4–12 years, and other cohorts report much lower figures. So a result must be read against the age band and the clinical picture, not against a single cutoff.
Many processes that send neutrophils into the gut can raise the value, and some drugs are associated with raised values. Raised values also occur in:
- bacterial and viral gastroenteritis
- Giardia infection
- food allergy
- cystic fibrosis
- untreated celiac disease
- NSAID or proton-pump inhibitor use
- young children generally
The celiac entry has a practical consequence. A raised value in a child with chronic diarrhea does not establish IBD until celiac serology has been checked (see Diagnosing Celiac Disease in Children).
The first bowel movement of the day is the preferred sample. Assay choice and sample handling both affect the result.
What predicts a more aggressive course?
The findings at diagnosis suggest how the disease will behave. In pediatric CD, these features predict a more aggressive course:
- extensive ileal involvement
- perianal disease
- stricturing behavior (disease that narrows the bowel)
- deep colonic ulcers
- upper GI involvement
- high corticosteroid requirement at presentation
- high serological titers
These features push treatment decisions toward earlier and more effective therapy rather than a slow step-up. They are also the reason the extent of disease is mapped at diagnosis rather than assumed.
Once the extent and behavior of the disease are mapped, how is the inflammation brought under control and kept there in a growing child? The Treatment and Monitoring of Pediatric Inflammatory Bowel Disease note takes up that question.