What is celiac disease, and why does the lining matter?
Celiac disease is a permanent, immune-mediated intolerance of dietary gluten in genetically predisposed people. Gluten is a protein in wheat, barley and rye. Three things meet: a trigger (gluten), a susceptible host (the genes) and a target, the mucosa of the small intestine. The result is damage to that lining.
The word permanent carries the clinical weight. The mucosa recovers when gluten is removed, but the intolerance does not go away. The damage depends on gluten reaching the tissue, so taking gluten away lets the lining heal. The predisposition is inherited, so it stays. That is why treatment is lifelong rather than a course.
This gives a useful pearl. A child who is told they have outgrown celiac disease has either been misdiagnosed or has abandoned the diet. The diet hides the disease; it does not remove it.
How does gluten damage the lining?
The disease arises where gluten meets tissue transglutaminase (tTG), an enzyme, and HLA molecules that display peptide fragments to T cells. It happens in four steps.
- Gluten is partially digested in the lumen. It breaks into gliadin peptides that resist further breakdown.
- tTG deamidates glutamine residues on those peptides, converting them to glutamic acid. This change makes the peptides bind more tightly to HLA.
- The deamidated peptides bind with high affinity to HLA-DQ2 or HLA-DQ8 on antigen-presenting cells and are presented to CD4+ T lymphocytes.
- T-cell activation, with IL-15 signalling from the epithelium, drives a Th1-type inflammatory response.
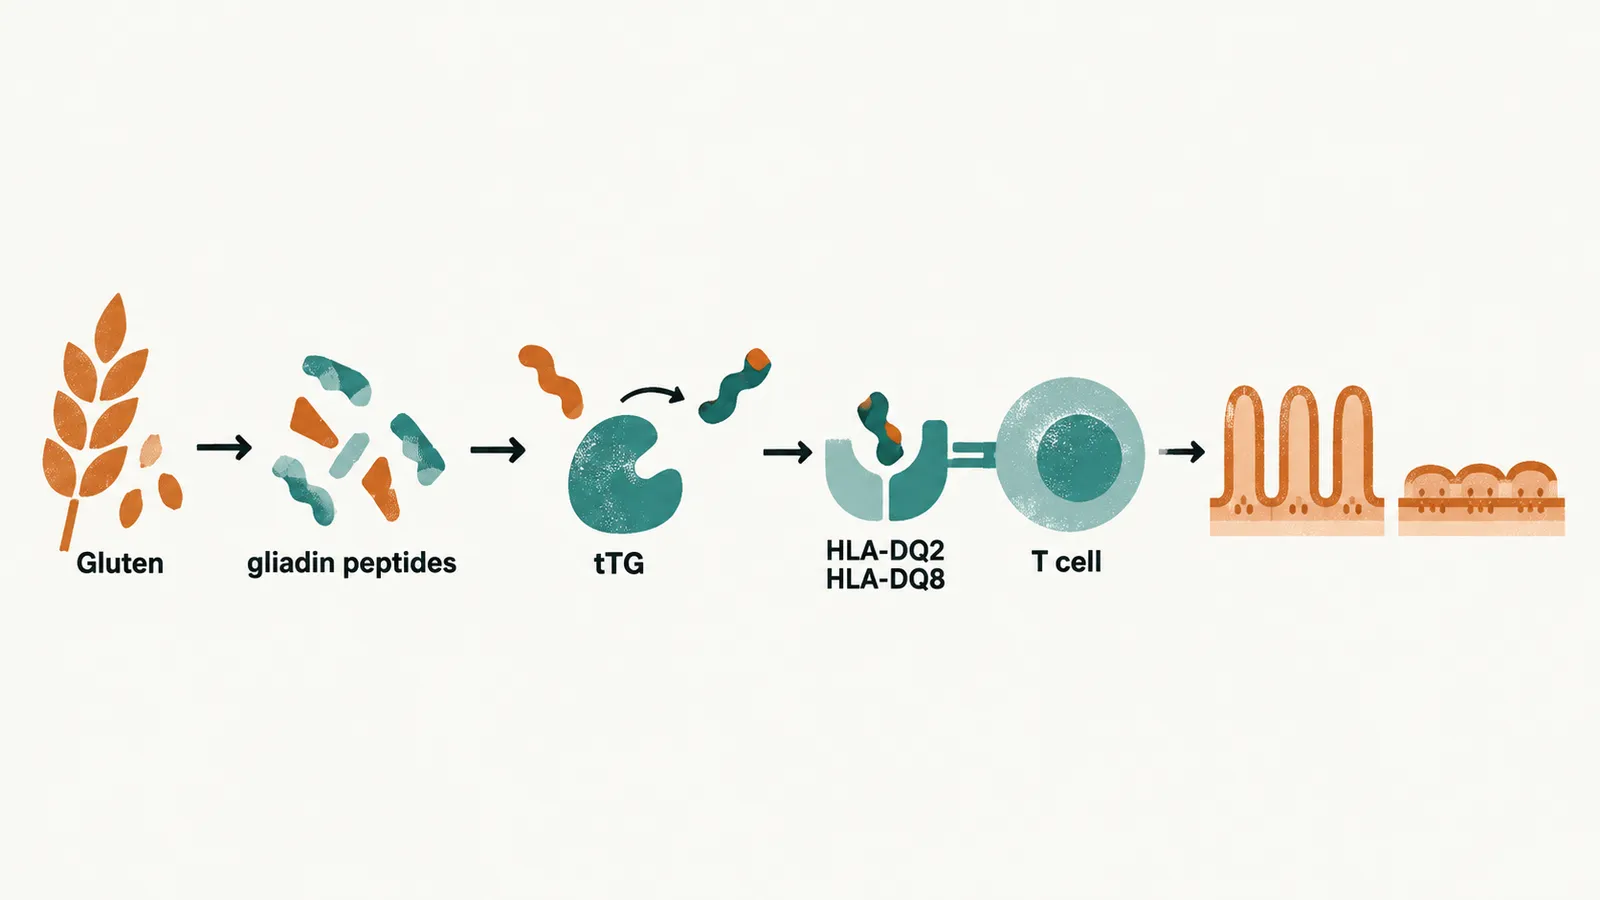
What does that response do to the lining? It flattens the villi, which cuts the surface available for absorption. It lengthens the crypts, which is described as a compensatory response to the loss of villi. And it destroys enterocytes.
A flat lining absorbs poorly, so food passes through unabsorbed. This is why celiac disease is the malabsorptive arm of chronic diarrhea in a child. Unabsorbed material in the bowel carries water with it, as explained in Definitions and Mechanisms of Chronic Diarrhea in Children. The usual presentation is prolonged loose stools, faltering growth and nutritional deficiencies.
The lesion is in the small bowel, so the first-line tests point to the duodenum rather than the colon. Celiac disease belongs in the differential of almost any child with chronic diarrhea, short stature or unexplained iron-deficiency anemia.
Why is the antibody anti-tTG, and what do the HLA genes add?
The enzyme tTG appeared in step 2. The same enzyme that modifies the peptide is also the target of the autoantibody response. Hence anti-tTG IgA is the serological marker of the disease.
Because the antibody follows the autoimmune process, serology tracks that process, not gluten intake directly. It falls as the mucosa heals on treatment.
Step 3 depends on the class II HLA haplotypes HLA-DQ2 and HLA-DQ8, the inherited combinations of HLA genes strongly associated with celiac disease. A person who carries one of them can display the peptides in this way. HLA-DQ2 or HLA-DQ8 is present in roughly 98% of people with celiac disease. In European patients, DQ2 is found in about 90% and DQ8 in about 5–10%.
Is carrying the haplotype enough? No. The same haplotypes are carried by a large minority of healthy people, with reported frequencies in general populations from roughly 30% to over 50%, depending on the population studied. Why a minority of carriers develop the disease is unclear.
This explains the main use of HLA typing. Absence of both haplotypes makes celiac disease very unlikely, because the display step cannot happen. So typing is used to exclude the diagnosis in a child whose serology is equivocal or whose biopsies were uninformative. A positive result means that the child belongs to a large group, most of whom never develop the disease. A positive HLA result never confirms the diagnosis. The 2020 ESPGHAN guideline no longer requires HLA typing for a serology-based diagnosis.
How common is it, and can it be prevented?
A pooled analysis of 275,818 people screened by serology found a global prevalence of 1.4% (95% CI 1.1–1.7%). Biopsy-confirmed disease was found in 0.7% (95% CI 0.5–0.9%) of 138,792 people tested. In the same analysis, prevalence was higher in children than in adults.
Most people with celiac disease are undiagnosed. The reason is that the classic diarrheal presentation is now the minority, as the clinical forms below show.
Italy has acted on this. A 2023 national law provides for population screening of children for celiac disease and type 1 diabetes. The school-age study behind that policy found an overall prevalence of 1.65% (95% CI 1.34–2.01%), with only about 40% of affected children already diagnosed before screening. Other European countries have not adopted universal screening. The Italian programme is a policy choice rather than a settled international standard.
Screening is a different question from prevention. No feeding strategy prevents celiac disease. Introducing gluten at any point between 4 and 12 months of age does not change overall risk, breastfeeding does not lower the risk, and no gluten dose has been shown to prevent the disease. Infant feeding is not modified with prevention in mind, including in a child with an affected first-degree relative.
What does it look like in a child?
If most affected children are undiagnosed, what are they presenting with? The disease is recognized in four forms, and only the first is defined by intestinal symptoms. The other forms explain why many affected children are found through growth, blood tests or screening rather than diarrhea.
| Form | What dominates | How it is found |
|---|---|---|
| Typical (classic) | Diarrhea, weight loss, anorexia, abdominal pain and distension, vomiting, sometimes irritability or personality change; onset follows gluten introduction | By the symptoms; once the usual pediatric presentation, now the minority |
| Atypical (non-gastrointestinal) | Consequences of malnutrition: short stature, iron-deficiency anemia that does not respond to oral iron, osteopenia, dental enamel defects; intestinal symptoms may be absent or minimal | By growth, blood tests or the extra-intestinal findings |
| Silent | Villous atrophy with positive serology in a child with no symptoms at all | Through screening of relatives, children with type 1 diabetes, or a population programme |
| Potential | Positive serology with normal or minimally abnormal histology | By serology; it is a pre-stage that may evolve, so it needs surveillance rather than dismissal |
The typical form follows from the mechanism. Gluten is the trigger, so symptoms follow its introduction, and malabsorption produces the diarrhea and weight loss. In the atypical form the same malabsorption shows through its consequences. Iron is not absorbed through the damaged duodenum, so the anemia does not respond to oral iron, and the nutritional deficiencies lead to osteopenia. The silent form shows that the lesion and the antibody can be present without symptoms, and it is found through screening of relatives, children with type 1 diabetes, or a population programme.
Growth failure is the feature that most often gives the diagnosis away in a child, because a child who cannot absorb nutrients does not grow as expected. So suspect celiac disease in any infant or child not growing as expected, and in any child with iron-deficiency anemia that fails to respond to iron replacement. The growth chart and the red flags are set out in Clinical Approach and Work-up of Chronic Diarrhea in Children.
Recurrent aphthous stomatitis, abdominal pain and diarrhea together raise the possibility of both celiac disease and IBD. Hence the celiac and IBD pathways overlap in the work-up.
What is dermatitis herpetiformis?
One form of the disease shows in the skin. Dermatitis herpetiformis is a separate presentation of the same disease: an intensely itchy, chronic, relapsing rash of small papules and vesicles in clusters. It appears on the extensor surfaces, buttocks, shoulders, trunk, face and scalp.
It is the skin face of the same gluten-triggered autoimmune process. It may occur with no intestinal symptoms at all. When it is present, it confirms the diagnosis of celiac disease. Even so, the diagnosis should be confirmed histologically by skin biopsy rather than assumed, because other itchy vesicular eruptions occur in childhood.
How is it told apart from wheat allergy and non-celiac wheat sensitivity?
Gluten and wheat cause other problems too. Three gluten-related conditions share gluten as a trigger and are frequently confused. They differ in mechanism, and that explains their different tests and treatments.
| Mechanism | How identified | Treatment | |
|---|---|---|---|
| Celiac disease | Autoimmune Th1 enteropathy with villous atrophy | Anti-tTG IgA and EMA (anti-endomysial antibodies), with or without biopsy | Gluten exclusion for life |
| Wheat allergy | IgE-mediated (type I) hypersensitivity | Skin prick test or specific IgE; symptoms on exposure, including after inhalation | Wheat avoidance, with attention to anaphylaxis risk |
| Non-celiac wheat sensitivity | No identified autoimmune or allergic mechanism | Clinical identification; no diagnostic test, no mucosal damage, no autoantibodies | Managed by clinical improvement on a restricted diet |
Celiac disease is identified by the antibodies for the reason given above: they mark the autoimmune process. In wheat allergy, IgE on mast cells reacts to wheat allergens, so symptoms appear on exposure, including after inhalation, and the skin prick test and specific IgE detect that sensitisation. In non-celiac wheat sensitivity no autoimmune or allergic mechanism has been identified. There is no test, no mucosal damage and no autoantibody, and the diagnosis is clinical. One caveat applies: expectation effects make non-celiac wheat sensitivity difficult to assess objectively.
The treatments follow from the mechanisms. Autoimmune damage with a permanent predisposition needs gluten exclusion for life. An IgE-mediated allergy carries a risk of anaphylaxis, so wheat is avoided with that risk in mind. Non-celiac wheat sensitivity is managed by how the symptoms respond to a restricted diet. The evidence for this spectrum of gluten-related disorders is set out in the European Society for the Study of Coeliac Disease guideline.
The diagnosis of celiac disease starts with serology and ends with histology in children who need a biopsy, and two diagnostic pathways exist, with and without duodenal biopsy. Diet and follow-up come after diagnosis, in Treating and Monitoring Celiac Disease. Once celiac disease is suspected, which tests establish it, and when is a biopsy still needed? That is the question of Diagnosing Celiac Disease in Children.