
A child with chronic diarrhea is a sorting problem. Most children have a benign pattern, and a few have organic disease. The work-up has to find those few without investigating every child. So it is a sequence, not a panel, and it works like a funnel with four gates:
- History and growth chart.
- Targeted examination.
- First-line non-invasive tests.
- Endoscopy, only when the earlier gates point somewhere.
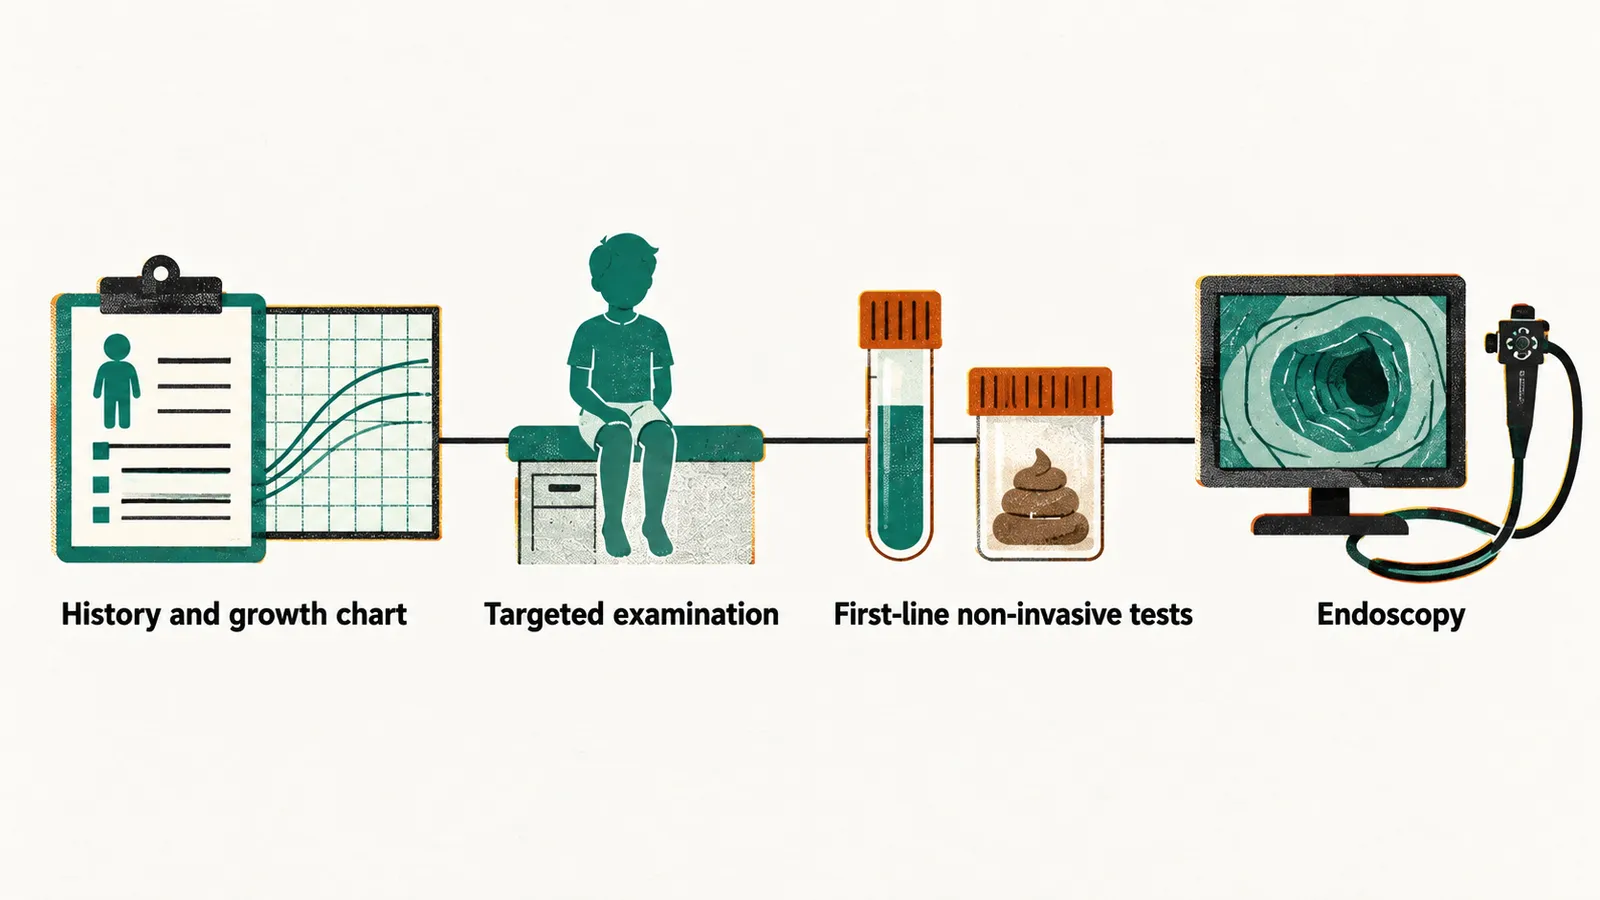
Why gate it this way? A test is worth doing when its result can change what happens next. Endoscopy is invasive, and most children do not need it. The children who do need it should get the right one, because a duodenal biopsy and a colonic biopsy answer different questions. So the cheap steps come first and must earn the scope.
Every gate asks the same thing: which mechanism is producing these stools, osmotic, secretory, fat malabsorption or inflammation? The mechanism decides which part of the work-up to follow. Definitions and Mechanisms of Chronic Diarrhea in Children explains the mechanisms and how the stool tells them apart. Here they become a route.
What does the history add?
The history decides the pre-test probability of almost everything that follows. The same antibody level or marker means different things depending on how likely the disease was before the test. So the history is not a formality. It decides what is worth testing.
It starts with the stools and then widens to diet, exposures and family.
- Onset and pattern. Ask when the loose stools started, and whether they began after an acute gastroenteritis that never fully resolved. Ask whether they are continuous or intermittent. A duration of 14 days or more is what makes the episode chronic.
- Stool characteristics. Ask about consistency, frequency, color, smell, undigested food, blood or mucus, and the relationship to meals. Each reflects a mechanism. Greasy and pale stools suggest fat malabsorption, because fat was not absorbed. Bloody and mucousy stools suggest inflammation, because an inflamed mucosa leaks. Acidic stools after dairy suggest carbohydrate malabsorption, because unabsorbed carbohydrate is fermented.
- Associated symptoms. Ask about abdominal pain, vomiting, fever, rash, joint symptoms, mouth ulcers, perianal problems, weight loss and fatigue. Celiac disease and IBD are immune-mediated, so they can show themselves outside the gut as well as in it.
- Diet. Ask about the age at gluten introduction, the amount of gluten eaten, the type and volume of milk, fruit juice intake, recent formula changes, and any food the family already removed.
- Drugs and exposures. Ask about antibiotics, laxatives, recent travel and day-care attendance.
- Family. First-degree relatives with celiac disease, type 1 diabetes, autoimmune thyroid disease or IBD each raise the probability of the corresponding diagnosis in the child. These diseases cluster in families and with each other.
Why does the diet history matter so much? Celiac antibodies and the biopsy lesion follow the immune response to gluten. If gluten is removed first, that response can fade. A diet restricted before assessment can therefore normalize serology and histology. So it matters what the child was eating when the symptoms started.
What does the growth chart show?
The history says what to suspect. The growth chart shows whether the gut is costing the child nutrition. It records the cumulative effect of what the gut absorbs and what it loses. That makes it the single most informative non-invasive assessment, and it separates a benign functional pattern from organic disease. A child who is absorbing well and is not inflamed keeps growing along the chart.
The thresholds are these:
- Growth below the 2nd centile for age is abnormal.
- A fall across two or more is a red flag even when the absolute centile still looks acceptable. A fall across bands is a loss of trajectory.
- For a child whose birth weight was above the 91st centile, the corresponding threshold is three centile spaces.
Weight deceleration out of proportion to height suggests recent-onset organic disease, because weight falls before length does.
Serial measurements matter more than a single point. One point is a position. A chart with two or three points can show a trajectory; one point cannot.
What does the examination add?
The chart shows the cost, so the examination looks for its signs. Malabsorption, anemia, inflammation and dehydration each leave a physical sign, so the examination runs head to toe.
- General. How unwell the child looks, and pallor from anemia.
- Edema. It comes from hypoalbuminemia, which occurs in protein-losing states including celiac disease. A low albumin can reflect protein that is not absorbed or is leaking through the gut.
- Skin. Dermatitis herpetiformis is the intensely itchy papulovesicular rash of celiac disease on extensor surfaces. and are IBD-associated.
- Eyes and mouth. Uveitis, and recurrent aphthous stomatitis occur in both celiac disease and IBD. Both diseases are immune-mediated, which is why these signs appear in both.
- Abdomen. Look for distension, tenderness, organomegaly and masses. A hard fecal mass is a sign of overflow around constipation.
- Perianal region. Inspect for skin tags, fissures, fistulas and abscesses. These point to Crohn’s disease, which involves the whole thickness of the bowel wall and so can reach the anal region.
Growth and pubertal staging are documented rather than estimated, so that later measurements can be compared with them.
Reassuring pattern, or red flag?
History, growth chart and examination together answer the first question: is the pattern reassuring, or does the child need investigating? This gate is a decision, not a diagnosis. Any one red flag turns a reassuring pattern into an indication to investigate, because each marks possible organic disease.
- Weight loss or growth faltering, the most important single sign.
- Blood or mucus in the stool.
- Nocturnal diarrhea, particularly in a child previously continent. Diarrhea that wakes a child from sleep suggests organic disease rather than a functional pattern.
- Systemic features: fever, rash, arthritis or recurrent vomiting.
- Abnormal laboratory results: raised CRP or ESR, anemia, or signs of chronic inflammation.
- A family history of IBD or celiac disease combined with any of the above.
How are the first-line tests read?
After a red flag, the tests are read as a pattern, not one at a time. A single result rarely settles the question, but the results together show which mechanism is operating. Blood tests look for anemia, protein loss, inflammation and vitamin deficiency. Celiac serology screens for celiac disease. Stool tests look for inflammation, pancreatic insufficiency, carbohydrate malabsorption, protein loss and infection.
Blood
- Complete blood count, ferritin, iron studies, folate and vitamin B12 look for anemia and its pattern. Microcytic iron-deficiency anemia suggests blood loss or malabsorption. Macrocytic anemia suggests B12 or folate malabsorption.
- Albumin and total protein look for protein-losing enteropathy or severe malabsorption. A low albumin with edema is an organic marker.
- CRP and ESR rise with inflammation. A normal CRP with a low albumin and low iron argues for malabsorption rather than active inflammation.
- Vitamin D, and calcium if abnormal, show fat-soluble vitamin status. These vitamins are absorbed with dietary fat, so fat malabsorption lowers them.
- Total IgA and anti-transglutaminase IgA are the first-line celiac screening. Anti-transglutaminase IgA is the celiac antibody. Because it is an IgA-class antibody, selective IgA deficiency produces false-negative IgA results, and measuring total IgA exposes that case.
Stool
- Occult blood looks for mucosal inflammation or bleeding.
- Fecal calprotectin is a neutrophil-derived marker of intestinal inflammation. In an inflamed mucosa, neutrophils move into the lumen and release it, so the stool level tracks neutrophilic inflammation. Interpretation is age-dependent, because levels in healthy children change with age. It also rises in several conditions other than IBD, since any neutrophil-rich inflammation in the gut can raise it. The IBD note gives the cutoffs and the other causes.
- Fecal elastase-1 survives passage through the gut, so the amount in stool reflects pancreatic output. It tests for pancreatic exocrine insufficiency when stools are pale and greasy.
- Stool pH and reducing substances look for carbohydrate malabsorption. Colonic bacteria ferment unabsorbed carbohydrate to acids, so an acidic stool with reducing substances is the pattern of carbohydrate malabsorption.
- Stool alpha-1 antitrypsin is a blood protein that resists digestion, so it appears in stool when protein leaks through the gut wall. It tests for protein-losing enteropathy, when albumin is low and there is no other explanation.
- Parasitology, and stool culture where indicated, look for persistent giardiasis and other infections that mimic malabsorption.
When fat malabsorption is suspected, the first-line panel is completed by a sweat chloride test for cystic fibrosis, the most important cause of pancreatic exocrine insufficiency. A sweat chloride of 60 mmol/L or more confirms cystic fibrosis. A value below 30 mmol/L makes it unlikely.
The pattern of these tests decides the next step, because each mechanism leaves its own trace:
- Typical malabsorptive picture: microcytic anemia with low ferritin, low albumin, low fat-soluble vitamin levels and a normal CRP.
- Typical inflammatory picture: raised CRP or ESR, raised fecal calprotectin and blood in the stool.
Which endoscopy does the pattern choose?
Endoscopy is gated by the non-invasive results, and the mechanism pattern chooses the route. The procedure is the one that can answer the question.
- Malabsorptive pattern (low albumin, iron or vitamin deficiencies, steatorrhea, normal inflammatory markers, no blood in the stool): upper gastrointestinal endoscopy with duodenal biopsies. Celiac disease damages the lining of the small intestine, and a duodenal biopsy is how that lining is examined. This is the route to celiac disease and other mucosal causes.
- Inflammatory pattern (blood or mucus in the stool, raised CRP or fecal calprotectin): ileocolonoscopy with biopsies from the terminal ileum and every colonic segment. IBD can inflame the ileum and colon, and these biopsies show where and how. This is the route to IBD.
- Unclear or mixed pattern: both procedures, because both mechanisms are possible.
Small-bowel imaging is added when small-bowel Crohn’s disease is a possibility. Crohn’s disease can involve any part of the gastrointestinal tract, including segments a colonoscope cannot reach. The options are ultrasound, MR enterography or capsule endoscopy.
Two points about the upper tract follow from the biology.
- A normal-looking duodenum does not exclude celiac disease. The lesion is patchy and the diagnosis is histological. The celiac diagnosis note gives the biopsy protocol.
- Upper endoscopy is part of the pediatric IBD work-up even when symptoms are colon-predominant. Upper gastrointestinal Crohn’s disease is easy to miss, and Crohn’s disease can involve the esophagus, stomach and duodenum.
What happens while the work-up runs?
While tests and endoscopy run, two management questions arise: what the child should eat, and whether a drug should be given to slow the stools.
No specific diet treats chronic diarrhea in children. Restricting the diet before the diagnosis is made can hide the diagnosis, for the reason given above: serology and histology can normalize. So the child stays on an age-appropriate diet. Excessive fruit juice and large volumes of milk can amplify stool output and are worth moderating, because they add unabsorbed carbohydrate and unabsorbed solute holds water in the lumen. A short trial of lactose-free formula is reasonable in selected children with severe symptoms. The evidence for that trial, and its limits, belong to the discussion of acute diarrhea.
Antimotility drugs have no place in the management of chronic diarrhea in children. The European ESPGHAN/ESPID acute gastroenteritis guideline states that loperamide is not recommended in children with gastroenteritis. The concern applies at least as strongly to a chronic picture. There, slowing transit masks inflammation, delays diagnosis and risks ileus. In functional diarrhea in particular there is no toxic hypersecretion to switch off; the transit is simply fast.
All of this assumes organic disease is being sought. When the pattern is reassuring, with a thriving child and normal tests, what is left, and how is it recognized and managed?