Inflammatory bowel disease (IBD) is chronic, relapsing inflammation of the gastrointestinal tract of unknown cause. It has two main forms, Crohn’s disease and ulcerative colitis. As it relapses, treatment has two jobs: bring active inflammation under control, then keep it controlled. A child adds a third demand, because the disease begins while the child is still growing and will last for decades.
How is a child’s IBD treated, and what decides the plan?
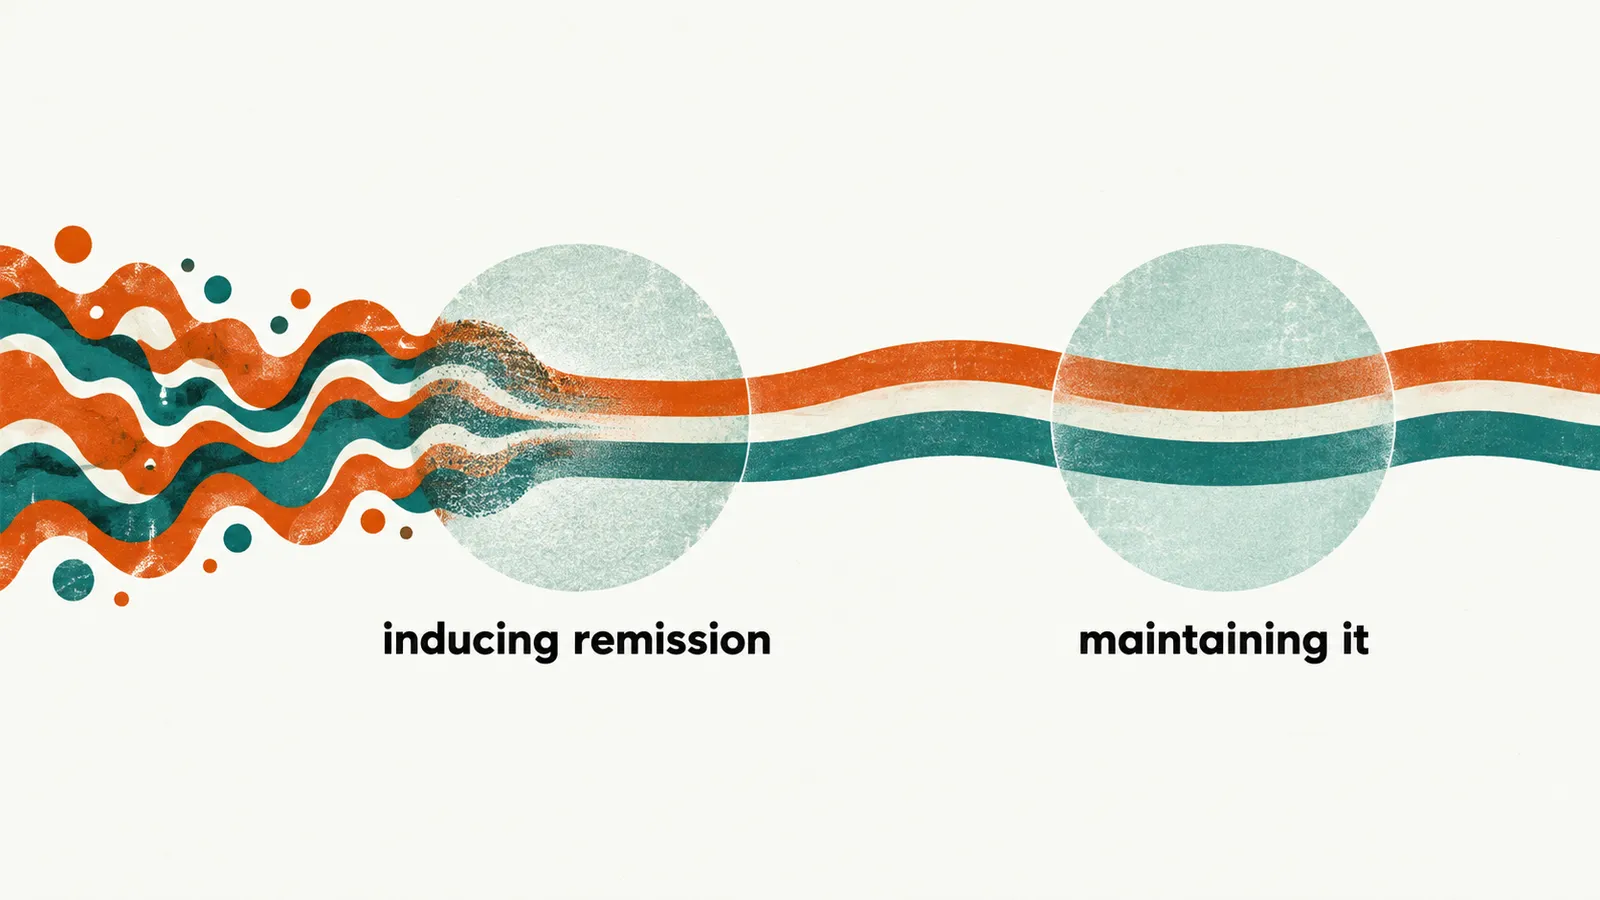
Treatment runs in two phases: inducing remission, then maintaining it. Inducing remission means bringing active inflammation under control. Control without maintenance would be a pause, because the disease relapses.
What decides induction? The disease and its severity at presentation, rather than the child. The reason is where each disease sits. Crohn’s disease is patchy, can involve any part of the gut from mouth to anus, and extends through the full thickness of the bowel wall. Ulcerative colitis inflames the colonic mucosa continuously from the rectum upwards. (These patterns are taught in Pediatric Inflammatory Bowel Disease.) The two diseases sit differently in the gut, so they are induced differently: Crohn’s disease nutritionally, ulcerative colitis by severity-based drug treatment.
After remission is induced, maintenance looks much the same in both diseases. The sections below follow this order: induction in each disease, then maintenance, then what has to be watched in a growing child.
Two features of childhood shape every choice. The disease will last for decades, so the chosen treatment has to be one the child can stay on. And growth and nutrition are treatment targets in childhood IBD, not late-arriving side issues.
How is Crohn’s disease brought into remission?
Exclusive enteral nutrition (EEN) is the first-choice induction therapy for pediatric Crohn’s disease. It is a complete liquid formula as the only source of calories, and it lasts about 6 to 8 weeks. It is as effective as corticosteroids in this setting, without their toxicity. That matters more in a child, because steroids can slow growth, and growth is one of the things treatment is meant to protect.
In Crohn’s disease the inflammation and the nutrition problem go together, and EEN addresses both: weight, linear growth and healing of the bowel lining are reported to improve. How it works is not settled. Proposed explanations include changes in the gut bacteria, restoration of the mucosal barrier and a direct anti-inflammatory effect. How much each contributes is unclear, and part of the evidence comes from laboratory and animal work.
EEN does not depend on a decision to use drugs. Choosing it means choosing nutrition, not a drug, as the treatment.
Because the formula must meet the child’s whole energy need, EEN needs regular monitoring of weight and intake. Its disadvantages are practical rather than medical. It is hard to sustain, and food-based social life disappears during the course.
EEN works in Crohn’s disease, not in ulcerative colitis. A child with colon-only ulcerative colitis does not have EEN as the induction tool. Corticosteroids remain the alternative for children who cannot or will not complete nutritional induction.
Is there a less restrictive nutritional route?
The practical cost of EEN raises the question. The Crohn’s disease exclusion diet (CDED) with partial enteral nutrition was developed as a less restrictive alternative. The formula provides only part of the intake, alongside a restricted set of foods.
A randomized trial compared CDED plus partial enteral nutrition with EEN in children with mild to moderate Crohn’s disease. At 6 weeks the two induced remission in a similar proportion. At 12 weeks the CDED group had significantly better sustained remission, and it also had better tolerance.
How is ulcerative colitis induced?
Ulcerative colitis follows a severity-based step-up rather than a nutritional approach. The disease inflames the colonic mucosa, so the first step is a drug that acts there.
Mild to moderate ulcerative colitis is induced and maintained with 5-aminosalicylates, anti-inflammatory drugs that act on the colonic mucosa. If the response is inadequate, corticosteroids or immunomodulators are added. Immunomodulators are drugs that damp down the immune response, such as thiopurines. The step up from the mucosa to the immune system follows the severity.
At the top of the scale is acute severe colitis, defined by a Pediatric Ulcerative Colitis Activity Index of 65 or more. The index is a clinical score of disease activity. Acute severe colitis is a medical emergency, and it is treated with intravenous methylprednisolone, a corticosteroid. If there is no response, second-line therapy should start by the fifth day of intravenous steroids, so the fifth day is the deadline for starting it.
Infliximab is the preferred medical option for second-line therapy. Calcineurin inhibitors, another class of immunosuppressant, are an alternative in experienced centers.
What keeps the disease quiet afterwards?
Once remission is induced, the problem in both diseases is relapse, so maintenance looks much the same. It rests on two drug groups: thiopurines and biologics. Mild to moderate ulcerative colitis can also be maintained with 5-aminosalicylates.
Thiopurines (azathioprine, 6-mercaptopurine) remain the conventional maintenance immunosuppressant in pediatric IBD. Early introduction is associated with higher steroid-free remission rates than late introduction.
Thiopurines carry a risk that has to be checked before the first dose. Thiopurine methyltransferase is the enzyme that breaks the drugs down. When its activity is low, the drug is cleared poorly, and this can lead to myelosuppression, a fall in blood-cell production by the bone marrow. That is why thiopurine methyltransferase activity or NUDT15 variants are tested before starting, with metabolite monitoring afterwards. The testing is used to reduce the risk of myelosuppression.
What do biologics add?
Biologics are antibody-based drugs that block a specific inflammatory signal. Anti-TNF therapy is directed against tumour necrosis factor, and it is the best-established biologic class in children.
In the European Union the licences are:
- Infliximab: severe active Crohn’s disease, and severely active ulcerative colitis, in children aged 6 to 17 years who have not responded to conventional therapy.
- Adalimumab: moderately to severely active Crohn’s disease, and moderately to severely active ulcerative colitis, from 6 years of age, after inadequate response to conventional therapy.
In ulcerative colitis, infliximab is the first-line biologic in chronically active or corticosteroid-dependent disease, and it is usually combined with an immunomodulator. Adalimumab is used in selected cases or after loss of response to infliximab.
A biologic can stop working, and antibodies against the drug are one reason. Proactive therapeutic drug monitoring measures drug levels and adjusts the dose rather than waiting for symptoms to return. It is recommended for both infliximab and adalimumab, particularly at the end of induction.
Newer agents with different inflammatory targets have been added as options after anti-TNF failure. Vedolizumab is recommended as a second-line biologic in ulcerative colitis. Ustekinumab received a European license in 2025 for moderately to severely active Crohn’s disease in children weighing at least 40 kg. Evidence for newer agents in children is still building, and sequencing advanced therapies is specialist territory.
What must be watched in a growing child?
The drugs are not the whole treatment. Growth and nutrition are treatment targets, not side effects to note later. Inflammation, poor intake and steroids all work against growth. So height velocity, weight and pubertal progress are followed at every visit, and malnutrition is treated alongside the inflammation. Inflammatory signals such as tumour necrosis factor are thought to contribute to poor appetite, so controlling the disease does not by itself correct intake.
Bone health needs the same attention, because peak bone mass is acquired during childhood and adolescence, and active disease and steroids lower bone mass. Bone health and drug safety monitoring follow the chosen therapy.
Adherence, staying on treatment through decades of disease, is a clinical problem in its own right. Reported non-adherence among adolescents with IBD is high. It is linked to anxiety, depression and poor quality of life, so psychosocial support is part of management rather than an adjunct.
Two further safeguards apply to particular situations. Thromboprophylaxis, preventive treatment against blood clots, should be considered in children admitted with acute severe colitis. Their venous thromboembolic risk is increased compared with other hospitalized children, although it is lower than in adults.
Finally, colorectal cancer surveillance is recommended for children with ulcerative colitis from age 12 when disease duration exceeds 8 years. When primary sclerosing cholangitis, a chronic inflammatory disease of the bile ducts associated with IBD, is present, surveillance is recommended from age 12 regardless of duration.
With functional diarrhea, constipation, celiac disease and IBD each now understood, how does one choose a route through them for the child in front of you?