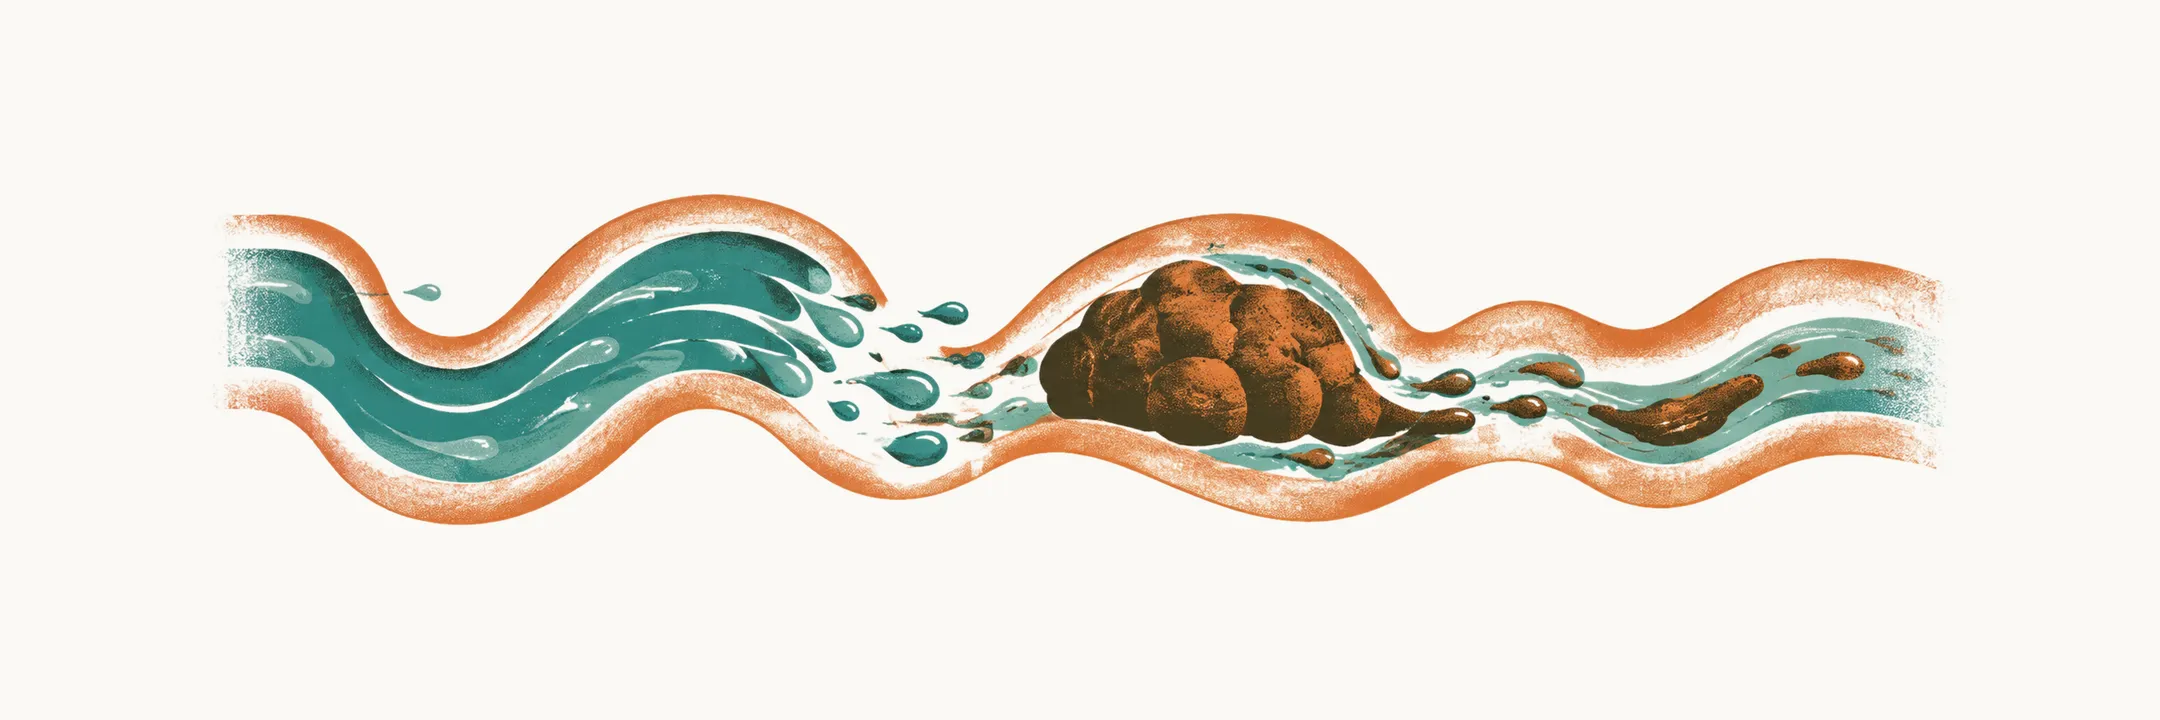
In early childhood the two patterns that dominate the differential of chronic diarrhea are both non-organic. Neither is caused by inflammation, malabsorption or a structural defect of the bowel. They still behave quite differently. In one, the meal is rushed through the bowel. In the other, stool is held back. Both can look like diarrhea to a parent, and both get worse when they are treated as something else.
Why can a thriving toddler have chronic loose stools?
Functional diarrhea is also called chronic nonspecific diarrhea or toddler’s diarrhea. It is the most common cause of chronic diarrhea in early childhood. It is a chronic diarrhea diagnosis in its own right, made from the stool pattern in a child who is thriving. Its diagnosis is a pattern rather than a test.
The mechanism is accelerated transit with incomplete carbohydrate absorption. A meal reaches the colon before all its carbohydrate and water have been absorbed, and unabsorbed carbohydrate holds water in the lumen. The stool is therefore large and loose.
The gastrocolic reflex also operates after eating. It is an increase in colonic activity following eating, and that explains why stools often follow immediately after a meal.
The pattern is amplified by a large intake of fruit juice or fructose, and by low fat intake.
Nothing is inflamed and nothing is malabsorbed. That is why the child looks well, the growth chart is normal and the laboratory tests are normal.
So the stools can be loose and frequent while the child is well. How do we recognise the pattern with confidence?
How is functional diarrhea recognised?
The are international consensus definitions of functional gastrointestinal disorders. For functional diarrhea they ask for:
- daily, painless, recurrent passage of four or more large unformed stools;
- symptoms lasting more than four weeks;
- onset between 6 and 60 months of age;
- no failure to thrive (faltering weight gain) when caloric intake is adequate.
The last criterion sets this condition apart from malabsorption. The normal laboratory tests are the blood count, the inflammatory markers and celiac serology. The diagnosis rests on normal growth and these normal tests.
Functional diarrhea is reached only after red flags and the malabsorptive and inflammatory causes have been excluded. A child with the same stool pattern does not have functional diarrhea if any of these is present:
- growth that is flattening;
- stools at night;
- blood in the stool;
- abnormal inflammatory markers.
These children belong to the organic work-up described in Clinical Approach and Work-up of Chronic Diarrhea in Children. Both patterns are reached through the growth chart and a small set of tests rather than through the stool alone.
When the pattern holds, what does the child need?
What does the child need?
Once the pattern is confirmed, management is reassurance and dietary advice. No drug treatment is needed. The condition is harmless and resolves spontaneously by school age.
Cutting back fruit juice and sweet drinks is the first change, because juice is the usual trigger. A general recommendation is juice of no more than about 120 mL (4 oz) a day in a child aged 1 to 3 years, which is a reasonable target. Milk and water stay the main drinks.
The rest of the diet is balanced rather than restricted. A low-fat, juice-heavy diet is the pattern that produces these stools.
When the pattern does not settle, a food-and-stool diary identifies reproducible triggers better than further broad elimination.
But not every loose stool in a toddler comes from rushed transit. Some come from the opposite problem.
How can constipation look like diarrhea?
A constipated child can present with liquid stools, and parents reasonably describe this as diarrhea. The loose stool of overflow around constipation is not diarrhea at all. It is stool leaking past a retained fecal mass.
The mechanism is obstructive rather than secretory. Soft stool passes around a retained hard fecal mass and leaks out. This is often seen as soiling of the underwear, and the child may pass several small loose stools a day.
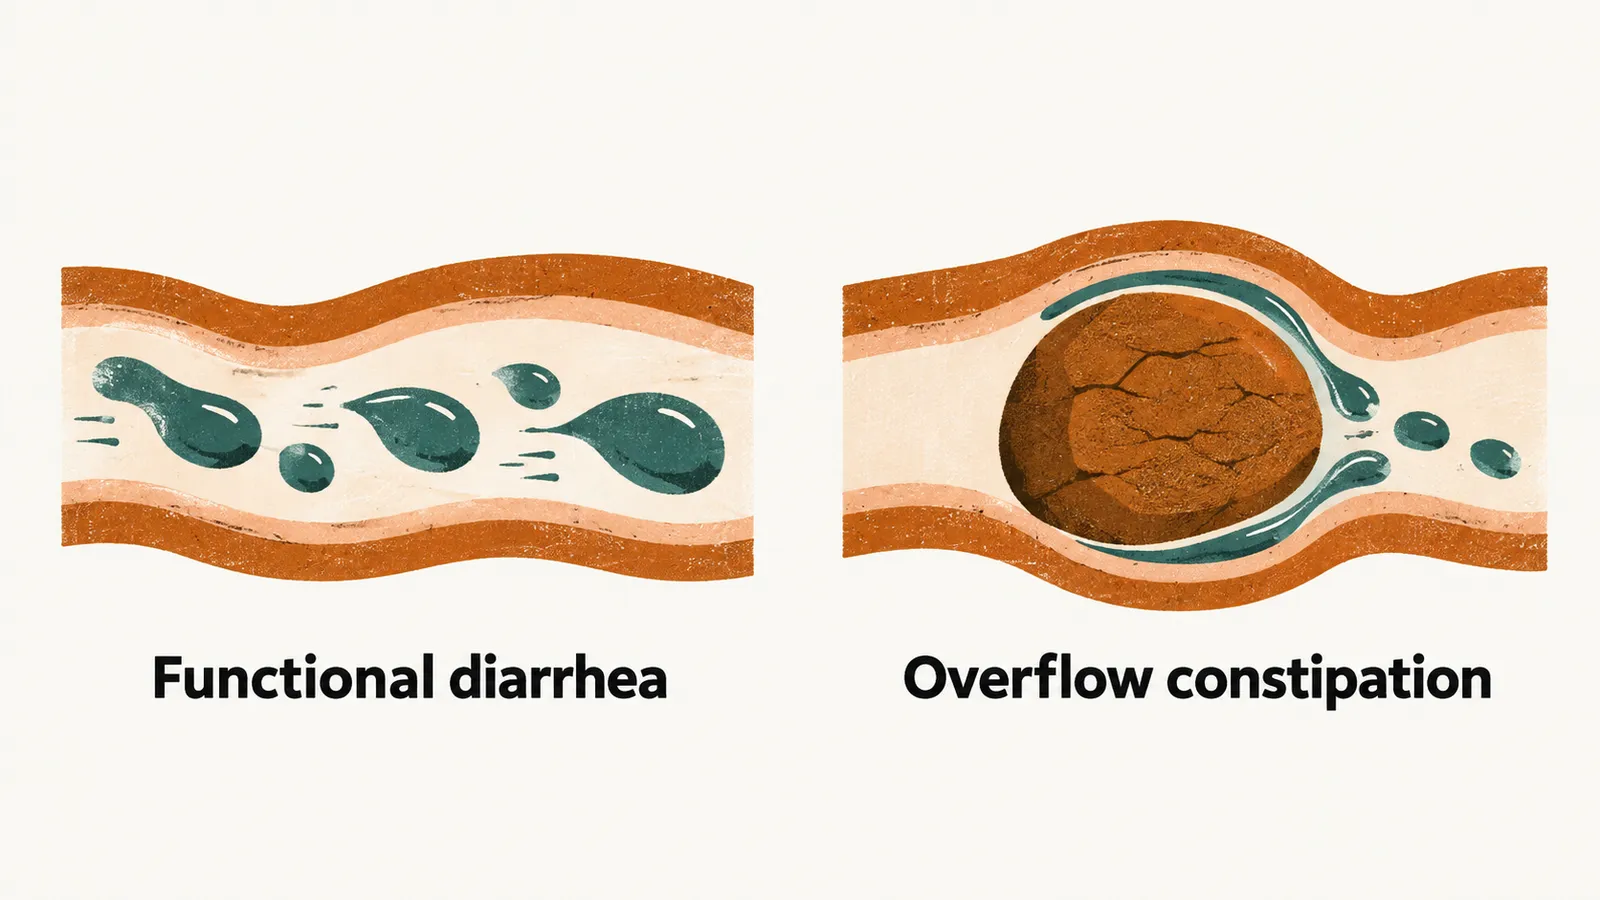
On examination the clue is a palpable mass in the lower abdomen, or hard stool in the rectum. The history often contains a counter-intuitive detail: the child passes stool frequently rather than infrequently.
What happens if this leakage is treated as diarrhea?
How is overflow treated?
Treating overflow as diarrhea makes it worse. Antidiarrheal drugs increase the retention that produced the problem. A child labelled as chronic diarrhea may be treated for the wrong condition for a long time before the abdomen is examined.
The retained stool has to be cleared, and then the constipation is treated. A disimpaction regimen clears the retained mass, and it comes first when fecal impaction is present. It is followed by maintenance laxative treatment. Oral macrogol (polyethylene glycol, an osmotic laxative) is the usual first choice.
Maintenance is continued for months rather than days while a regular toilet routine is re-established.
So what if neither pattern fits?
What if neither pattern fits?
When there is no retained fecal mass, and growth is faltering or the stools contain blood, the child belongs to the organic work-up. Organic causes in the toddler years include:
- cow’s milk protein allergy;
- cystic fibrosis–related pancreatic insufficiency;
- celiac disease, which appears once gluten has been introduced into the diet.
If the child has an organic cause, which one is it, and how does a disease such as celiac disease injure the gut?