
Antibiotic choice in a child’s urinary tract infection becomes easier once the infection is assigned to a compartment. So the question that comes before any drug is where the infection sits.
Where does the infection sit?
The bacteria can be in the urine in the bladder, in the tissue of the kidney, or in the blood.
Cystitis is infection limited to the bladder, so it is a problem of the urine alone. The bacteria are in the bladder, and a drug that concentrates in the urine can reach them. A drug that the kidneys excrete unchanged into the urine collects there, which is why the bacteria in the bladder meet it.
Pyelonephritis and urosepsis are problems of the urine and the blood. In pyelonephritis the bacteria have reached the renal parenchyma, and they may be in the bloodstream. As the foundations note set out, bacteria climb from the bladder into the kidney, so the kidney is the second place to treat. As the clinical presentation note set out, localised flank pain points to the kidney and lower-tract symptoms point to the bladder.
So cystitis is a urine problem, and pyelonephritis is a urine and blood problem.
Why must the drug reach that place too?
Naming the place is not enough, because the drug has to get there. Kidney tissue receives its drug from the blood, not from the urine. In pyelonephritis or urosepsis the drug must therefore reach adequate concentrations in tissue and blood, not only in urine. A drug with poor serum and tissue levels fails there even when the urine is treated.
This explains why most avoidable treatment errors come from choosing a drug that satisfies only the first compartment.
Which drugs stay in the urine?
Some drugs are excreted into the urine and stop there. Fosfomycin is the clearest example of a drug that stays in the urine. Nitrofurantoin is another: it concentrates in the urine and gives no useful serum or tissue levels.
Fosfomycin
Fosfomycin is excreted unchanged in the urine, and only part of a swallowed dose is absorbed. Its oral bioavailability is around 40%. So the serum concentrations stay low relative to the MICs of the organisms being treated, while the urinary concentrations are high.
That is why fosfomycin is licensed for uncomplicated lower UTI. Because most of the drug leaves in the urine, too little reaches the blood to reach kidney tissue, and it is explicitly not indicated for pyelonephritis or perinephric abscess. It is an excellent urinary tract drug and an inadequate renal parenchymal drug. In practice it is for uncomplicated cystitis only.
Licensing also varies by age. In many countries oral fosfomycin is licensed for adults and older adolescents rather than young children, so the local licensing age should be checked before prescribing it.
Nitrofurantoin
Nitrofurantoin follows the same logic with a different drug. Its serum and tissue levels are not useful, so it treats cystitis, not pyelonephritis. It is used for lower UTI when renal function is adequate.
What goes wrong in the wrong compartment?
A urine-only drug is the wrong tool for kidney tissue. Fosfomycin and nitrofurantoin are useful in the right compartment and dangerous in the wrong one. A child whose bladder-limited infection is actually early pyelonephritis will be undertreated, because the drug never reaches enough kidney tissue and the bacteria there go untreated. Fosfomycin and nitrofurantoin concentrate in urine and should not be used for pyelonephritis.
Is the route a separate question?
Where the drug must work is settled, and how it gets in is another question. The route is separate from the compartment. A drug that reaches tissue and blood can be given by mouth, and the amount reaching the blood depends on how well it is absorbed, as the partial absorption of oral fosfomycin shows. Pyelonephritis does not by itself demand intravenous treatment. The route decision concerns absorption and severity rather than the diagnosis itself.
Oral or intravenous?
Most children with UTI who are drinking and are not septic can be treated with oral antibiotics. Oral is the preferred route in current guidance for children over 3 months who are not vomiting or severely ill.
Intravenous treatment with fluids is reserved for children who cannot tolerate oral medication: those who are dehydrated or vomiting, look septic, or are under 3 months.
Which organism must the drug cover?
After compartment and route are settled, the next question is which organism the drug must cover and how likely it is to resist the drug. Treatment usually starts empirically. As the urine sampling note set out, treatment starts before the culture result is back.
The choice follows the local antibiogram, the laboratory summary of how often the common urinary organisms in the area are susceptible to each antibiotic. Antibiotic misuse and overuse is a leading cause of the spread of resistance in community-acquired pediatric UTIs, so the local pattern is the guide. Local resistance differs from place to place, so the local antibiogram decides.
Amoxicillin on its own
Plain amoxicillin is the first drug that fails. Bacteria that produce beta-lactamase destroy it, so it is unreliable without a susceptible isolate. Urinary E. coli resistance to ampicillin and amoxicillin is common enough that amoxicillin alone is not recommended empirically.
Amoxicillin with clavulanate
Clavulanate is the answer to that failure. It inhibits the beta-lactamase enzyme, so the amoxicillin is protected from breakdown. Amoxicillin–clavulanate is the first-line oral drug for febrile UTI in Italian and some European guidance.
UK guidance prefers cefalexin and uses amoxicillin–clavulanate only when the isolate is confirmed susceptible. A confirmed susceptible isolate removes the guess, so the drug is used only when susceptibility is shown.
Resistance to amoxicillin–clavulanate varies by region: roughly 10–30% of urinary E. coli in European pediatric series. It is about 40% in children with congenital anomalies of the kidney and urinary tract (CAKUT) or a neurogenic bladder. That is why local antibiograms matter for this choice.
Cephalosporins
A broader drug is a common next choice. Cephalosporins are effective and widely used for pyelonephritis: oral cefixime or ceftibuten, and intravenous ceftriaxone or cefotaxime. UK guidance uses cefalexin as the first-line oral drug.
They are very effective, but they are a strong driver of resistance, so they are often described as second-line. A broad drug kills susceptible bacteria and leaves resistant ones to grow. Resistance to third-generation cephalosporins is rising by roughly 1–2% per year in some series.
Aminoglycosides
An intravenous drug has its own toxic profile. Aminoglycosides (gentamicin, amikacin) are given intravenously, particularly in infants with pyelonephritis. They are nephrotoxic and ototoxic. The dose is set by weight, and serum levels are monitored, especially with any fall in kidney function.
Trimethoprim–sulfamethoxazole
This drug also has limits by compartment. It suits lower UTI where the risk of resistance is low. In most guidance it is not a first choice for renal parenchymal infection.
Ciprofloxacin
Ciprofloxacin is the last reserve agent, kept for resistant organisms when the alternatives are exhausted. It was historically avoided in children because of joint and cartilage effects seen in juvenile animals. Modern pediatric use is more accepted for specific indications, but it is not a drug of first choice, and it remains a reserve agent.
Why is the first choice sometimes wrong?
Even a good guess misses often enough to matter. Inadequacy of initial therapy is not rare, even with the antibiogram as a guide. In one hospital series a quarter of children needed their antibiotic changed once the susceptibilities were available.
How long does treatment last?
Duration follows the compartment, as the drug does.
- Cystitis is short. UK guidance for children uses about 3 days of an oral agent such as trimethoprim or nitrofurantoin.
- Febrile UTI or pyelonephritis is longer: 7–10 days of oral treatment. The alternative is 2–4 days of intravenous treatment followed by oral therapy, to a total of about 10 days.
- The AAP guideline for febrile infants aged 2–24 months allows 7–14 days of antimicrobial therapy.
Local protocols vary, and where a child sits within these ranges depends on the clinical response and the organism.
What is the fixed sequence?
Drug, route and duration sit inside a fixed sequence that starts before the first dose.
First, the urine specimen is collected before the first dose. As the urine sampling note set out, an antibiotic given first suppresses the culture.
Second, empiric treatment starts immediately afterwards, based on the local resistance pattern and the child’s clinical state.
Third, the child is reviewed at 48 hours. If the child is not improving, the diagnosis, the compartment, and whether the organism is resistant or unusual are all reconsidered.
Fourth, treatment is adjusted to the isolate’s susceptibility results when they return, narrowing where possible.
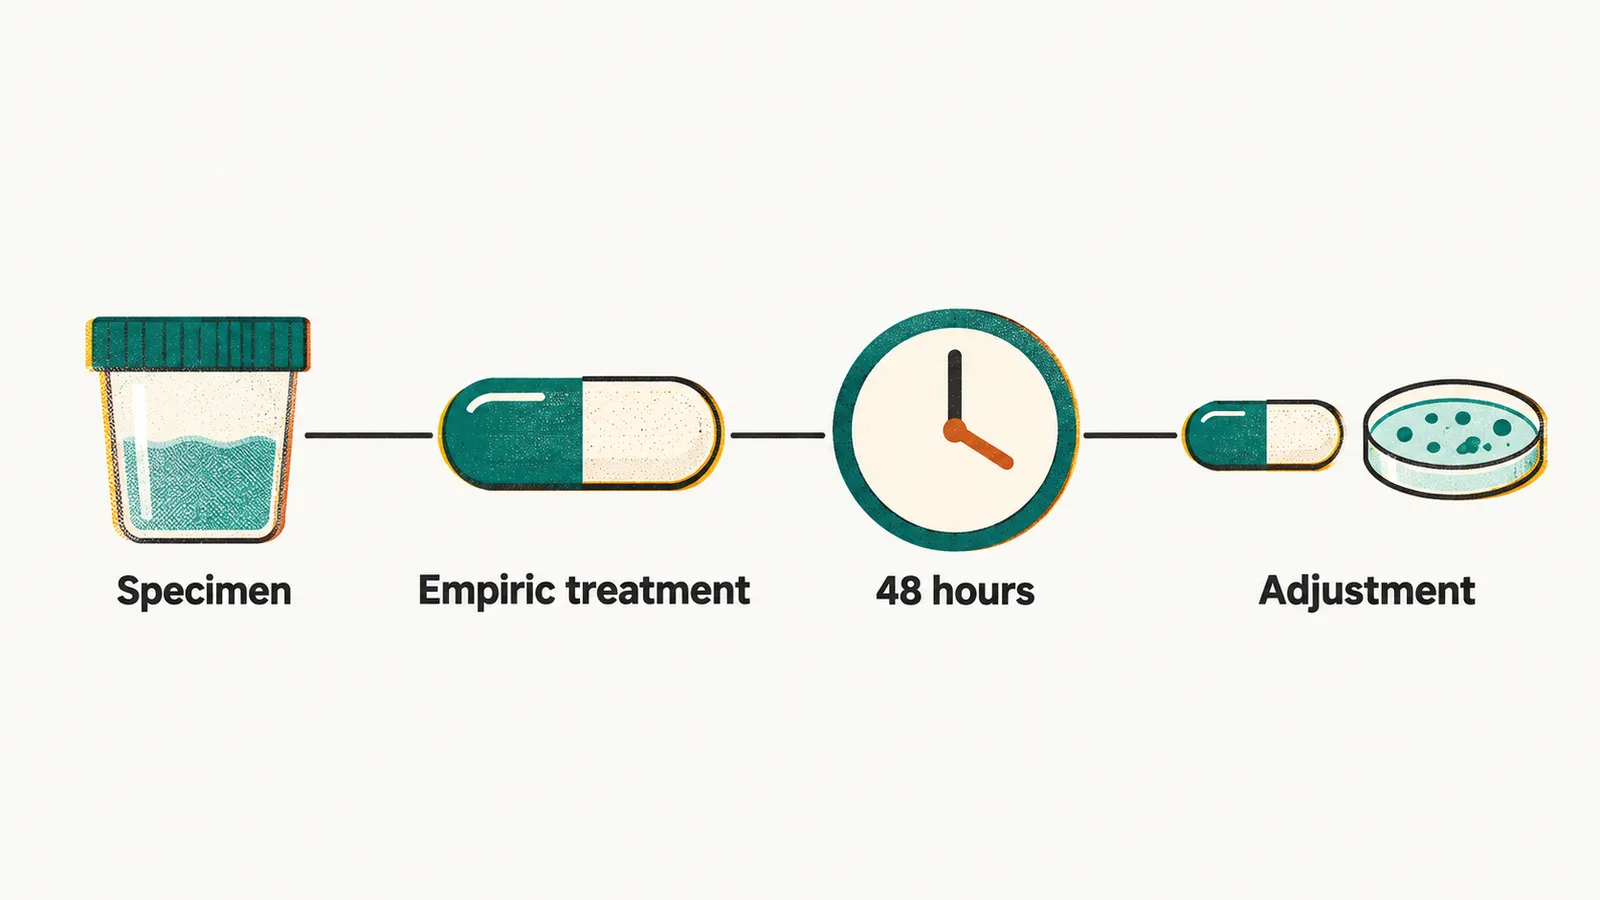
So it is specimen first, antibiotic second, adjustment third.
What does a non-E. coli organism change?
If the child is not improving, the organism is a reason to reconsider. A non-E. coli organism predicts a higher chance of resistance. As the foundations note set out, a non-E. coli infection in a young child suggests an upward route that a structural abnormality would provide. So it also raises the probability of an underlying structural abnormality, and it is a reason to complete imaging even if the infection settles quickly.
A clear response to treatment does not show whether the kidney was damaged or has a structural problem, so what do the kidneys look like on imaging, and which scan should show it?