
Urine is made without a pause, so it has to leave the tract through the outlet at its bottom. Obstruction anywhere along the urinary tract raises the pressure behind it, because urine is still being made while the way out is closed. Obstructive uropathy is the pattern of dilatation and parenchymal damage that results.
CAKUT is the group of congenital anomalies of the kidney and urinary tract. The most damaging example is a pair of mucosal folds in the posterior urethra of boys.
How does a blockage damage the kidney?
The pressure does not stay where the block is. It is passed back up the tract, so the tract behind the blockage dilates: the renal pelvis first, then the ureters, then the bladder. The kidney sits at the top of that column.
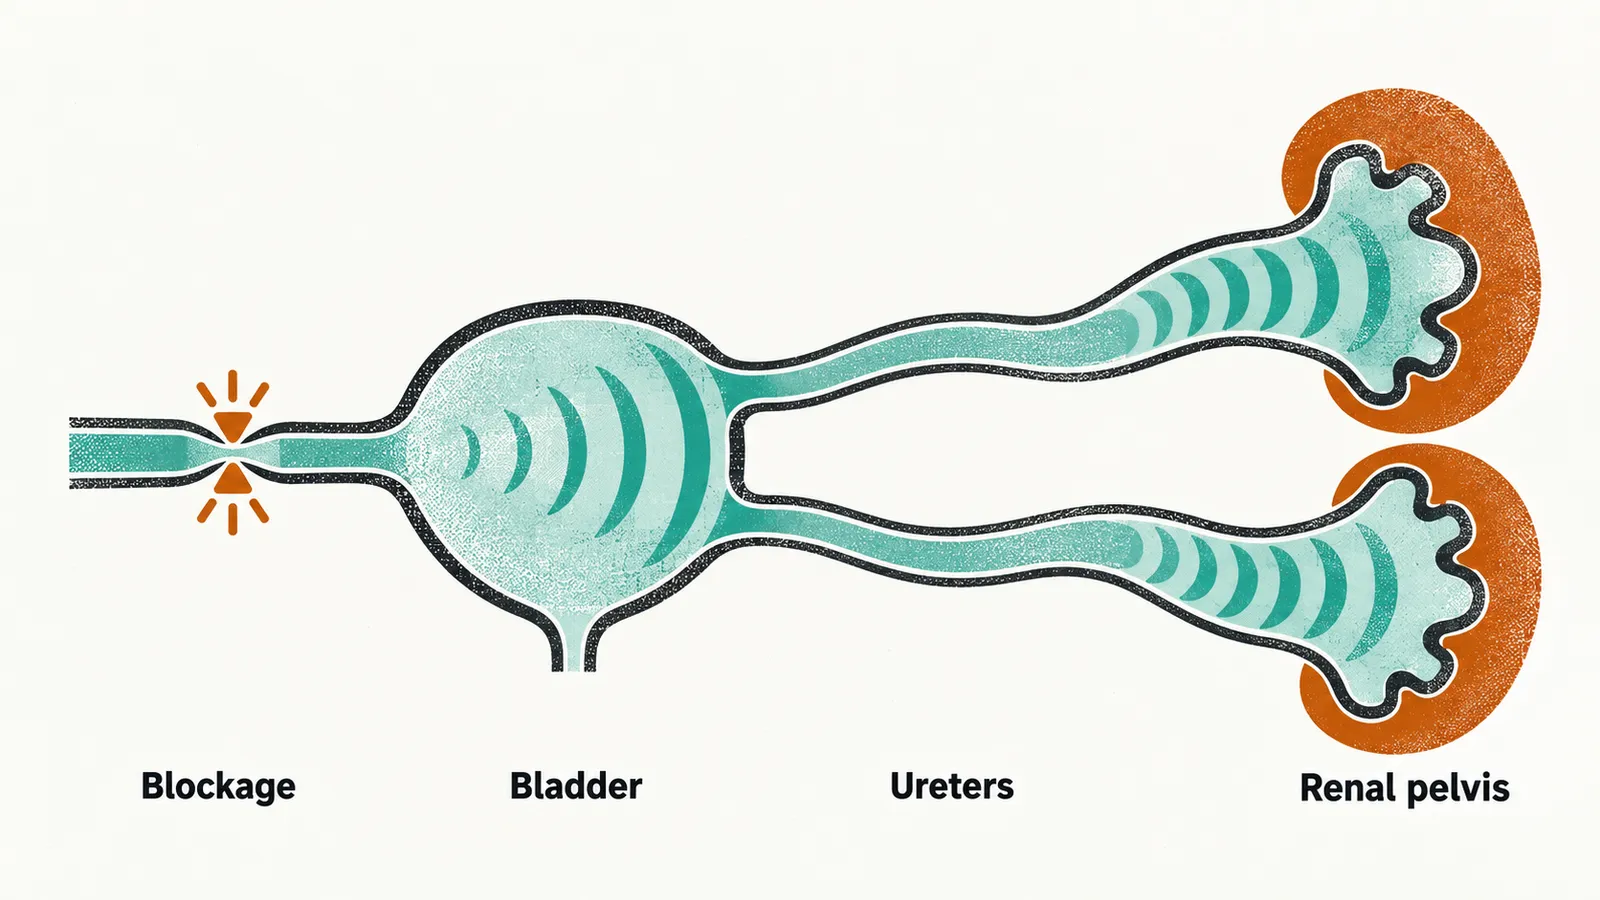
In a fetus or infant, that pressure falls on a kidney still being built. Nephron formation is finished by late pregnancy, so damage done before then falls on tissue that is not rebuilt. That is why the consequences of posterior urethral folds extend from before birth into adult life.
Sustained high pressure damages the developing parenchyma.
Two mechanisms therefore run in parallel, pressure and infection. Both are reasons to relieve an obstruction rather than observe it.
Can sterile urine do harm?
Yes. The injury is driven by the pressure itself, so it needs no bacteria: sterile urine alone can cause this pressure damage.
Dysplasia is sometimes found in kidneys draining a high-pressure system before any infection. Sterile high pressure alone can leave dysplasia.
Where does infection come in?
Pressure is one route; infection is the other. Stasis leaves urine in place to be colonised, so an obstructed tract infects more easily. As the foundations note set out, urine flow and an intact lining carry most of the defence.
A febrile UTI in a child with obstruction signals that the obstruction needs attention, not only an antibiotic. As the foundations note set out, febrile UTI is infection that has reached the kidney, and cystitis is infection confined to the bladder. In short, obstruction damages the kidney by pressure and by infection.
Where in the tract does the block sit?
Pressure needs a block, and in children obstruction occurs at a few characteristic levels.
One is the ureteropelvic junction, where the renal pelvis meets the ureter. Another is the ureterovesical junction, the site of the valve mechanism that fails in vesicoureteral reflux. As the reflux note set out, reflux is urine going back from the bladder toward the kidney, through the valve mechanism at the ureterovesical junction.
The third level is the posterior urethra, where valves in boys produce the most severe form of obstruction.
What are posterior urethral valves?
The block that matters most sits in the posterior urethra of boys. As the imaging note set out, posterior urethral valves are congenital folds in the posterior urethra of boys that obstruct outflow of urine. They are abbreviated PUV.
The valves lie in the urethra below the bladder, so the bladder and the tracts above lie behind the block. PUV are one of the few life-threatening congenital urinary tract anomalies found in the neonatal period.
PUV account for roughly 60% of congenital lower urinary tract obstruction. The incidence is estimated at 1 in 7,000–8,000 live births. Up to 17% of paediatric end-stage renal disease is attributed to PUV.
Which type is most common?
The valves come in types, and one is far more common. Young type I is the commonest form: a ridge continuous with the verumontanum that divides into two fork-like processes. It accounts for 90–95% of cases.
What happens above the valves?
The valves are below the bladder, so the damage moves up the tract. As the imaging note set out, the valves change the bladder and the upper tracts they drain. Bladder wall and bladder neck hypertrophy occur, and nearly all boys with PUV have dilated upper tracts. Dilatation on both sides follows from the same pressure acting on both tracts.
Secondary vesicoureteral reflux is present in at least 50% of boys with PUV. As the reflux note set out, reflux driven by a pressure source outside the junction is a different problem from reflux through a short tunnel at the junction.
Pressure reaches the kidney that drains the tract. A kidney draining a high-grade refluxing system in this setting is under that pressure and often functions poorly.
How is it suspected before birth?
The same pressure is visible on the fetal scan, and antenatal ultrasound raises suspicion in most cases. The findings are a distended, thick-walled bladder with bilateral hydroureteronephrosis, and sometimes the “keyhole” appearance of the dilated posterior urethra. Severe obstruction also produces oligohydramnios. Antenatal suspicion thus comes from a thick-walled bladder with bilateral hydroureteronephrosis and oligohydramnios.
None of these signs is decisive on its own. A thick-walled bladder predicts PUV better than the keyhole sign does. Imaging is not specific, because obstructive and non-obstructive dilatation can look alike. Suspected lower urinary tract obstruction is normally referred to a centre with both prenatal and postnatal expertise.
Why does the fetus lose fluid?
The scan shows low fluid, so the next question is why. Severe obstruction reduces fetal urine output. Amniotic fluid is needed for lung development.
Can the blockage be drained before birth?
If pressure is the problem, relief is the question. A prenatal shunt restores amniotic fluid and may improve early survival. In animal models, draining the fetal bladder early can prevent some of the dysplasia that obstruction causes. The randomised PLUTO trial, however, found no long-term benefit of the prenatal shunt for renal function.
What does the baby look like after birth?
Pressure has reached the kidney, so what does that look like? After birth, the picture depends on how severe the obstruction is. A boy may have a poor urinary stream, a palpable bladder, failure to thrive, or a UTI that behaves like sepsis. Undescended testis and inguinal hernia are more common in these boys than in others. Initial management involves a paediatric nephrologist as well as a urologist.
What do the blood tests show?
Impaired filtration shows up in blood. Raised pressure lowers glomerular filtration, so the kidney clears less. Blood tests may therefore show impaired kidney function with electrolyte disturbance.
Creatinine is cleared by glomerular filtration, and its blood level rises when filtration falls or urine elimination is obstructed. That is why creatinine, urea and electrolytes are followed closely through the first days.
How is the diagnosis confirmed?
The chemistry says the kidney is affected, so the anatomy has to be shown. As the foundations note set out, cystography is an X-ray that follows contrast as the child voids. As the imaging note set out, cystography is how posterior urethral valves are diagnosed.
Voiding cystourethrography (VCUG), with lateral views of the urethra during voiding and no catheter in place, defines the anatomy. It shows a dilated posterior urethra, a thick-walled bladder and dilated upper tracts. The anatomy is confirmed on VCUG during the voiding phase, with the bladder already drained. The diagnosis is confirmed after birth on voiding cystourethrography.
As the imaging note set out, DMSA reads kidney tissue, and MAG-3 reads drainage and split function. Nuclear renography with either one assesses how much function each kidney contributes and whether either kidney has already scarred.
What is done first?
Once the anatomy is known, the first step is to drain. Drainage comes first and definitive treatment second. The order matters because the infant’s chemistry and kidneys must be stabilised before instrumentation.
The bladder is drained with a transurethral or suprapubic catheter, and antibiotic prophylaxis is started. Treatment is thus bladder drainage and antibiotic prophylaxis first, then endoscopic valve ablation.
How are the valves treated?
After drainage, the valves are removed. They are ablated endoscopically once the infant is stable, provided the urethra admits the instruments.
Extensive electrocoagulation is avoided because urethral stricture is the commonest complication of the procedure. Thermal injury and instrumentation damage the urethral wall, and the healing that follows narrows it. Extensive coagulation therefore risks a urethral stricture.
When does drainage have to continue?
Sometimes the valves cannot be removed or do not relieve the tracts. Drainage is maintained when the child is too small for endoscopy, and when ablation fails to decompress the upper tracts or improve renal function.
Vesicostomy is one option for maintaining drainage. It stabilises or improves the upper tracts in up to 90% of cases. Draining the bladder removes the pressure that would otherwise pass back up the tract, which is why the upper tracts can settle.
When is urine diverted above the bladder?
Drainage has its own limits, so the next question is diversion. High urinary diversion drains urine from above the bladder. It is reserved for children whose upper tracts do not decompress with bladder drainage alone.
Diversion is not a more renoprotective treatment than ablation. A systematic review of comparative studies found that worse kidney outcomes after diversion were largely explained by worse kidney function at presentation. The choice between diversion and ablation is therefore usually anatomical and practical rather than a matter of protecting the kidneys.
Why does the bladder keep misbehaving after the valves are gone?
Relieving the obstruction does not end the problem, because a bladder that developed under high pressure continues to misbehave. A proposed explanation is that the bladder is remodelled under the pressure of the valves, and that this dysfunction persists after the valves are removed; bladder dysfunction is one of the factors named in progression to kidney disease.
Valve bladder describes this dysfunction. It includes poor compliance, small capacity and detrusor overactivity. Later there is myogenic failure.
Valve bladder dysfunction can progress long after anatomically successful ablation. Bladder function can deteriorate years after ablation.
How is valve bladder managed?
When the bladder misbehaves, treatment follows its behaviour. Daytime and night-time continence are often delayed. Management is guided by urodynamic assessment where indicated. It may include anticholinergic therapy for overactivity, and alpha-blockers or clean intermittent catheterisation when emptying is poor. It may also include nocturnal drainage when a high overnight urine output distends the bladder.
How much kidney is left?
The bladder and the kidney are both damaged, so the kidney outcome is the question. Nephron formation is complete around term, so much of the kidney’s reserve is set before birth. Renal prognosis is therefore set largely by the damage present at diagnosis.
Estimates of eventual kidney failure vary with the cohort studied. A systematic review reported chronic kidney disease in about 32% and end-stage renal disease in about 20%, so about one boy in five reached end-stage renal disease. The European guideline notes chronic kidney disease in up to 65% of patients in some series.
What does the creatinine show?
The most useful single marker is the nadir creatinine: the lowest serum creatinine during the first year after decompression.
Creatinine leaves the blood by glomerular filtration, so a higher serum level means filtration is lower. A creatinine that stays high after relief means filtration stays low. A nadir creatinine above 0.85 mg/dL (75 µmol/L) is correlated with a poor renal prognosis. Published nadir creatinine cut-offs range from 0.85 to 1.2 mg/dL.
Why does follow-up last a lifetime?
The kidney outcome is set early and carried forward, while the bladder can change years after ablation. Bladder and kidney function are therefore monitored lifelong, and followed for life.