Why does a toilet-trained child with repeated urinary infections so often need the bladder and bowel looked at first? As the imaging note set out, in a toilet-trained child the explanation for repeated infection often lies less in the anatomy than in how the bladder and bowel behave between infections.
Bladder and bowel dysfunction (BBD) is the combination of lower urinary tract symptoms with a bowel disturbance, usually constipation. It is one of the most common reasons for recurrence after a first urinary tract infection. It is also one of the few contributors to recurrence that can be changed at home.
How does the bladder hold and empty urine?
To see how the bladder fails, we first need the normal job. The bladder has two jobs. It stores urine while it fills, and it empties when the child chooses to void.
Emptying depends on the detrusor contracting while the sphincter at the bladder outlet relaxes. Storage is the opposite state: the detrusor stays relaxed while the outlet is held shut. Dysfunction can arise in either phase. Because the two phases use opposite muscle behaviour, the two failures look like opposites.
What changes as a child learns bladder control?
Once the bladder’s two jobs are clear, the question is when a child is expected to do them on purpose. A newborn bladder empties reflexly as it fills, frequently and involuntarily. Voluntary control arrives gradually. Daytime continence comes around age 3, and night-time continence around age 5.
So bed-wetting before about age 5 is developmental rather than pathological. As the presentation note set out, enuresis is not diagnosed before five, and from five the split between never-dry and previously-dry bed-wetting becomes useful. Secondary enuresis points towards an acquired problem such as inflammation, constipation or a dysfunctional voiding pattern.
What goes wrong when the bladder fills?
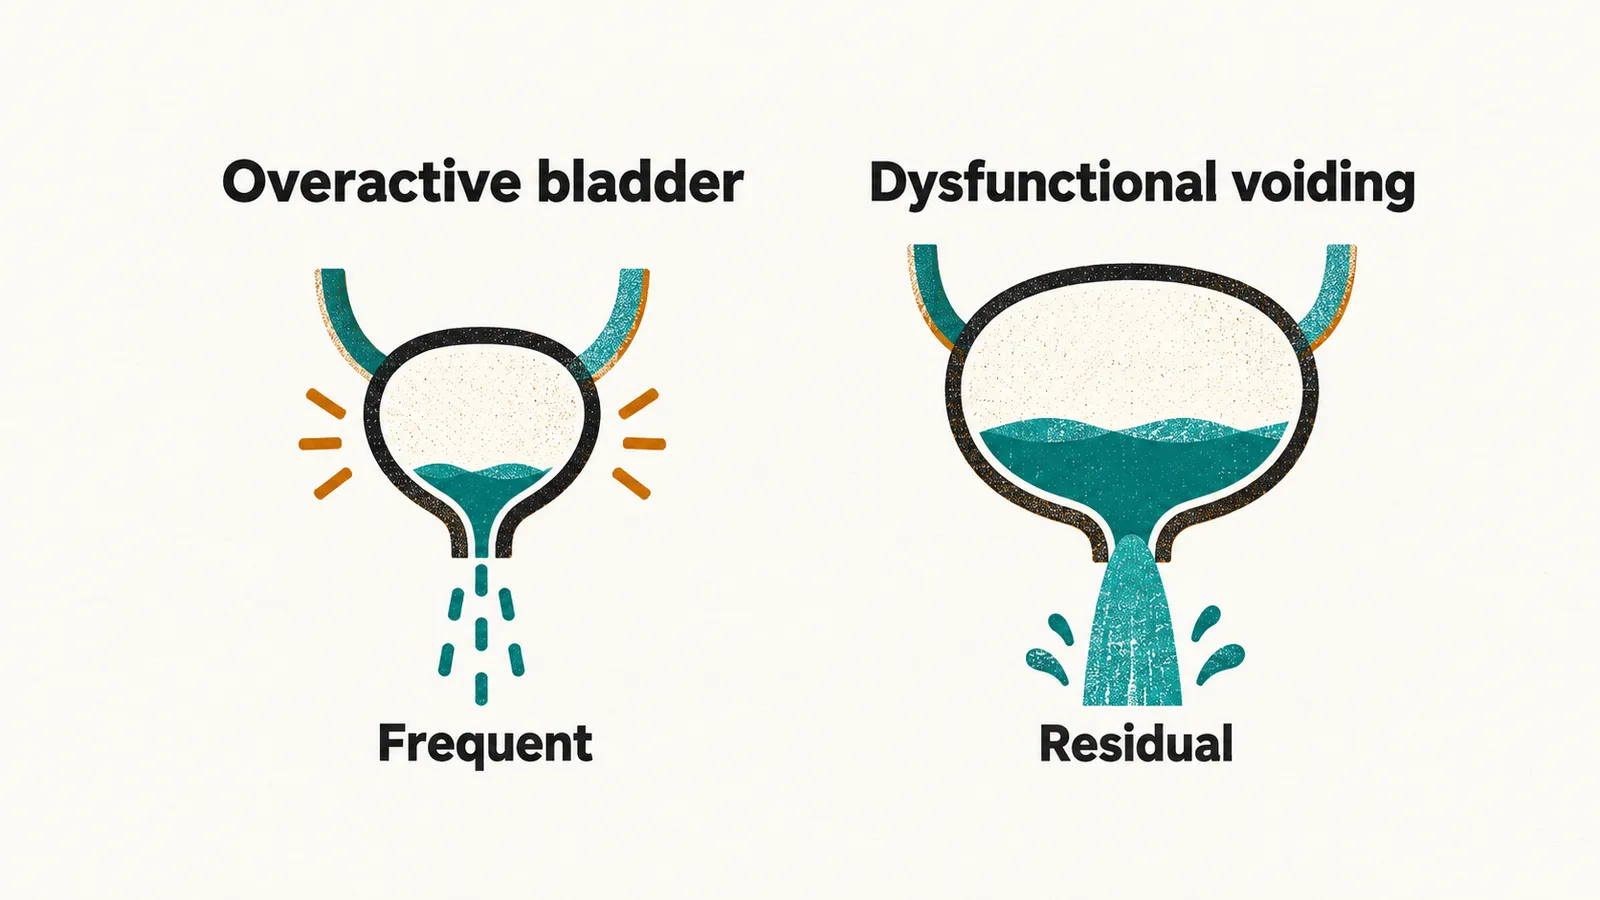
If the bladder contracts during filling, the child feels a sudden urge that is hard to defer. This is overactive bladder, a filling-phase problem: the detrusor contracts before the bladder is full. During storage the detrusor is meant to stay relaxed, so a contraction during filling is the abnormal event.
The child voids often and urgently, in small volumes. If the contraction overcomes the hold of the outlet sphincter, the child may leak before reaching a toilet. Overactive bladder also raises the risk of ascending infection, because each contraction can push urine and bacteria towards the ureters.
What goes wrong when the bladder empties?
The opposite failure leaves urine behind, and that residual urine is where bacteria settle. Dysfunctional voiding and underactive bladder are emptying-phase problems: the detrusor contracts weakly, or the sphincter fails to relax. Emptying needs both a contracting detrusor and an outlet that opens, so if either fails, urine stays behind.
The child voids infrequently and in large volumes, and a residual volume remains after each void. As the foundations note set out, bacteria can settle in urine that is not cleared. Residual warm urine is a favourable environment for bacterial growth, so this pattern produces cystitis and recurrent infection. It is easily missed, because neither the family nor the child recognises infrequent voiding as a symptom.
Why must the history ask about both phases?
The two failures look like opposites, so one question about either phase misses the other. The history must ask about both filling and emptying. In a toilet-trained child with recurrent infection, the voiding history is the most productive step.
Both extremes of frequency matter because they are opposite failure modes. Overactive bladder voiding is frequent, urgent and small-volume. Dysfunctional voiding is infrequent, large-volume and leaves a residual.
What does the history ask about?
The history turns those two failures into questions the family can answer.
- Incontinence: is there involuntary daytime urine loss?
- Hesitation: is it hard to start the stream? Starting needs the outlet to relax, so difficulty starting points to an outlet that is not opening.
- Straining or effort: is abdominal pressure needed to start or maintain voiding?
- Weak or intermittent stream: is flow reduced, stop-start, or sometimes spraying?
- Holding manoeuvres: does the child postpone micturition by crossing the legs, squatting, or sitting on a heel to compress the urethra against it (sometimes called Vincent’s curtsy sign)?
- Post-void dribbling: is there loss of urine immediately after the main void?
Why are holding manoeuvres a finding?
Holding manoeuvres usually mean the child is fighting a detrusor contraction rather than being inattentive or lazy. They raise the tone of the outlet sphincter and relax the detrusor, so a child who squats or crosses the legs is working against a contraction. That is why holding manoeuvres are a diagnostic finding rather than a behavioural quirk.
How many voids a day are normal?
The two extremes point to the two failures. The International Children’s Continence Society treats 4–7 voids a day as normal daytime frequency for a child. So fewer than 4 or more than 7 voids a day suggests a storage or emptying disorder.
Eight or more voids a day, after ruling out high fluid intake and diabetes insipidus, is increased daytime frequency. Three or fewer voids a day is decreased daytime frequency. Both 8 or more and 3 or fewer are abnormal.
What counts as constipation?
The bowel side is the second half of the picture, and it needs its own working definition. Constipation shows as hard, infrequent stools or a palpable faecal mass. The Paris Consensus on Childhood Constipation Terminology (PACCT) defines chronic constipation as at least 2 of the following over the preceding 8 weeks:
- fewer than 3 bowel movements per week
- more than 1 episode of faecal incontinence per week
- a large faecal mass in the rectum, or one palpable on abdominal examination
- stool large enough to obstruct the toilet
- retentive posturing or stool withholding
- painful defecation
How do the Rome IV criteria differ?
The definition in use depends on the reference applied. The Rome IV criteria for functional constipation cover the same domains as PACCT, with age-specific wording. They have a shorter minimum duration, about 1 month.
How does constipation reach the bladder?
Once constipation is defined, the question is how a bowel problem can affect the bladder. The rectum lies behind the bladder, so the two are close neighbours in the pelvis. A proposed explanation is that a loaded rectum presses on the bladder from behind, so the bladder cannot empty completely.
The result is a high residual volume with stasis, functional obstruction and bacterial proliferation. These are the same conditions that predispose to ascending infection. Treating constipation can therefore interrupt a recurrent infection cycle without any change to the kidney or ureter.
Why do bladder-bowel dysfunction and reflux make each other worse?
If the bowel can compress the bladder, the next question is what happens when the bladder also lets urine climb. BBD and reflux are not competing explanations; they compound each other. A probable reason the bowel and bladder problems come together is that they share afferent nerves, similar neural centres and a common embryological origin.
Reflux gives urine a route upwards. A bladder contracting against a full rectum, or emptying incompletely, supplies pressure and residual urine to use that route. Children with both BBD and reflux therefore have a higher risk of recurrent infection and renal damage than children with either alone, and they are at highest risk.
The RIVUR trial studied antibiotic prophylaxis in children with reflux. Children with BBD at baseline had more recurrent urinary infections. The absolute benefit of prophylaxis was also larger in those children.
In what order is the problem treated?
Knowing that the bowel and bladder compound each other sets the order of treatment. Bowel comes first, because a loaded rectum keeps the bladder from emptying. In every toilet-trained child with recurrent infection, the voiding history comes first.
- Take the voiding history in a structured way, ideally supported by a frequency–volume chart of the time and volume of each void.
- Diagnose and treat constipation first, with adequate fluid and fibre, unhurried toilet time after meals, and an osmotic laxative such as polyethylene glycol where needed. This is first-line in a toilet-trained child with recurrent infection, because it addresses the mechanical cause. It is also the one step the family can carry out at home.
- Treat the bladder pattern. Overactive bladder responds to scheduled voiding, bladder training and sometimes anticholinergics. Dysfunctional voiding responds to timed and double voiding, which is a second attempt to void shortly after the first, aimed at the residual urine. Relaxation techniques help too, and in resistant cases pelvic floor physiotherapy.
- Re-image only if symptoms persist after the bowel and bladder are managed.
The order is the bowel, then the bladder, then re-imaging if symptoms persist.
Why is imaging left until the end?
Only after the bowel and bladder have been treated do the scans mean anything. Imaging findings will not be interpretable until the functional problem is treated. The reasoning error to avoid is repeating imaging in a child with recurrent cystitis and unrecognised constipation. A child who holds urine and stool does not need a second cystogram before the bowel has been dealt with. And if the functional problem is treated and reflux is still there, what exactly is the reflux, how is it graded, and when does it need more than treating the bowel and bladder?