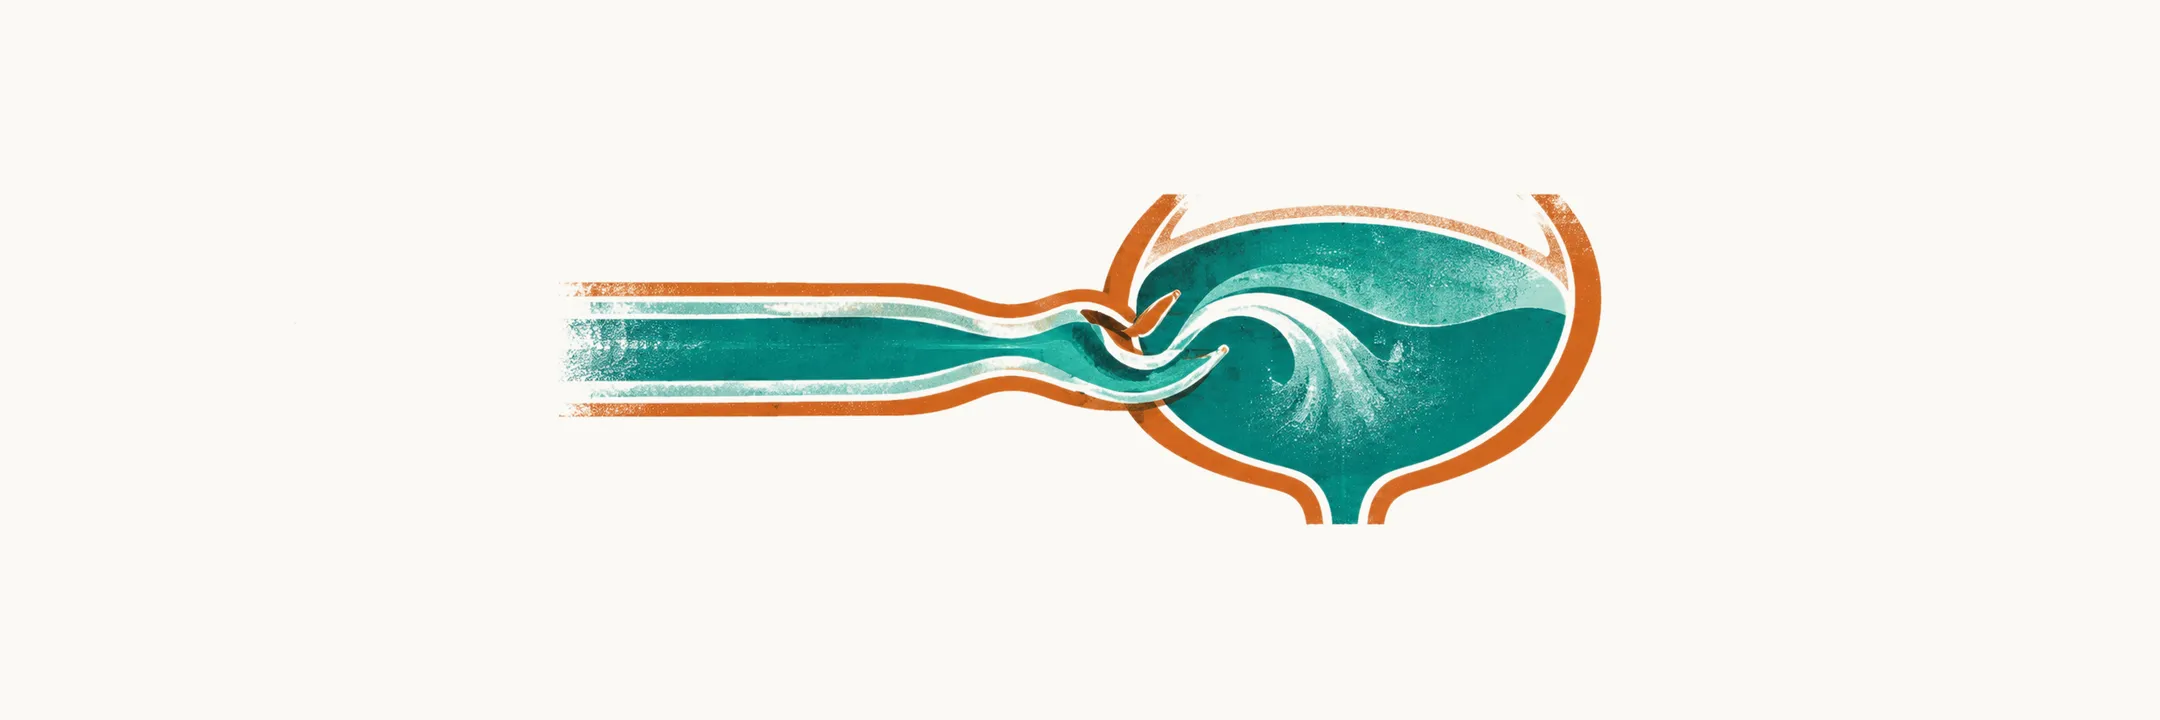
Vesicoureteral reflux (VUR) is retrograde flow of urine from the bladder back up the ureter towards the kidney. It happens because the ureterovesical junction, where the ureter enters the bladder, fails to act as a one-way valve. VUR is the failure of that valve to prevent retrograde flow.
How does the valve normally hold?
The last segment of the ureter does not simply open into the bladder. It runs through the bladder wall in a submucosal tunnel. As the bladder pressure rises during voiding, that segment is compressed against the wall and sealed. So urine can enter the bladder, but it cannot go back up. The valve is passive: it is pressed shut by the very pressure it has to resist. The question is what makes it fail.
What makes the valve fail?
A flap of this kind is thought to hold when the tunnel is long enough for its width. The seal fails when the submucosal tunnel is too short, when the junction is malpositioned, or when bladder pressure is chronically high. A short or badly placed tunnel leaves little to seal the ureter, and sustained high pressure can overwhelm even a sound valve.
So a valve fails either because it was built wrongly or because the pressure outgrows it. The most useful split is by cause, because the cause determines treatment. A short tunnel is a fault built into the junction. High pressure is a driver outside the junction.
Primary reflux: a valve built short
Idiopathic, or primary, reflux is a developmental incompetence of the ureterovesical junction with no other urinary tract disease. It is thought to begin in development, when the ureteric bud arises in an unusual position and leaves an opening to one side and a short tunnel. The typical cause is therefore a short or malpositioned submucosal tunnel.
This kind of reflux tends to behave well. It is usually of lower grade, and it often resolves as the child and the tunnel grow. As the bladder grows, the tunnel is thought to lengthen, and a longer tunnel can seal again.
Secondary reflux: pressure the valve cannot hold against
The second kind is a sound valve overpowered by pressure. Secondary reflux is caused by another abnormality that raises bladder pressure or disturbs the junction. Here the pressure drives the reflux, and high pressure pushes urine back past the valve.
The causes are:
- posterior urethral valves
- neurogenic bladder
- bladder and bowel dysfunction, including overactive and dysfunctional voiding patterns
- previous ureterovesical surgery
As the bladder and bowel note set out, a bladder that cannot empty, or a loaded rectum pressing on it, raises the pressure that drives reflux.
While the pressure stays high, the reflux continues and the kidney keeps taking the strain. So secondary reflux behaves worse. It is of higher grade, it causes more scarring, and it is unlikely to resolve until the underlying problem is corrected.
Posterior urethral valves
The most damaging form of that pressure comes from a valve in the urethra. As the imaging note set out, posterior urethral valves are congenital folds in the posterior urethra of boys that obstruct outflow of urine. As the same note set out, obstruction at the valves raises pressure in the bladder, and that pressure drives urine back up the ureters. The urine is driven backwards into kidneys that are often already dysplastic, and infection is then added on top of the pressure injury. Posterior urethral valves are the most aggressive secondary cause, and the most damaging one.
Because the obstruction is the driver, treating the reflux without relieving the valve obstruction does not work. In one series, reflux resolved after the valves were ablated.
What does reflux do to the kidney?
Whatever the cause, reflux harms the kidney in two ways.
The first is infection. As the foundations note set out, a febrile UTI is infection that has reached the kidney. The valve normally keeps urine from climbing, so when it fails, bacteria in the bladder have a route to the renal parenchyma. Reflux therefore raises the frequency of febrile UTI. Infected urine in the kidney sets off an immune response. Each episode sets off an inflammatory response, and with persistent reflux that response may lead to chronic inflammation and scar. So repeated episodes scar the kidney, and the number of febrile UTIs drives the scarring. In one analysis of 345 children, scarring was present in 2.8% after a single febrile UTI, 25.7% after two, and 28.6% after three or more.
The second is pressure. Infection is not the only mechanism of harm. Sterile urine under sustained high bladder pressure can itself damage the developing kidney, and high-pressure reflux of sterile urine is thought to stunt the normal growth of the kidney. Dysplasia is sometimes found in kidneys draining a high-pressure system before any infection has occurred. A proposed explanation is that pressure on a kidney that is still forming may alter how its tissue develops.
So VUR can damage the kidneys by pressure as well as by infection.
How is reflux graded?
The harm depends on how much reflux there is, so reflux is graded. As the foundations note set out, cystography is the X-ray that follows contrast as the child voids. Reflux is graded on cystography with the International Reflux Study system.
Urine collects in the calyces and then passes into the renal pelvis, and from there into the ureter. The grading system records how far contrast climbs along that route and how much the collecting system dilates.
- Grade I: reflux into the ureter only, with no dilatation.
- Grade II: reflux reaches the renal pelvis and calyces without dilatation.
- Grade III: the ureter and pelvis are dilated, with mild or no blunting of the calyces.
- Grade IV: greater dilatation with tortuosity. The sharp angle of the calyceal fornices is obliterated, but papillary impressions remain visible.
- Grade V: gross dilatation and tortuosity. Papillary impressions are frequently absent.
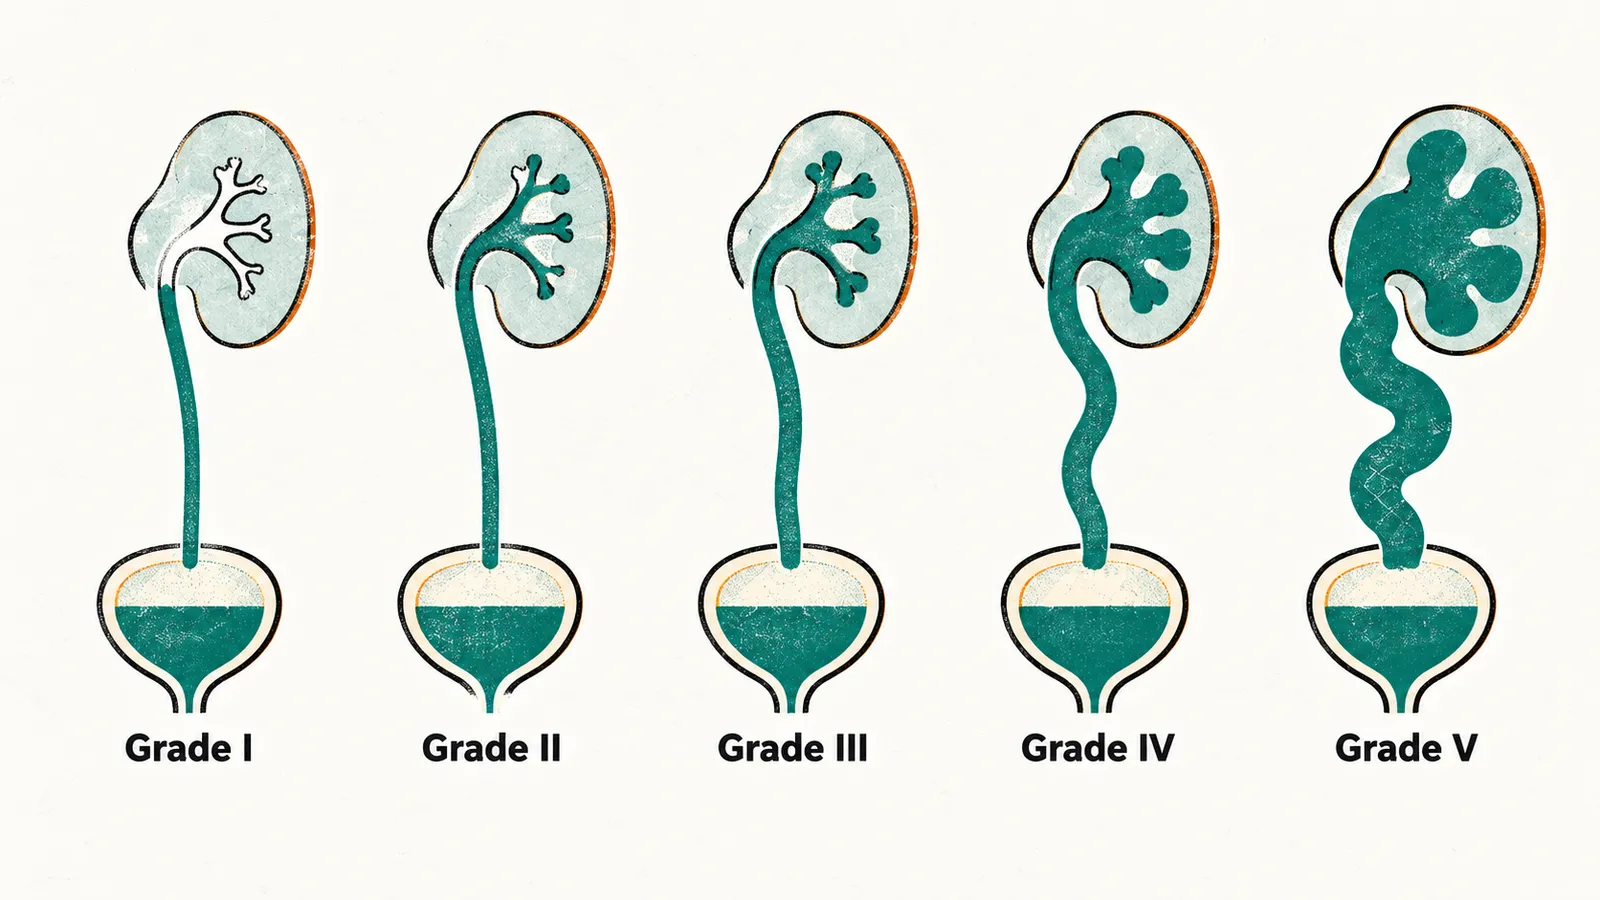
On this scale, grades I and II are usually described as mild, grade III as moderate, and grades IV and V as severe.
Why the grade is not the whole answer
A grade alone does not settle what to do, but it shifts the balance. Lower grades are more likely to resolve spontaneously. Higher grades carry a higher risk of further scarring with each febrile infection.
What is treatment trying to prevent?
The decision follows from what treatment is aiming at. The purpose of treatment is not to correct an image. It is to prevent the next febrile UTI and the next scar. Reflux raises the frequency of febrile UTI, and the number of febrile UTIs drives scarring. Three strategies serve that aim, and they differ in how much they intervene.
Surveillance
Surveillance is for low-grade reflux with no scarring and no recurrence, in a child with normal bladder and bowel function. It is a reasonable choice. It comprises periodic review, education of the family, and prompt treatment of any breakthrough infection.
The reason it fits is that much grade I–II reflux resolves during childhood as the bladder and the submucosal tunnel grow. An early operation would then treat a problem that would have disappeared.
Antibiotic prophylaxis
Prophylaxis is a low daily dose of an agent such as trimethoprim–sulfamethoxazole or nitrofurantoin. It aims to keep the urine sterile during the years of greatest risk, so that fewer infections recur. The RIVUR trial is the key evidence. It enrolled 607 children aged 2–71 months with grade I–IV reflux after a first or second febrile or symptomatic UTI.
- Two years of continuous trimethoprim–sulfamethoxazole reduced recurrent febrile or symptomatic UTI from 23.6% to 12.9% (hazard ratio 0.50, 95% confidence interval [CI] 0.34–0.74).
- It did not reduce new renal scarring (8.2% versus 8.4%).
- Resistance rose in the treatment group: 63% versus 19% of first recurrent E. coli isolates were trimethoprim–sulfamethoxazole resistant.
In short, prophylaxis halved recurrent UTI but did not reduce scarring, and it increased antibiotic resistance. Prophylaxis is a reasonable option for reducing recurrence in selected higher-risk children. It is not a default for every child with reflux, and it carries a resistance cost.
Surgery
Surgery is considered for high-grade reflux, for breakthrough febrile UTIs despite prophylaxis, for progressive scarring, or for secondary reflux with a correctable cause.
The classic operation is ureteral reimplantation. The ureter is reimplanted so that it runs through a newly built, longer submucosal tunnel, which restores the valve mechanism. That is the goal of the operation.
Endoscopic injection of a bulking agent at the ureterovesical junction is a less invasive alternative for selected moderate grades. The agent is thought to change the angle at the junction and so add resistance to reflux, though the precise mechanism is not settled. It has a lower success rate per procedure.
Secondary reflux: treat the cause first
None of the three options touches a pressure source that is still there, so the cause comes first. In secondary reflux the pressure comes from the cause, and the first step is to treat it: endoscopic ablation of posterior urethral valves, management of a neurogenic bladder, which means keeping bladder pressures low, or treatment of bladder and bowel dysfunction.
This explains why grade IV reflux caused by posterior urethral valves and grade IV reflux in a child with an overactive bladder and constipation do not have the same solution, even though the images look alike. The grade shows the appearance of the reflux, and the source of the pressure decides the treatment. Idiopathic reflux often resolves, while secondary reflux usually needs the underlying cause fixed.
Which child needs intervention?
The question is not surgery or no surgery, but which child needs intervention to prevent the next febrile UTI and the next scar. The judgement rests on the grade, the age, whether scarring is already present, how often infections recur, and whether the underlying cause is treatable. Treatment is aimed at preventing febrile UTI and scarring, and it depends on grade, age, scarring, recurrence and cause together. Since the most damaging cause of secondary reflux is a blockage in the urethra, how does that blockage damage a developing kidney, and why does it need relief before anything else?