One blood sample can mislead, so how is each axis actually tested?
How do you test a gland that may fail only under demand?
Each pituitary axis has two ends: a pituitary hormone and the hormone of its target gland. The pituitary is a relay, so an axis is read as both together. If the target-gland hormone is low and the pituitary hormone is not appropriately raised, the fault lies in the pituitary or the hypothalamus.
Confirming hypopituitarism requires testing the pituitary axes at rest and after stimulation. A gland can produce enough at rest and still fail when it is pushed, so a baseline value can look normal. A stimulated (dynamic) test measures the gland’s reserve. For each hormone, the basal and the stimulated (dynamic) level are checked.
Basal testing means measuring the serum concentration of the anterior pituitary hormones and of their target-gland hormones. The blood sample is taken unstressed, between 7 and 9 am. That is the window when serum cortisol and testosterone are highest, so a low value drawn then carries more meaning than one drawn at another time of day.
Which basal levels are checked for each axis?
Each axis is a pituitary hormone plus a target-gland hormone, and the tests follow that pairing:
| Axis | Basal tests |
|---|---|
| Adrenocortical | Morning serum cortisol, ACTH |
| Thyroid | Free T4, TSH |
| Gonadal, men | Testosterone (09.00 AM), SHBG, LH, FSH |
| Gonadal, women | Estradiol, LH, FSH, progesterone (day 21 if menstruating) |
| Prolactin | Prolactin level |
| Growth | Insulin-like growth factor-1, growth hormone |
| Fluid balance | Paired plasma and urine osmolality |
LH and FSH are released in pulses, so a single gonadotropin value can mislead. GH is also released in pulses, so a single level can fall between peaks. IGF-1 is made in response to GH, which makes it a steadier measure than GH itself. Prolactin may be raised when the stalk is disrupted, because the hypothalamic dopamine brake is lost. Without ADH the kidney cannot concentrate urine, which is why urine concentration is compared with plasma osmolality.
How is ACTH deficiency confirmed?
What does ACTH show?
In central (secondary) hypoadrenalism the pituitary makes too little ACTH, so the adrenal cortex is not driven. ACTH can therefore be low or low-normal, and a low or low-normal ACTH does not exclude the diagnosis.
ACTH is still the gold-standard biomarker for distinguishing primary from secondary hypoadrenalism. With low cortisol, ACTH normally rises because the brake is off. That is why in primary disease ACTH is inappropriately high, and in central disease it is not.
What does the morning cortisol decide?
When ACTH deficiency is suspected, the basal cortisol at 9 am decides the next step. It sorts the patient into three bands:
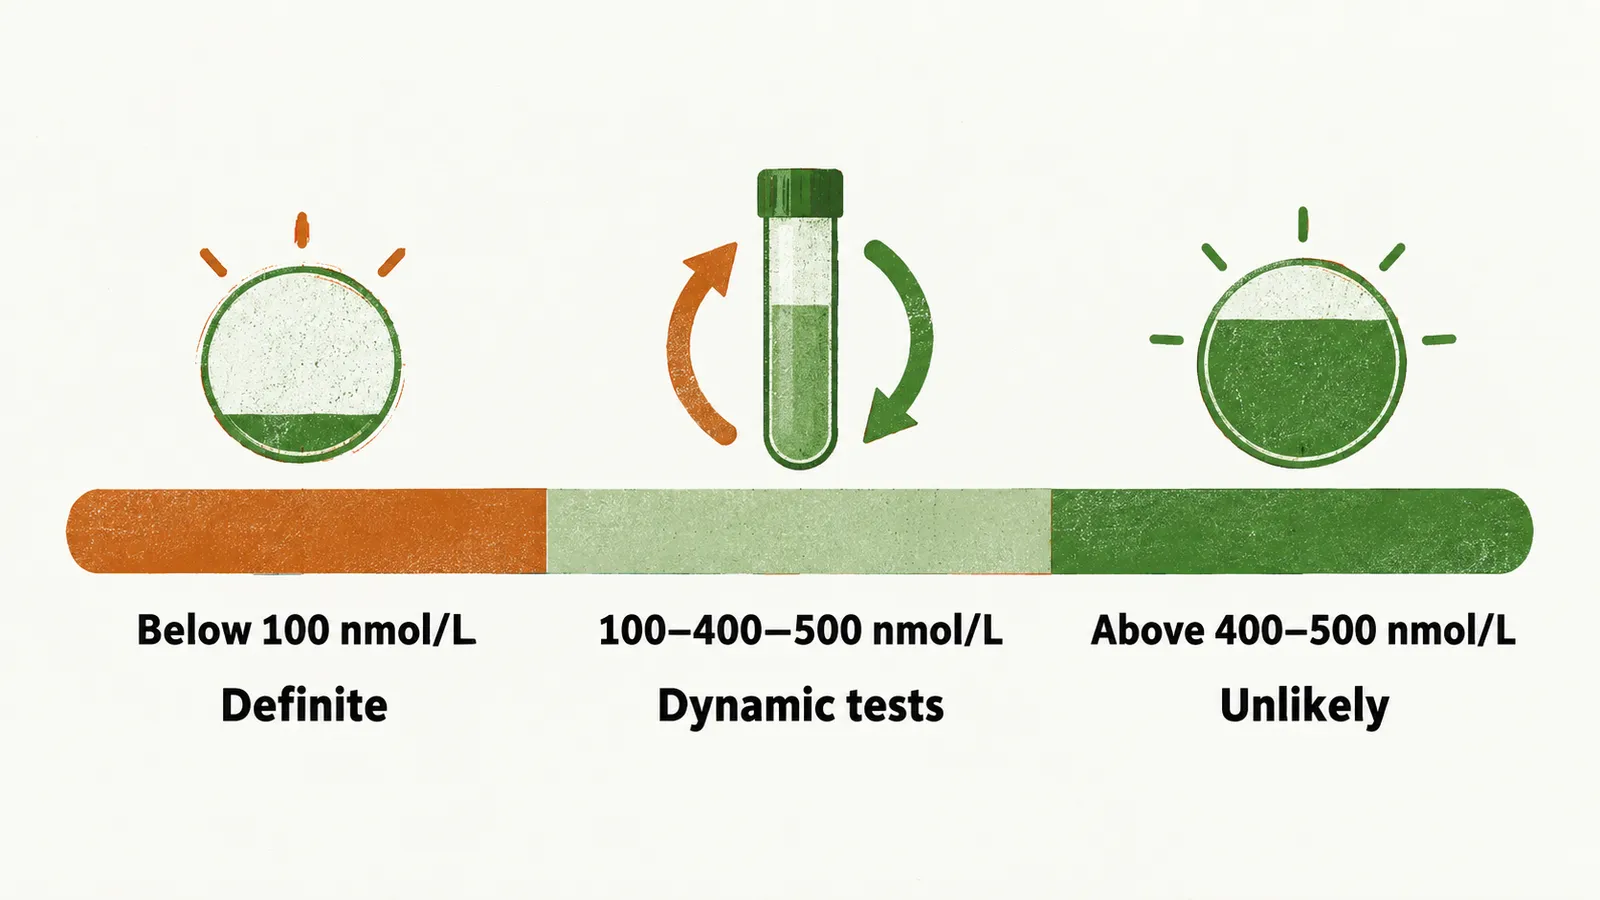
- Below 100 nmol/L (3.625 µg/dL): ACTH deficiency is definite. A cortisol this low at the daily peak leaves little room for adequate adrenal output.
- Above 400–500 nmol/L (14.5–18.1 µg/dL): ACTH deficiency is unlikely. A cortisol this high at the daily peak argues against significant failure.
- Between 100 nmol/L (3.625 µg/dL) and 400–500 nmol/L (14.5–18.1 µg/dL): dynamic tests are needed to confirm. In this middle range the gland may be only partly failing, so its output at rest does not settle the question.
What is the insulin tolerance test?
In the grey zone of basal cortisol, the insulin tolerance test (ITT) can be used. Induced hypoglycaemia stimulates the axis, and the pituitary-adrenal axis is what is being tested. The result is interpretable only if the induced glucose fell below 40 mg/dL, because only an adequate hypoglycaemia is a real stimulus.
The ITT is contraindicated in suspected secondary hypoadrenalism, and an ACTH stimulation test is performed instead. The ITT is a hazardous test, and it is contraindicated in patients with a history of seizures or heart disease, so an alternative is needed.
What is the ACTH stimulation test?
In this test a synthetic ACTH is given and the adrenal’s cortisol response is read. In normal subjects, the ACTH stimulation test raises blood cortisol above 500 nmol/L (18 µg/dL). This is the traditional threshold for a normal response, and it came from the responses of healthy volunteers.
The test can work in central failure because an adrenal cortex that has not been stimulated for a long time loses its response only gradually. The test therefore reads an adrenal that the missing ACTH has stopped driving.
Why is the insulin tolerance test preferred for ACTH and GH?
The ITT is also the test of choice for growth hormone. Several tests measure dynamic changes of pituitary hormones, but the ITT is still preferred because it measures the dynamic changes of ACTH and GH at the same time.
The reason is that insulin-induced hypoglycaemia is a potent stimulator of pituitary hormone release. Because of this, one ITT can measure the reserve of both GH and ACTH.
How is GH deficiency confirmed when the ITT cannot be used, and what about IGF-1?
The ITT is contraindicated in suspected growth hormone deficiency (GHD), and the recommended test is then the arginine plus GHRH combination. GHRH is the hypothalamic signal that drives GH, and arginine is thought to inhibit somatostatin tone, so together they give a powerful stimulus. Thyroid and adrenal hormones must be normal before GH testing.
The result is judged against the patient’s BMI. Obesity blunts the GH response to stimulation, so the cut-off is lower as BMI rises. The reason for the blunting is unknown.
- BMI below 25: GH below 11 microgram/L
- BMI between 25 and 30: GH below 8 microgram/L
- BMI above 30: GH below 4 microgram/L
IGF-1 offers a simpler measure, since it is made in response to GH. For the diagnosis of GHD it is highly specific but not sensitive. In practice this means a low value is meaningful and a normal value does not exclude the diagnosis. A low IGF-1 is enough to confirm GHD.
A normal or low-normal IGF-1 is quite common in GHD patients, so it cannot rule out the diagnosis. The overlap is probably explained by the fall of IGF-1 during physiological aging. A proposed explanation is that with aging the age-adjusted reference values and the pathological decrease of GHD come close together.
Why does the thyroid axis need TSH and FT4 together?
The thyroid axis is assessed with basal measurements, so the difficulty lies in interpreting them, not in the test. Two measurements are made: TSH and free thyroxine (FT4). TSH can be measured directly because of its relatively long half-life.
In primary disease the thyroid itself is at fault, so TSH moves in the expected direction. The laboratory method starts with TSH, and if it is high or low, FT4 follows. The combination of TSH and FT4 then guides the diagnosis of primary hyper- or hypothyroidism. Suspected secondary hypothyroidism cannot be approached the same way.
In central hypothyroidism the thyroid is normal but under-stimulated. Yet in the great majority of patients TSH is normal or even slightly increased, so TSH alone looks reassuring. The reason is that the anterior pituitary forms biologically inactive TSH: enough TSH is present, but it is not biologically active.
So central hypothyroidism is diagnosed by the simultaneous measurement of TSH and FT4, not by measuring TSH first and FT4 only when TSH is abnormal. A normal TSH with a low FT4 shows that the thyroid is under-stimulated.
Per guidelines, mild central hypothyroidism is suggested by a borderline FT4 with an inappropriately low or low-normal TSH. The numbers alone are not enough, so the patient also needs some other supportive evidence.
Once the missing axes are confirmed, how is each hormone replaced, and why does the order of replacement matter?