
What does treatment replace?
In hypopituitarism the pituitary is the failing part, and it works as a relay: its hormones drive the thyroid, the adrenal glands and the gonads. The glands downstream are intact but unstimulated, and each failing axis therefore shows as target-gland failure. Once hypopituitarism is established it is usually permanent, so treatment is lifelong replacement of the hormones each failing axis can no longer make.
The pituitary itself is not mended, and its own hormones are mostly not given. Replacement uses the target-gland hormone, because the target gland is still able to respond to it:
- Hydrocortisone (cortisol) for the adrenal cortex.
- Levothyroxine (thyroxine) for the thyroid.
- Sex steroid for the gonads.
- Desmopressin, a synthetic analogue of antidiuretic hormone, for the kidney in antidiuretic hormone deficiency.
There are two exceptions to target-gland replacement: growth hormone and fertility treatment. Growth hormone is the pituitary’s own product, and for fertility the gonads have to be stimulated, which a steroid cannot do. Both come later.
Replacement cannot reproduce normal physiology exactly, because the body adjusts its hormones continuously and a tablet does not. So doses are adjusted to relieve the symptoms of deficiency without producing the effects of excess. This raises the first practical question, for the hormone that matters most.
How is the adrenal axis replaced?
Loss of the ACTH axis leaves the adrenal cortex unable to raise cortisol in response to stress. Hydrocortisone is the usual glucocorticoid replacement, at 15-25 mg total per day. It is given in two or three divided doses. The largest dose is given on waking, to imitate the natural early-morning cortisol peak. Prednisolone 3-5 mg once daily is an alternative; it is longer acting, so a single daily dose is possible.
Why is no mineralocorticoid needed?
The adrenal cortex makes more than one hormone. Aldosterone secretion is controlled by the renin-angiotensin system, not by ACTH, and it remains intact. Mineralocorticoid replacement is therefore not needed, and the hyperkalaemia of primary adrenal insufficiency does not appear in hypopituitarism.
What does the patient do when the body needs more cortisol?
A fixed hydrocortisone dose covers baseline needs, but stress needs more, and without ACTH the cortex cannot raise cortisol by itself. Glucocorticoid replacement therefore only works if the patient can increase the dose during stress. Doses are doubled or tripled during febrile illness. With vomiting or diarrhoea, oral hydrocortisone may not be absorbed, so intramuscular injection is used instead.
Because others may have to act for the patient, the preparation is part of treatment:
- Patients carry a steroid card or medical-alert identification.
- Patients carry an emergency hydrocortisone injection.
- Patients and families are taught when to use them.
Why does the order of starting matter when several axes fail?
Thyroid and adrenal replacement can interact. Thyroid hormone accelerates the metabolism of cortisol. When several axes fail together, hydrocortisone is therefore started before levothyroxine: starting levothyroxine with an untreated adrenal axis can provoke adrenal crisis.
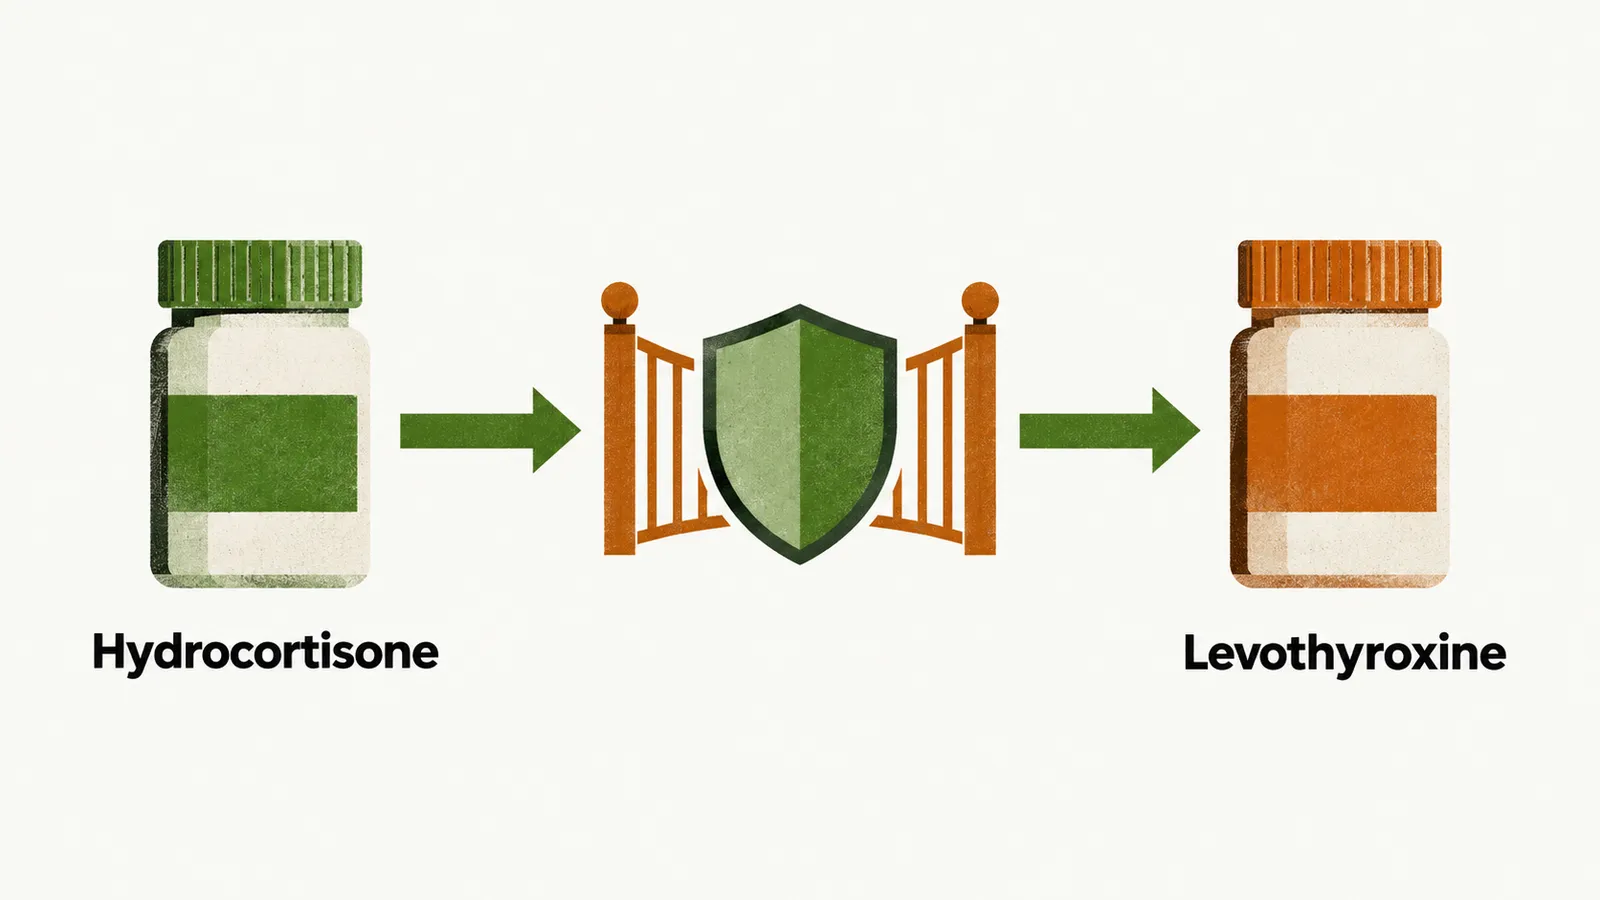
The same caution applies to growth hormone. Growth hormone can unmask central hypothyroidism or occult ACTH deficiency, so the thyroid and adrenal axes are assessed and treated first.
How is the thyroid axis replaced?
Once the adrenal axis is safe, central hypothyroidism is treated with levothyroxine once daily. The dose is guided by free T4, not TSH, because TSH cannot report the adequacy of replacement when the pituitary is the failing organ. The target free T4 is the upper half of the reference range.
Some patients need a gentler start. With a long history of hypopituitarism, or with ischaemic heart disease, the starting dose is low, such as 25-50 microgram daily, and is then increased gradually. A low start reduces the risk of precipitating cardiac events.
How are the gonads replaced, and when does the approach change?
In gonadotropin deficiency the gonads are intact but unstimulated, because the signal that drives them is missing. Sex steroids are therefore replaced directly.
Women under 50 are offered oestrogen replacement. Its aims are to relieve the symptoms of oestrogen deficiency and to protect bone mineral density. A progestogen is added if the uterus is present, to protect the endometrium. Transdermal oestrogen is preferred, because it avoids the first-pass effects of oral oestrogen and mimics normal ovarian release better. Men receive testosterone.
When fertility is the goal, the approach changes. A sex steroid does not make sperm or trigger ovulation, so the gonads themselves have to be driven. Fertility treatment uses gonadotropin injections or pulsatile gonadotropin-releasing hormone (GnRH). These stimulate the gonads rather than substitute for the end hormone. Pulsatile GnRH can work only if the pituitary can still answer it.
When is growth hormone given?
Growth hormone is the other exception to target-gland replacement, because it is the pituitary’s own product. Recombinant growth hormone is used in confirmed growth hormone deficiency. The dose is individualised, and treatment is monitored through IGF-1 and clinical response; growth hormone acts partly through IGF-1. Growth hormone is not started in active malignancy.
How is water balance replaced, and what can go wrong?
Antidiuretic hormone is made in the hypothalamus and released from the posterior lobe, and its loss shows as polyuria and thirst, including at night. Central antidiuretic hormone deficiency is treated with desmopressin, a synthetic analogue given intranasally, orally or subcutaneously.
Over-replacement suppresses urinary water loss while the patient continues to drink, and this causes hyponatraemia. The dose is therefore kept to the smallest that controls polyuria, including nocturia.
What are the emergencies?
Replacement fails when a stress outruns it or when the gland is destroyed all at once. There are two endocrine emergencies in this group: adrenal crisis and pituitary apoplexy. In both, glucocorticoid is given immediately. In both, ACTH and so cortisol are lost, and cortisol is associated with the vascular response to catecholamines, so its loss threatens the circulation.
Adrenal crisis is the acute failure of cortisol that stress dosing is meant to prevent. Untreated, it is life-threatening. Hydrocortisone 100 mg is given intravenously or intramuscularly without waiting for confirmatory tests, followed by 200 mg over 24 hours, together with rapid isotonic saline to restore circulating volume.
Pituitary apoplexy is also treated with glucocorticoid immediately; high-dose steroid has an anti-inflammatory and anti-oedema effect as well. The sella is a bony cup with no room to expand, so a swollen gland presses on the optic nerves above it. Urgent transsphenoidal decompression is considered for severe, persistent or worsening visual loss, because a visual deficit that is not relieved can become permanent.
How are patients followed up?
After treatment starts, dosing is checked against the patient. Follow-up is clinical as much as biochemical. Weight, postural blood pressure, energy and signs of over-replacement guide the glucocorticoid dose. Free T4 guides levothyroxine, and IGF-1 guides growth hormone. Patients are reviewed at least once a year. The replacement plan is adjusted for pregnancy, surgery and intercurrent illness, when the body’s demands change.
Each axis has its own hormone, its own dose and its own marker, so how does a clinician keep the whole patient in view? That is the question Hypopituitarism sets out to orient.