A child has a sore throat caused by group A Streptococcus. The throat gets better. Then, 2-4 weeks after it has resolved, the child falls ill again with acute rheumatic fever. It occurs in a genetically susceptible child, and it produces inflammation in the joints, skin, brain and heart.
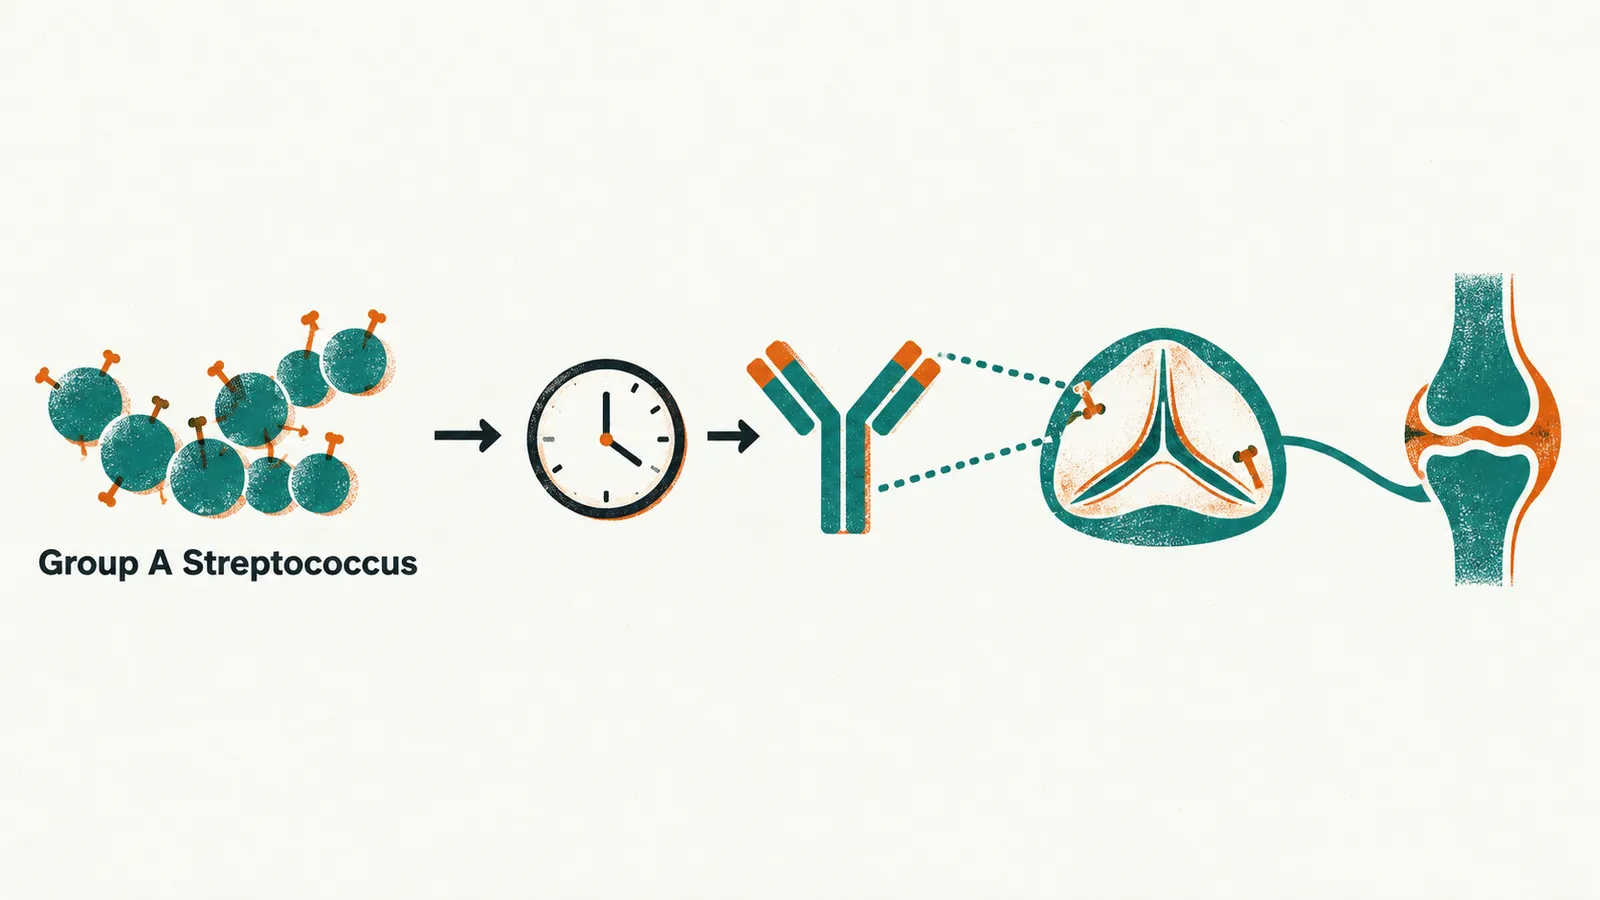
The picture to hold is this: the immune system makes antibodies against the bacterium, some of the bacterium’s surface proteins look like the child’s own tissue, and the response then turns on that tissue. Joints and rash recover. Heart valves may not.
Why does the illness come after the sore throat has gone?
The trigger is pharyngitis caused by group A Streptococcus (Streptococcus pyogenes). The damage is done by the immune response rather than by the bacterium. An immune reaction takes time to build, so the attack appears after the sore throat has cleared. If the bacterium is gone, what is the immune system still aiming at?
Which strains matter, and what do they look like?
The answer lies in the bacterium’s surface. Only certain strains are thought able to cause the disease, and they are called rheumatogenic strains. They are distinguished largely by the structure of the M protein, which the emm gene encodes.
Some M protein classes resemble components of human connective tissue. This resemblance is the structural basis for the cross-reaction that follows. So the antibodies are matching the child’s own tissue, and the question is why that happens.
Why do the antibodies turn on the body?
Antibodies raised against streptococcal antigens cross-react with host tissue, particularly the heart valve endothelium and the myocardium. They cross-react because the two look alike to the immune system. This molecular mimicry is thought to be the mechanism behind rheumatic carditis and its long-term valvular consequences.
Two conditions usually need to be met. The first is infection with a rheumatogenic strain of group A Streptococcus. The second is genetic susceptibility in the host. Neither alone is enough: genetic susceptibility alone does not cause the disease, and infection alone does not either. Why does one child with this infection develop the disease, and another not?
Who is at risk?
Susceptibility is the other half of the cause. Associations have been reported with class II HLA alleles, including HLA-DR7, and the disease clusters in families beyond what shared environment would explain.
The peak age is 5-15 years, and the disease is uncommon before 3 years of age. The seasonal variation follows that of group A streptococcal pharyngitis: late winter and early spring in temperate climates. The incidence follows the incidence of untreated streptococcal pharyngitis. It is concentrated in low- and middle-income countries and in populations with crowded housing and limited access to care. Some of the highest rates in the world have been reported in Aboriginal and Torres Strait Islander children in northern and central Australia, with an incidence in children aged 5-14 years of up to 150-380 per 100,000 per year.
Skin infection with group A Streptococcus is also implicated as a trigger, particularly in high-incidence settings. Whether treating skin infection prevents rheumatic fever is not established.
Where the disease is common changes how it is diagnosed. The 2015 diagnostic criteria divide the world into low-risk and moderate- to high-risk populations. Threshold numbers decide whether a single inflamed joint, or joint pain alone, counts as a major manifestation, that is, one of the findings that carry most weight in the diagnosis. Most of Western Europe, North America and Italy are classified as low-risk. Much of Asia, Africa, the Pacific and Indigenous Australian populations are not low-risk.
Streptococcal extracellular products (streptolysin O, streptolysin S, streptokinase, hyaluronidase and DNases) can also damage tissue directly. They are thought to contribute to the early fever and the general inflammatory state.
Once the reaction has started, where does it go?
What does the reaction do to joints and skin?
The tissue affected is connective tissue. The pattern of involvement explains the clinical picture. Three mechanisms are described, and separating them is useful because each maps onto different organs. One of them is immune complex deposition: circulating antigen-antibody complexes deposit in the synovium and skin. This produces the arthritis and the characteristic rashes. It is also why anti-inflammatory drugs control the joint disease so quickly and yet do nothing for the valves.
There are five major manifestations: arthritis, carditis, erythema marginatum, subcutaneous nodules and Sydenham’s chorea. They do not arrive together. They appear at different times after the infection and with very different frequencies. Arthritis is the one that brings the child to medical attention, and carditis is the one that changes the long-term prognosis.
Arthritis is the most common major manifestation in most series, and it is early, about 1-3 weeks after the pharyngitis. The latency after the pharyngitis is typically 2-3 weeks. It affects the large joints: knee, ankle, elbow and wrist. It rarely affects the small joints of the hands and feet. It is migratory, transient and asymmetric: one knee is inflamed for a few days and settles as another joint becomes involved. The classic signs of inflammation are present: pain, swelling, heat, redness and loss of function. The arthritis responds dramatically to anti-inflammatory drugs. Monoarthritis does not exclude the diagnosis, particularly in populations at moderate or high risk.
After a sore throat, other diagnoses can explain joint inflammation, and each differs in a checkable way:
- Juvenile idiopathic arthritis is persistent rather than migratory, and the polyarticular form involves the small joints symmetrically.
- Post-infectious reactive arthritis develops during the infection rather than after it, and the inflammatory markers are normal in many cases.
- Septic arthritis is a single hot joint that requires aspiration.
- Tuberculous arthritis is slower and monoarticular.
- Lyme disease comes with a history of tick exposure.
Erythema marginatum is uncommon, in under 10%, and it comes later. The rash is non-pruritic and barely raised, made of reddish rings with a pale centre. The rings are 1-2 cm across and lie on the trunk and proximal limbs. The rash is often described as evanescent. It can be confused with the migratory erythema of early Lyme disease, and the two are separated by a history of tick exposure.
Subcutaneous nodules are also uncommon, in under 10%, and also later. They are firm and painless, 0.5-2 cm across, and lie over tendons and bony prominences. They move with the skin and resolve spontaneously. They also occur in juvenile idiopathic arthritis and systemic lupus erythematosus, so they are not specific on their own.
Joints and skin recover, but the heart valves may not. What does the heart look like?
What happens in the heart?
The valves are where the lasting damage occurs. Carditis determines whether the child will need heart surgery or lifelong prophylaxis. It occurs in roughly half of cases, and in more when echocardiography is used systematically. It is early, about 1-3 weeks after the pharyngitis.
The spectrum of carditis is wide:
- The endocardium shows valvulitis. In most cases it is the primary site.
- The myocardium shows myocarditis, which is part of the pancarditis seen in severe cases.
- The pericardium shows pericarditis.
The mitral valve is most commonly affected, followed by the aortic valve.
The classic clinical finding is a new murmur of mitral or aortic regurgitation. This fits the damage: a valve whose cusps are rigid and deformed does not close fully, so blood leaks back. Regurgitation is far more typical than stenosis, which belongs to the late, chronic phase.
Echocardiography detects valvular regurgitation even when no murmur is audible. The 2015 revision of the diagnostic criteria accepts subclinical carditis as a major manifestation. Doppler echocardiography is recommended in every child with suspected rheumatic fever.
On the ECG, first-degree atrioventricular block (a prolonged PR interval) is the most common finding. Second- and third-degree block occur but are much less common. Severe carditis can present with heart failure and cardiomegaly, and it may be fatal during the acute episode, although death in the acute phase is rare overall.
The same reaction can also reach the brain. How does the brain change?
What happens in the brain?
The basal ganglia are a second target of the same reaction. The result is Sydenham’s chorea. It is thought to come from antibodies that cross-react with the basal ganglia, and these structures control movement, so the cross-reaction shows as involuntary movement.
Sydenham’s chorea is the rarest and most difficult manifestation to recognise. It appears weeks to months after the streptococcal infection, often so long afterwards that the sore throat has been forgotten.
The child shows behavioural change: irritability, emotional lability, agitation and difficulty concentrating. The motor signs are uncoordinated, purposeless, involuntary movements, especially of the hands and face. The handwriting deteriorates, and the face grimaces. The movements disappear during sleep and are worsened by emotional stress. Chorea is more common in girls.
Echocardiography is often revealing. Most children with chorea have valvular involvement even when no murmur is heard. Unexplained chorea in a school-age girl with mitral regurgitation on echocardiography is a strong pointer to rheumatic fever.
Because the latency is so long, serological evidence of the preceding infection may have disappeared by the time the chorea appears. A normal antistreptolysin O titre does not argue against the diagnosis in chorea.
What is left afterwards?
The valve is the lasting damage. The acute episode is usually survivable, and the arthritis and rash resolve without permanent damage. Prognosis is decided by the heart. Valve regurgitation may resolve, or it may progress to scarring and stenosis over years to decades. Later complications include heart failure, atrial fibrillation and infective endocarditis.
Chronic rheumatic heart disease remains a leading cause of acquired heart disease in children worldwide. It is the reason a sore throat is treated with a full antibiotic course. Each recurrence of rheumatic fever adds further valve damage, so what happens after the first attack matters as much as the attack itself. That is why regular cardiology follow-up, adherence to prophylaxis and dental hygiene all matter.
Because the valve damage cannot be undone, recognising the disease during the acute episode is what makes treatment and later prophylaxis possible. Diagnosis rests on criteria applied to a clinical picture rather than on any single test, and the balance of manifestations, not the severity of the sore throat, identifies the child. If no single finding proves the disease, how do doctors put the picture together? The answer is in Diagnosing Acute Rheumatic Fever.