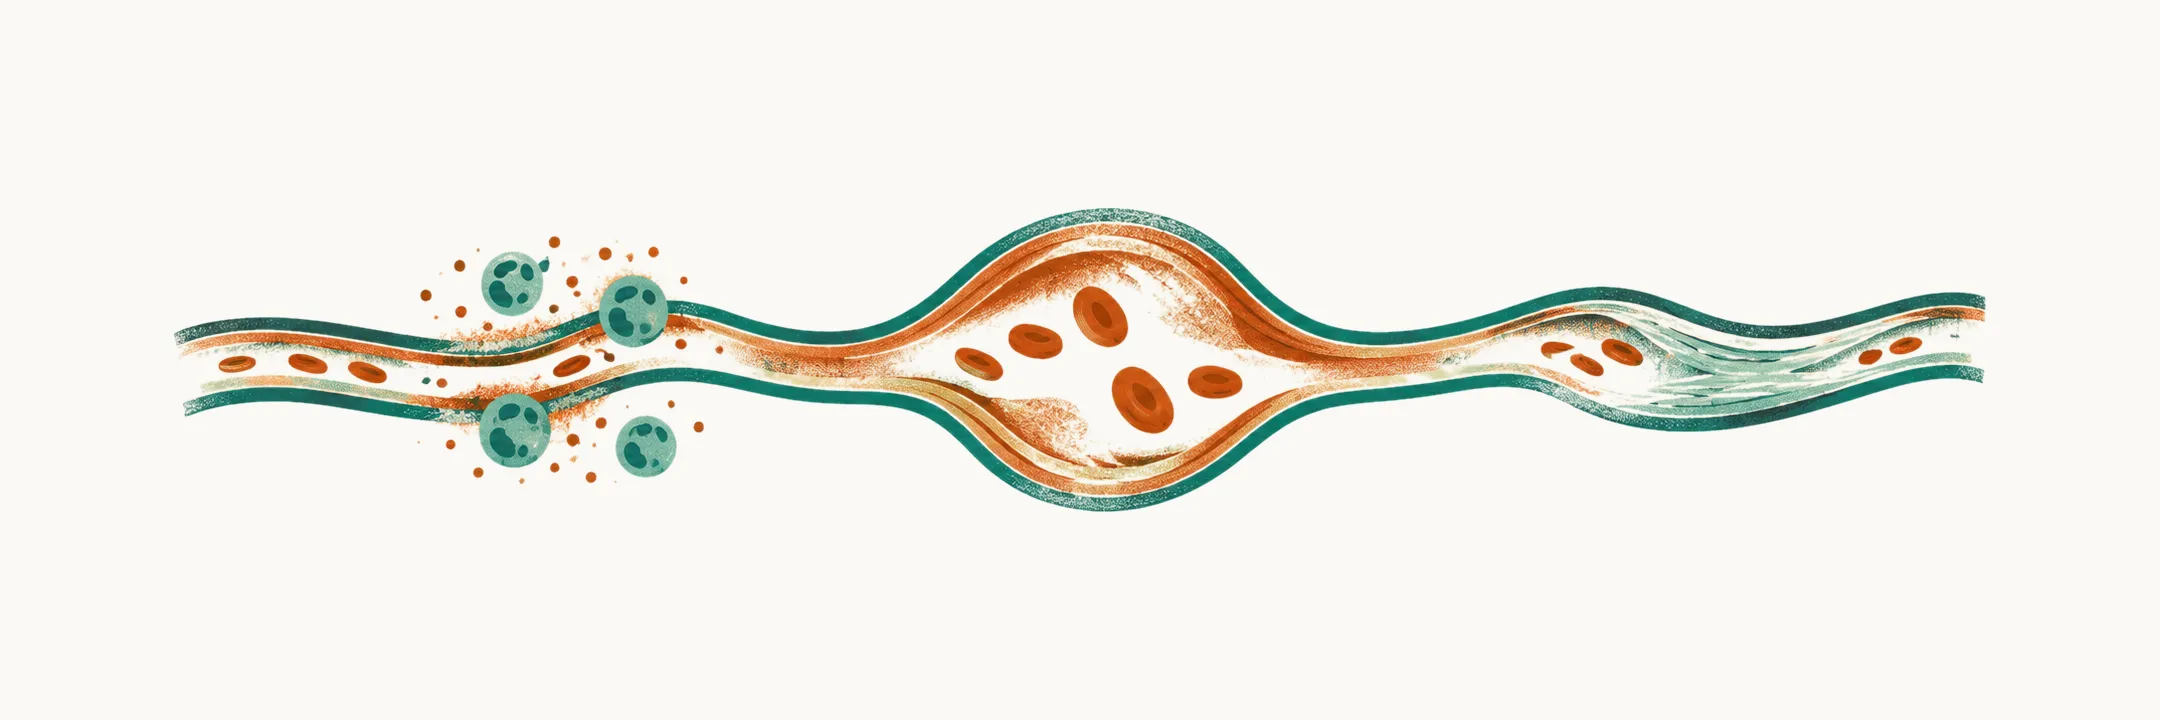
Kawasaki disease is an acute, self-limiting vasculitis of medium-sized arteries. In this disease, the arteries most harmed are the coronary arteries.
The coronary arteries carry blood to the heart muscle itself. Inflammation weakens an arterial wall, and a weakened segment stretches and bulges under the pressure of the blood inside it. This is how an aneurysm forms. A bulge can hold a clot, and a clot can block the artery and starve the heart muscle it feeds. So the fever, rash and red eyes are the visible part of the illness, but the danger lies in the coronary wall.
Why the coronary arteries?
The importance of the disease comes from this one target. Untreated, roughly a quarter of children develop coronary artery dilation or aneurysm, because the inflamed wall gives way where it is weakest. Aneurysms can thrombose years later, because a clot can form inside the aneurysm and block the artery. Treatment changes this. When a child receives IVIG inside the correct time window, the great majority recover with normal coronary arteries.
The benefit depends on timing, so the first task is to recognise the disease. Which children does it strike?
Which children does it strike?
Recognising Kawasaki disease starts with knowing which children are at risk. It occurs almost entirely in young children, and it is a disease of the first years of life. The peak incidence is between 9 and 11 months of age. About 80% of patients are under 5 years old, and roughly half are under 2 years. Boys are affected somewhat more often than girls.
The incidence varies enormously with geography and ancestry. Japan has the highest reported rate in the world: approximately 359 per 100,000 children aged 0-4 in 2018. Korea and Taiwan follow. In the continental United States the figure is approximately 9 to 20 per 100,000 children under 5. Children of East Asian ancestry have a higher risk wherever they live. A risk that follows ancestry rather than place points to a genetic contribution rather than a purely environmental one. If inheritance sets the risk, what sets the disease off?
What sets it off?
Cases cluster in winter and spring in temperate climates, and outbreaks occur. A respiratory or other febrile illness in the 2-3 weeks before the classic features begin is commonly reported. A febrile illness just before onset fits a trigger that is probably infectious. These patterns suggest an infectious trigger acting in a genetically susceptible child.
No single organism has been identified, so the link to infection is inferred from the pattern rather than from a germ. The disease is not transmitted in any simple person-to-person way. With no germ found, what keeps the fever going?
Why does the fever not respond?
The fever is high and sustained, and it is typically poorly responsive to antipyretics and to antibiotics. Untreated, the fever lasts at least 5 days.
This explains a common story. Most children have had a course of antibiotics for a presumed bacterial infection before the diagnosis, and the diagnosis is usually reached only after that course has failed. So what does the illness look like?
What does it look like?
Five principal features accompany the fever.
The first is bilateral conjunctival injection. Unilateral or exudative conjunctivitis argues against the diagnosis.
The second is a change in the oral cavity. The lips are dry, cracked and fissured, sometimes with blood crusts. The tongue shows a strawberry tongue. The pharynx is hyperaemic, without vesicles or tonsillar exudate.
The third is a polymorphous rash. It is a pink maculopapular exanthem of the trunk and limbs. The rash is not specific to the disease, and it is easily mistaken for a viral rash.
The fourth is a change in the extremities. During the febrile phase the hands and feet show erythema and oedema, often more prominent on the feet. Periungual desquamation of the fingers and toes appears 2-3 weeks later. It is highly suggestive of Kawasaki disease, but it appears too late to count towards the diagnostic criteria. It is most useful retrospectively, in a child whose fever has already settled.
The fifth is cervical lymphadenopathy. It is usually unilateral, one node or one side of the neck. Bilateral or generalised lymphadenopathy suggests another diagnosis.
Other findings are common in these children but do not count. Which are they?
Which findings do not count?
These findings do not count towards the diagnosis:
- marked irritability
- abdominal pain
- vomiting or diarrhoea
- arthralgia or arthritis
- sterile pyuria
- aseptic meningitis
- hydrops of the gallbladder
The five principal features and these extra findings do not all appear at once. How does the illness change over time?
How does it change over time?
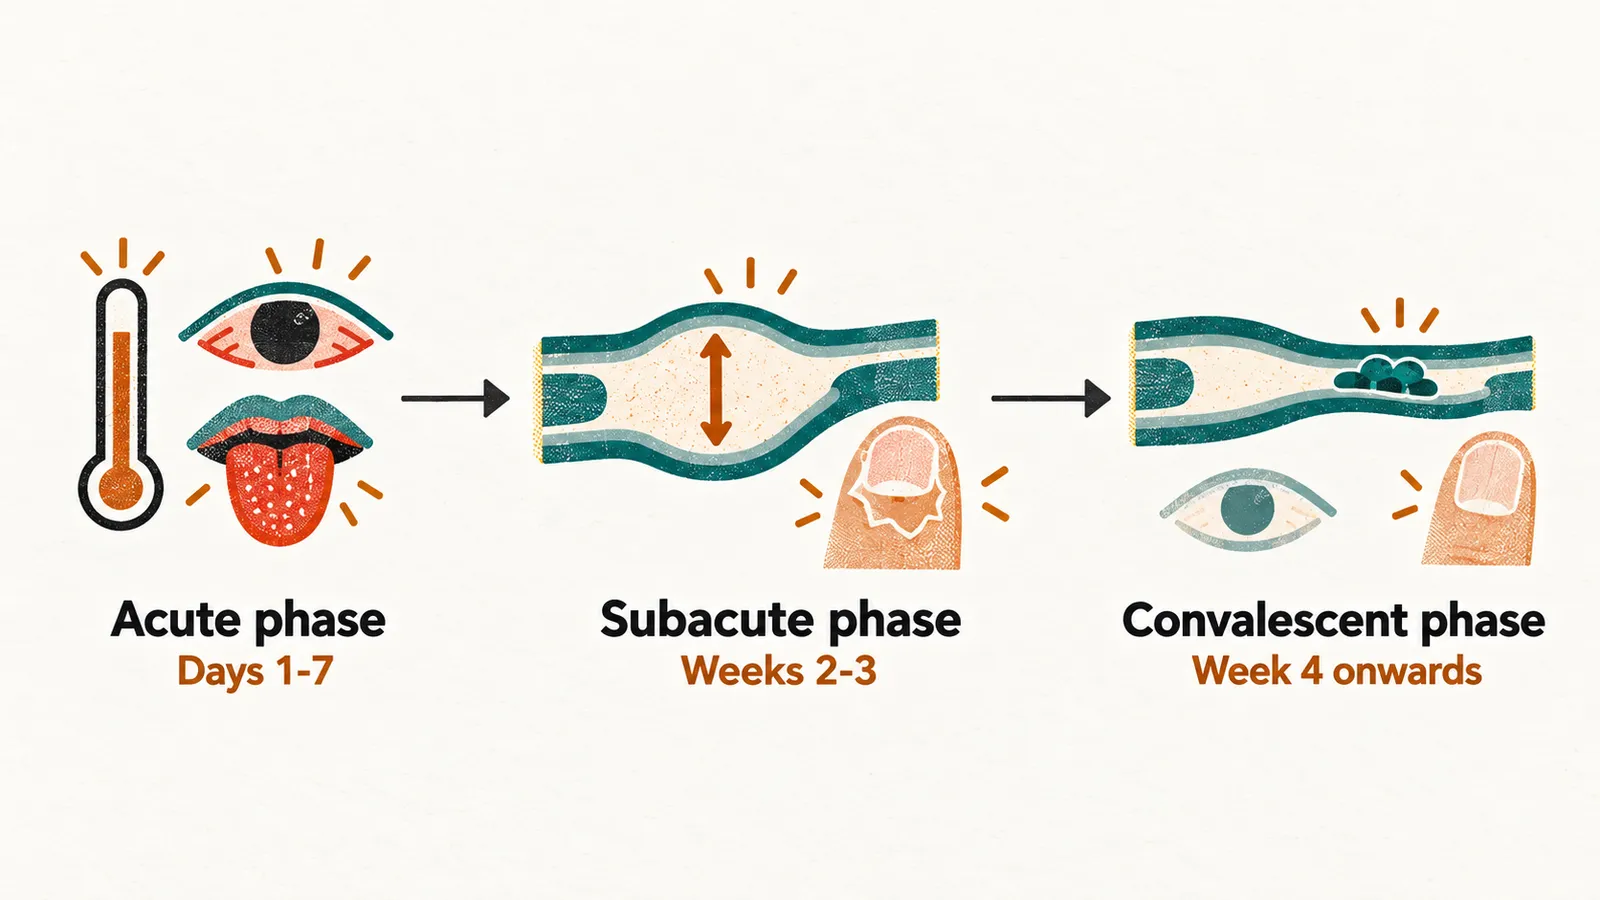
The inflammation in the arterial wall keeps running and feeds on itself, so the illness changes over time rather than staying the same. It moves through three phases.
The acute phase is days 1-7 from fever onset. It brings the fever and the five principal features, with irritability. Myocardial and pericardial inflammation are present, often subclinical.
The subacute phase is weeks 2-3. Coronary artery dilation and aneurysm appear now. Periungual desquamation appears, and the platelet count rises.
The convalescent phase is week 4 onwards. The clinical features resolve. If an aneurysm has formed, there is a risk of coronary thrombosis, because a clot can form inside it and block the artery. Risk stratification is guided by cardiac involvement.
The most specific features come late in this sequence. Why is the illness easy to miss at first?
Why is it easy to miss?
The illness is easy to miss at the first consultation because its most specific features come late. The finding that matters most, coronary artery dilation, appears in the second and third week, after the point at which treatment is most effective.
The features are individually non-specific and the most specific ones come late, so the differential is broad. Most of it is infection. What else looks like it?
What else looks like it?
Many illnesses share fever and rash with Kawasaki disease, so each has to be separated from it:
- Epstein-Barr virus and other viral infections cause fever, rash and lymphadenopathy. Atypical lymphocytes, pharyngitis with exudate and splenomegaly point away from Kawasaki disease.
- Scarlet fever shares the strawberry tongue. Its rash is fine and sandpaper-like, and the child has pharyngitis with a positive streptococcal test.
- Measles, roseola infantum and other exanthems are usually separated by the absence of conjunctival, oral and extremity changes.
- A bacterial infection that has failed to respond to antibiotics. This includes urinary tract infection when there is sterile pyuria, and pneumonia when there are respiratory findings.
- Drug reactions and hypersensitivity, where the history is the discriminator.
Two inflammatory illnesses share several features, and a third alternative is identified from the history.
- Systemic JIA shares fever, rash and arthritis with Kawasaki disease. The fever pattern differs: daily spikes in systemic JIA, sustained fever in Kawasaki disease. The echocardiogram is decisive. In Kawasaki disease it shows coronary involvement; in systemic JIA it shows, when present at all, pericardial involvement.
- Multisystem inflammatory syndrome following SARS-CoV-2 infection is a distinct post-infectious hyperinflammatory illness. It is a complication that comes after the infection rather than the infection itself. It can also produce fever, rash, conjunctivitis and coronary involvement, so it shares features with Kawasaki disease, but it is treated differently. It is distinguished by age, by an epidemiological link to a preceding infection, and by a different pattern of organ involvement.
With so many look-alikes, how is Kawasaki disease recognised?
How is it recognised, then?
The diagnosis is clinical, and there is no confirmatory laboratory test. Its features are individually non-specific, so the diagnosis rests on a pattern. No single feature identifies the disease. The diagnosis is made from how many principal features are present, how long the fever has lasted, and what the laboratory tests and echocardiogram show. If no single feature decides it, how many must be present, for how long must the fever last, and what do the tests and echocardiogram add?