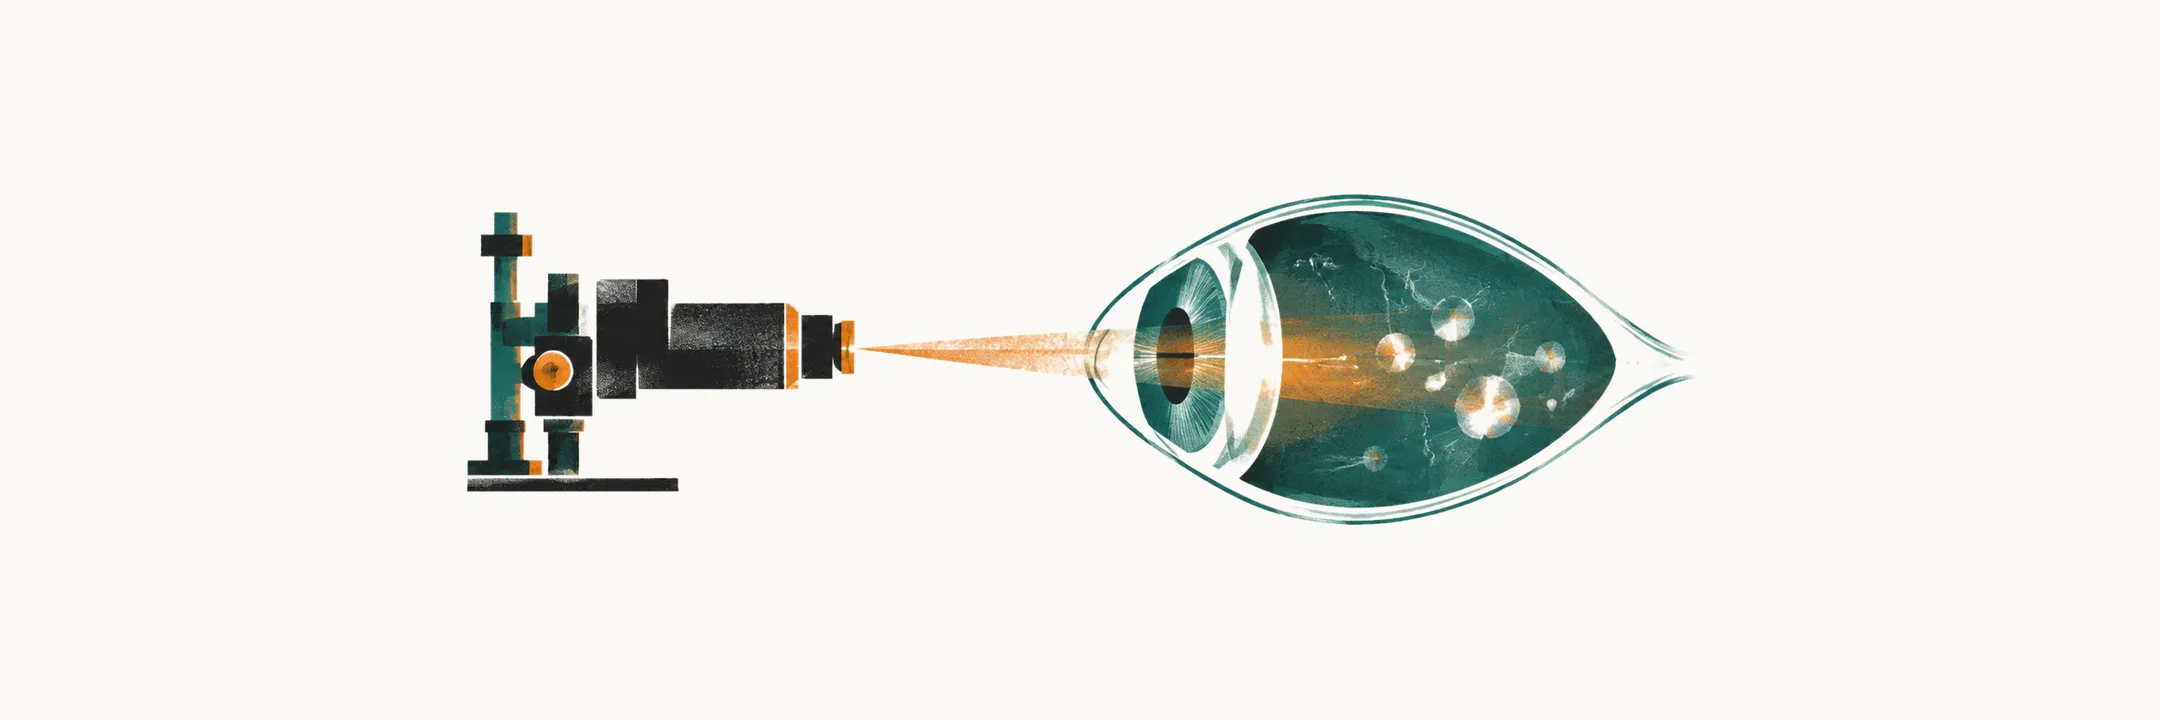
Why can an eye be damaged when nothing shows outside? In most children the early stages of chronic anterior uveitis have no redness, no pain and no change in vision, so the child appears entirely well. It usually produces none of the symptoms that would bring a child to the doctor. That is why it is the juvenile idiopathic arthritis complication that justifies the most attention, and why the eye is examined on a schedule, not because of a complaint. The joints may not warn about the eye, so the eye needs its own check.
What sits inside the eye, and where does its fluid come from?
Behind the cornea lies the anterior chamber, a fluid-filled space. The iris sits in front of the lens and separates this chamber from the space behind it. Behind the iris is the ciliary body, a ring of tissue whose inner layer makes the fluid that flows into the chamber. Chronic anterior uveitis is inflammation of the iris and the ciliary body, at the front of the eye. When this part of the eye is inflamed, cells appear in the fluid, and the cells the doctor looks for float in it.
How does a doctor see cells too small to see?
The examination that finds them is the slit-lamp examination, a magnified examination with a narrow beam of light. Cells show up as reflective particles floating in the fluid of the anterior chamber. So the slit lamp can show inflammatory cells in the anterior chamber before anything is visible from outside.
What does the inflammation leave behind?
Untreated chronic inflammation in the anterior chamber leaves permanent structural damage. The iris sticks to the lens, forming synechiae. A cataract develops. The cataract is sometimes accelerated by the corticosteroid drops used to treat the inflammation, and a proposed explanation is that the drops themselves speed the clouding of the lens.
Glaucoma follows from both the inflammation and the treatment. The fluid made by the ciliary body has to drain out of the eye through a drainage channel. Steroid-induced rises in eye pressure are thought to involve the cells of that channel, and a raised pressure can damage the optic nerve. The end result can be permanent visual loss. These harms are the reason treatment has to be weighed carefully.
Why can the joints be quiet while the eye is not?
Uveitis can be present and active while the joints are quiet. As the Juvenile Idiopathic Arthritis note showed, a child with well-controlled arthritis may still have active eye disease. So a child with this disease needs a rheumatology and ophthalmology follow-up plan, not only a prescription. The screening frequency is set by the number of risk factors, so the risk groups in the next section matter.
Which children get eye checks, and how often?
The uveitis risk is not spread evenly across the categories of arthritis. It follows particular categories and particular antibodies. Hence screening is a matter of counting risk factors, not watching for symptoms. The risk factors are age at onset, ANA status, category and disease duration. ANA status is one of them, as the JIA note explains.
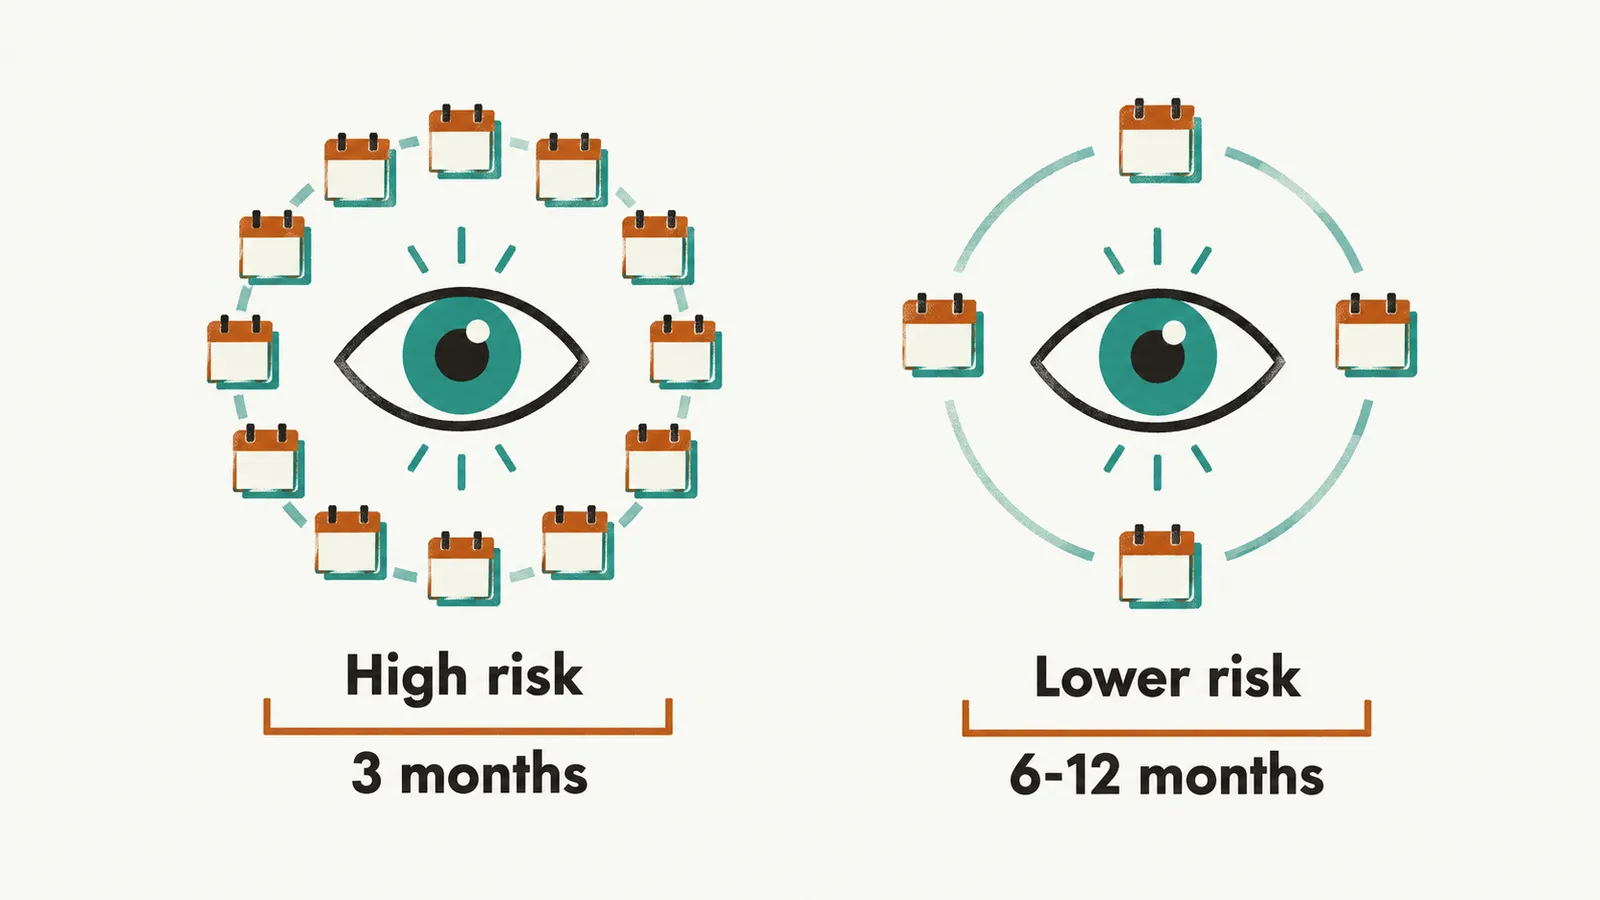
High risk means one of these categories: oligoarthritis, RF-negative polyarthritis, psoriatic arthritis or undifferentiated arthritis. It also requires all three of the following:
- ANA positivity
- onset before 7 years of age
- disease duration of 4 years or less
In current guidance, high-risk children are screened every 3 months.
Lower risk means one of the same categories, but with ANA negativity, or onset at 7 years or older, or disease for more than 4 years. The lower-risk group also includes systemic JIA and RF-positive polyarthritis. These children are screened every 6-12 months, depending on the combination of risk factors.
Two other groups need screening as well. Children with enthesitis-related arthritis and children carrying HLA-B27 are at risk of both chronic anterior uveitis and the acute anterior uveitis of spondyloarthritis.
The ophthalmologist adjusts the schedule as the risk changes. Screening is continued for years, and it does not stop because the joints are quiet. Once an eye check finds inflammation, the next question is treatment.
What treats the eye, and what does each option cost the eye?
Treatment is stepped. The aim is to control the inflammation while reducing exposure to topical steroids, because topical steroids carry the risks of cataract and glaucoma, the long-term complications described above.
Topical glucocorticoids are the initial treatment, and prednisolone acetate 1% drops are the usual choice. For short-term control, adding or increasing topical drops is preferred to adding systemic glucocorticoids. The JIA note gave one reason for that preference: steroids given by mouth can impair growth. Steroid drops work fast, but they carry these risks.
So what happens when the eye still needs 1-2 drops a day of topical glucocorticoid for control? Systemic treatment is added or escalated so that the drops can be tapered. Methotrexate is the standard disease-modifying drug in JIA, and it is the usual drug to add. Subcutaneous methotrexate is preferred to oral methotrexate for this purpose, since it is absorbed better than the tablet form.
What happens when the eye is at risk of losing sight?
Methotrexate alone is often not enough to stop the eye inflammation from progressing. When a biologic is needed, the monoclonal antibody TNF inhibitors adalimumab and infliximab are preferred to etanercept. In severe, sight-threatening uveitis, methotrexate and a monoclonal antibody TNF inhibitor are started together rather than methotrexate alone.
When the eye disease is controlled on systemic treatment alone, the therapy is not tapered until it has been well controlled for at least 2 years.
A child with established uveitis is monitored more closely than a child being screened, and the timing of examinations follows the treatment:
- While the disease is controlled on stable treatment, ophthalmic monitoring is no less frequent than every 3 months.
- When topical glucocorticoids are tapered or stopped, monitoring is within 1 month of each change.
- When systemic treatment is changed, monitoring is within 2 months of the change.
Each change of treatment needs an eye check to see whether it works.
Which children are least affected?
Uveitis affects most the categories with an early, ANA-positive, oligoarticular pattern. It is uncommon in systemic JIA, which sits in the lower-risk group alongside RF-positive polyarthritis. The danger in systemic JIA lies elsewhere: in the systemic inflammation itself, and in a complication that can turn controlled disease into an emergency within days. In Systemic Juvenile Idiopathic Arthritis and Macrophage Activation Syndrome the eye is not the main threat, so what is the threat, and how fast can it arrive?