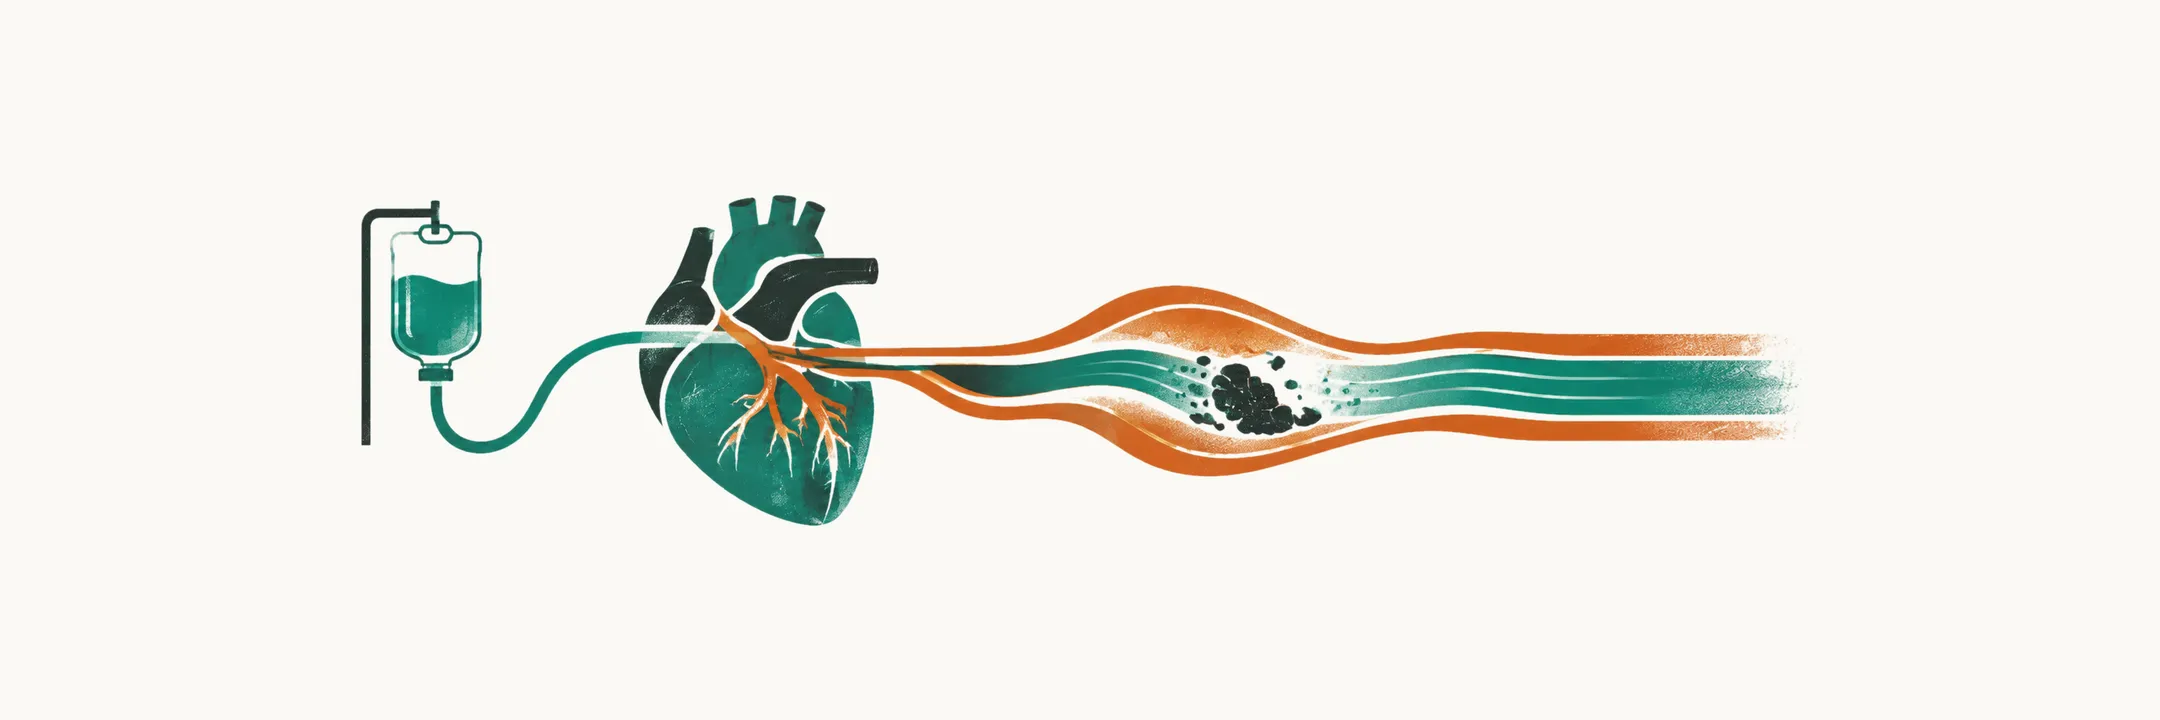
The coronary arteries are the one place where Kawasaki disease can leave lasting harm, and the inflammation of the illness is thought to injure their walls while it is active. So treatment has two jobs at two moments. The first is to calm the inflammation while it is still acting on the wall, and intravenous immunoglobulin (IVIG) and high-dose aspirin should start early. The second is to reduce the risk of clots forming in a wall that is still abnormal or healing, which is the work of low-dose aspirin, given for as long as the wall stays abnormal. The fever resolves over days to weeks, and the long-term plan follows the arteries, not the temperature.
Why does a fever that settles on its own need treatment?
Because the fever is not the danger. Untreated, roughly a quarter of children develop coronary artery dilation or aneurysm. Treated with IVIG inside the correct time window, the great majority recover with normal coronary arteries. That is why treatment is built around a single time-limited decision.
Early IVIG given with high-dose aspirin is associated with less coronary artery disease. Treatment should be given within 10 days of fever onset, and as soon as the diagnosis is secure.
The stakes are wider than one illness. Coronary aneurysms from Kawasaki disease are the leading cause of acquired heart disease in children in developed countries. This is why a febrile child who does not fit the usual patterns deserves echocardiography rather than another antibiotic.
So when should the infusion be given, and how much?
What does the first infusion do, and when?
IVIG is the cornerstone of treatment, and its timing matters more than any other single decision in the illness. The dose is 2 g/kg as a single infusion. It is usually given over 10-12 hours, and more slowly if there is cardiac dysfunction.
The time limit works at both ends. A diagnosis may be secure by day 4 in a child with 4 or more features, and then treatment should not wait. When the diagnosis can safely wait, treatment is usually started from day 5 onwards. In a meta-analysis of more than 70,000 patients, IVIG before day 5 of fever was associated with a higher rate of treatment failure and need for retreatment, with an odds ratio of about 2.2, roughly twice the odds.
At the other end, treatment after day 10 is indicated when the child is still febrile or has active coronary involvement. If the fever has resolved and the coronary arteries are normal, late IVIG has no demonstrated benefit.
And what happens when the first dose does not work?
What if the fever does not go?
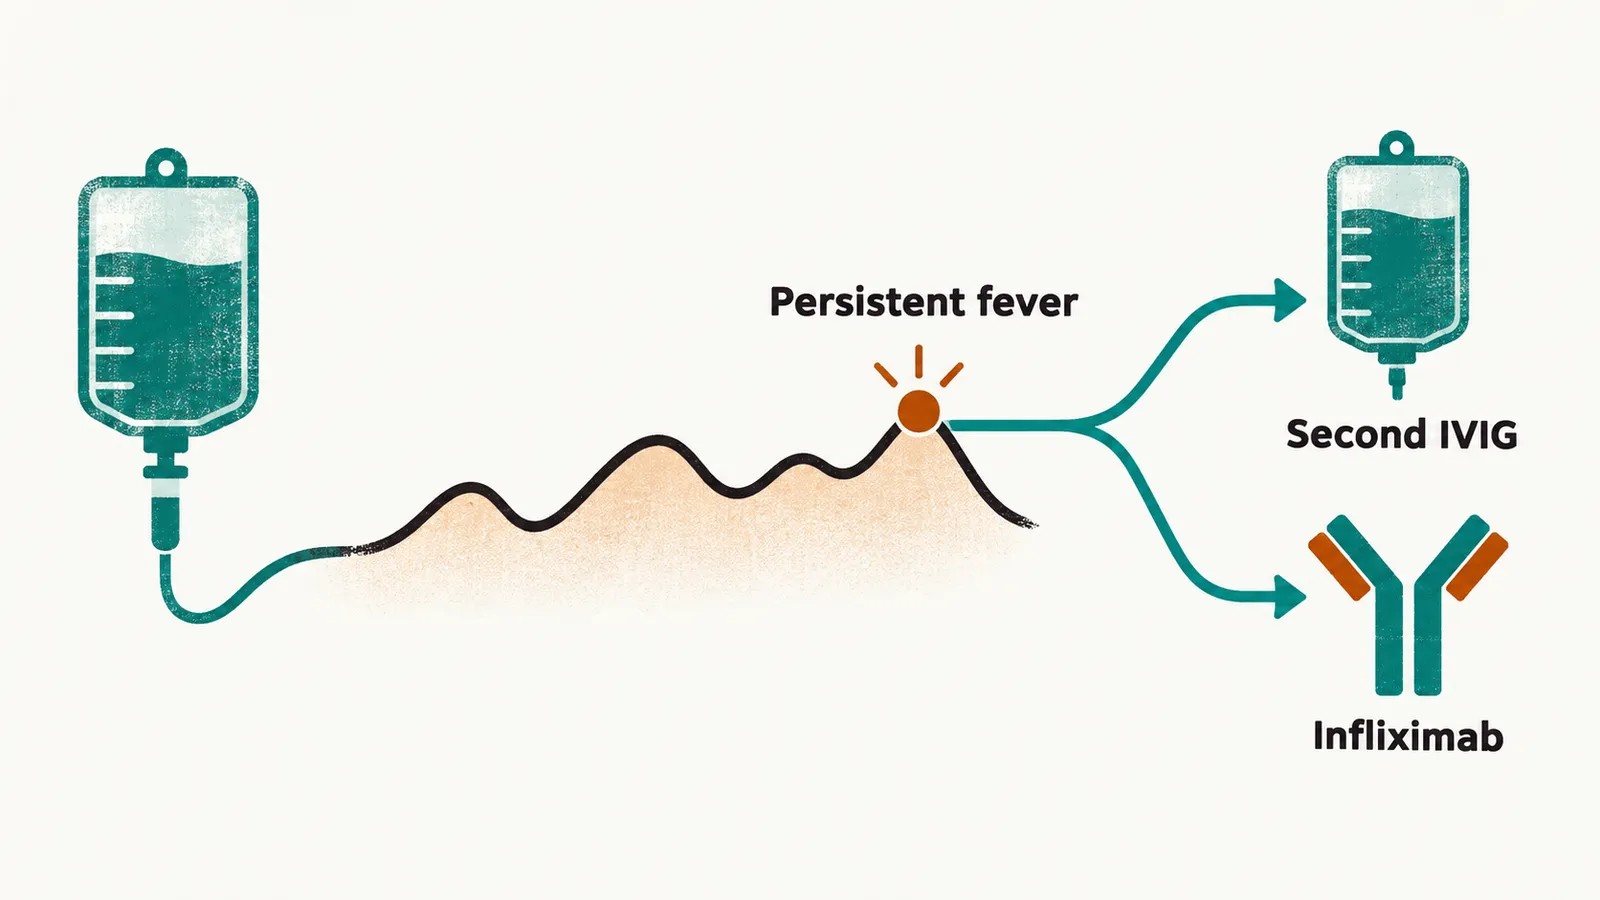
Not every child responds to the first infusion. Approximately 10-20% of children remain febrile 36 hours or more after it. Persistent fever at that point is called IVIG resistance, and its prevalence is around 14% in pooled series.
The usual next step is a second dose of IVIG at the same dose, 2 g/kg, given at least 36-48 hours after the first. Alongside this, fever control, fluid and electrolyte management, and treatment of any cardiac failure or arrhythmia are handled as they arise.
Is a second dose the only next step?
What is used instead of a second dose?
The alternative is infliximab, an antibody that blocks tumour necrosis factor (TNF). Infliximab is used as salvage therapy, an option when IVIG has not ended the fever.
In a randomised trial, infliximab ended fever more often than a second IVIG dose: 77% versus 51% of children were afebrile at 24 hours without recurrence within 7 days. The infliximab group also had a shorter hospital stay and fewer serious adverse events. Yet inflammatory markers and coronary artery outcomes were similar at study completion.
The fever is not the whole picture, so why does aspirin come next?
Why is aspirin given at two doses?
IVIG and aspirin are the standard initial treatment. Aspirin is given alongside IVIG at two very different doses for two different reasons.
In the acute phase the dose is 80-100 mg/kg/day in divided doses, until the child has been afebrile for 48-72 hours. Its purpose is anti-inflammatory, and the high dose has an anti-inflammatory action that the low dose does not.
After that, for about 6-8 weeks, the dose is 3-5 mg/kg/day once daily. Its purpose is antiplatelet, to reduce thrombotic risk while the coronary arteries are abnormal or healing. The low dose has antiplatelet action that the high dose is not used for. Aspirin continues while the artery is abnormal or healing, and can stop once it is normal.
Aspirin is avoided in children in most other circumstances because of its association with Reye syndrome, an acute illness of brain and liver. Kawasaki disease is one of the few remaining indications for high-dose aspirin in paediatrics.
If everyone gets IVIG and aspirin, which children start with more?
Which children start with more treatment?
Some children are treated more intensively from the outset. Children at increased risk of coronary aneurysm get close monitoring and intensified first treatment. The higher-risk features are:
- age under 1 year, especially under 6 months
- markedly raised inflammatory markers, particularly CRP
- anaemia or low albumin at presentation, or raised liver enzymes
- shock, or macrophage activation syndrome
For these children, corticosteroids are added to the initial IVIG and aspirin. The corticosteroid is given as a single intravenous dose of methylprednisolone before the infusion, or as a short course afterwards. Methylprednisolone pulse therapy for three days is used in severe disease and in non-responders. The evidence for routine corticosteroids in all children with Kawasaki disease, rather than only those at high risk, continues to evolve.
Once this first treatment is done, what decides the long term?
What decides the long term?
Fever and mucocutaneous features resolve over days to weeks, and most children recover completely. The long-term outcome is decided almost entirely by the coronary arteries, and the long-term plan is set by what echocardiography has shown:
- No coronary involvement in the first 6-8 weeks: aspirin can be stopped, and there is no routine restriction.
- Transient dilation that resolves: aspirin until it has resolved.
- Small or medium persistent aneurysm: continued aspirin, with cardiology follow-up and imaging.
- Giant aneurysm: long-term aspirin plus anticoagulation, and restriction of vigorous physical activity.
Anticoagulation appears in the plan because coronary thrombosis is the mechanism of the late deaths. Children with large or giant aneurysms may need it in addition to aspirin. Physical activity restriction is tied to the severity of coronary involvement. It is difficult to maintain, because children feel entirely well once the inflammation has settled.
Some features have been reported to predict a worse outcome: male sex, diagnosis after day 10 of fever, fever lasting more than 10 days, and neutrophil predominance.
The coronary arteries are one target of the immune system in childhood, so what are the others?
What is the heart’s immune target in other illnesses?
Kawasaki disease is not the only childhood illness in which the heart is the target of an immune response, but not every such illness attacks arteries. When the valves are the target instead, and the triggering bacterium has long since been dealt with, the disease appears weeks after the sore throat that started it. If the immune system can damage the heart valves weeks after a sore throat, what is it aiming at, and why does it wait?