
The coronary artery is what matters in Kawasaki disease, but nobody can see it by looking at a child. So the diagnosis is a bedside count: the principal signs stand in for the artery, and enough of them, for long enough, make the illness likely. Some children show only part of the pattern, and then the count is not enough. The blood shows whether systemic inflammation is present at all, and the echocardiogram looks at the artery itself. Those two carry the weight when the count falls short.
How many of the signs make the diagnosis?
The earlier note described the five principal features, and no one of them identifies the disease on its own. The question now is how many have to be present, and for how long. The five are:
- bilateral conjunctival injection without exudate;
- changes of the lips and oral cavity;
- a polymorphous rash;
- erythema and oedema of the hands and feet;
- cervical lymphadenopathy, usually unilateral.
Fever for at least 5 days plus at least 4 of these 5 features is complete (classical) Kawasaki disease. When 4 or more features are present, the diagnosis can be made from day 4 of fever. Waiting for the fifth day is not necessary.
Irritability, arthralgia, hydrops of the gallbladder and sterile pyuria are common in Kawasaki disease. They do not count towards the rule.
What if the child has only some of the signs?
The count is not always met, and the rule then needs evidence beyond the bedside. Fever for at least 5 days plus 2 or 3 features, with supportive laboratory findings or echocardiographic coronary changes, is generally called incomplete Kawasaki disease.
A child can have Kawasaki disease without ever meeting the classical rule. For these children the laboratory tests and the echocardiogram carry the weight of the diagnosis. When the disease is strongly suspected, the child is examined by echocardiogram even without the classical count, because the artery can be involved.
Why are the youngest the ones most often missed?
The count falls shortest in the youngest, so the blood and the echocardiogram are the further evidence. Incomplete disease is the usual presentation in infants under 1 year. Infants are handled separately because they present with fewer features. Their presentations are often incomplete and may mimic common infections, so blood tests and an echocardiogram are needed. That is why infants under 1 year are the group most likely to be missed.
Two rules follow from this:
- An infant 6 months old or younger with fever for 7 days or more and no other explanation should have laboratory testing.
- If there is evidence of systemic inflammation, that infant should have an echocardiogram, even with no principal features at all.
Why do the names for the partial picture disagree?
A child who falls short of the full count is described in several ways, and the words are not used the same way everywhere. Terminology varies between sources. Some use “incomplete” and “atypical” interchangeably for any presentation that does not meet full criteria. Others reserve “atypical” for a child whose findings are unusual rather than merely fewer. The unusual findings are:
- pericarditis;
- myocarditis;
- aseptic meningitis;
- arthritis;
- severe gastrointestinal involvement;
- respiratory findings.
Both words describe the same disease.
Why can no blood test confirm it?
Since the count cannot settle every child, the next question is what the blood can add. No laboratory finding confirms the diagnosis. The tests reflect the systemic inflammation of the acute illness, and many inflammatory indices change throughout the disease process. A raised value therefore shows that inflammation is present, not which illness causes it. Even so, the tests support the diagnosis and drive the algorithm for incomplete disease.
Which blood markers show the inflammation?
Two general markers of inflammation appear throughout: C-reactive protein (CRP) and the erythrocyte sedimentation rate (ESR). Both are raised. They are both markers of the acute-phase response, and CRP is the better marker of that response. The white cell count is raised too, with neutrophil predominance, because it changes in the same inflammatory response.
The two markers do not move at the same pace: the ESR falls more slowly than the CRP. A proposed reason is that the ESR depends mostly on fibrinogen, while CRP follows the acute-phase reaction more closely, so the two need not fall together.
Why do the platelets come too late to decide?
The platelets rise later than the other markers, so they are read after the early decision. The platelet count is normal early and rises in the subacute phase; thrombocytosis is the characteristic laboratory feature of the subacute phases. The rise comes too late to help the diagnosis, and it can support it looking back. A platelet count of 450,000/mm³ or more counts as a supportive finding after day 7.
The haemoglobin shows a mild anaemia in the acute phase. Early anaemia is associated with more severe disease.
What do albumin, ALT and the urine add?
The rest of the blood and urine show the same systemic inflammation, and the urine also separates the disease from an infection.
- The alanine aminotransferase (ALT) is mildly raised.
- The albumin is low. Albumin is a negative acute-phase reactant, so it falls as the inflammatory response rises. A value of 3.0 g/dL or less is a supportive finding.
- The urinalysis shows sterile pyuria. A study reports that these white cells come from the urethra or the kidney. In most children with the disease the pyuria is sterile, so white cells appear without bacteria, and that is useful for distinguishing a febrile child with Kawasaki disease from one with a urinary tract infection. Here 10 or more white cells per high-power field is the supportive finding.
How do the markers decide the next step?
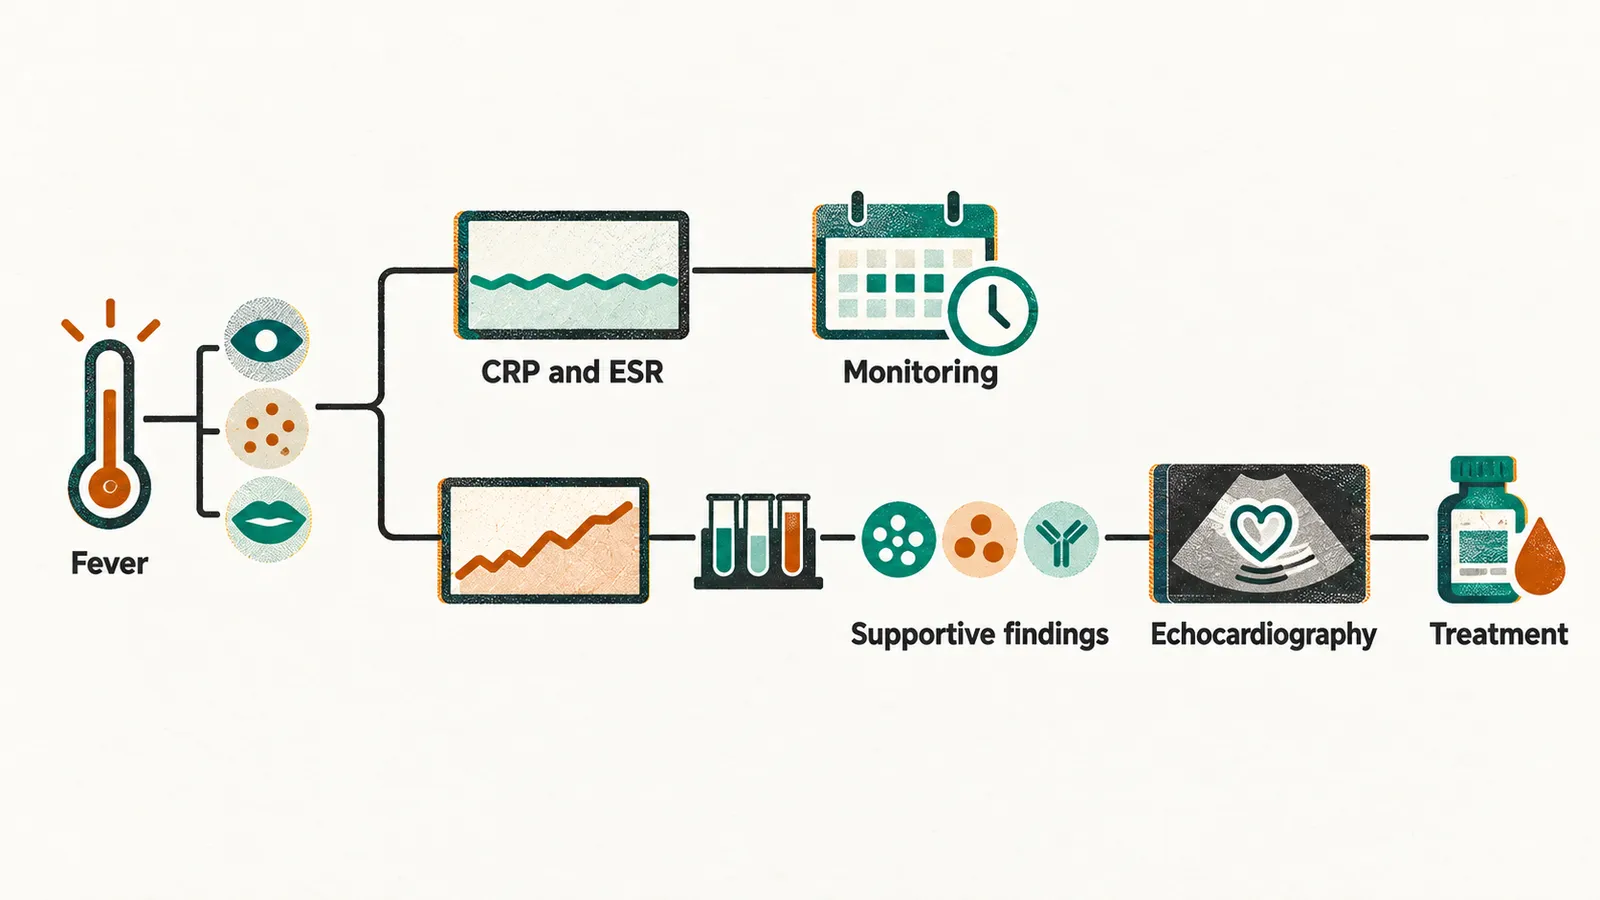
The markers are a gate, and the next step depends on how many supporting findings are present. A widely used algorithm for a child with fever and fewer than 4 features starts from the CRP and ESR, which show whether systemic inflammation is present at all, and then counts supportive laboratory findings.
- Fever for 5 days or more with 2-3 features and a normal CRP and ESR: continue clinical and laboratory monitoring with serial echocardiography. If coronary abnormalities appear, the diagnosis is made.
- Fever for 5 days or more with 2-3 features and a raised CRP or ESR: obtain further laboratory tests, namely a full blood count, liver enzymes, albumin and urinalysis.
If 3 or more of 6 supportive criteria are present, obtain an echocardiogram and treat as Kawasaki disease. The six criteria are:
- anaemia for age;
- a platelet count of 450,000/mm³ or more after day 7;
- albumin of 3.0 g/dL or less;
- a raised ALT;
- a white cell count of 15,000/mm³ or more;
- 10 or more white cells per high-power field on urinalysis.
Why does the coronary scan outrank the blood tests?
The blood tests point to inflammation, and the echocardiogram is the test that looks at the artery. Coronary abnormalities on echocardiography at any point establish the diagnosis, regardless of laboratory results.
This makes echocardiography the most important investigation. Transthoracic echocardiography is the imaging test of choice, and it images the coronary artery itself, which no blood test can show. In the incomplete form it is the only investigation that can establish the diagnosis.
Why does a normal first echocardiogram not end the question?
The artery is examined at diagnosis and again, because it changes over the weeks. The first study looks for early coronary involvement. Aneurysms form later, so a normal study at diagnosis does not exclude the disease. Coronary arteries can be normal on the day of diagnosis and abnormal two weeks later.
The arteries must therefore be re-examined as the disease evolves. Repeat studies are typically done at diagnosis and again at about 1-2 weeks and 4-6 weeks.
How is the artery’s size judged?
A size is read against the child’s body size, which is why the Z-score is used. Coronary artery dimensions in children are reported as Z-scores, the number of standard deviations from the expected value for body surface area. Absolute diameters are uninterpretable across different ages and sizes, so the Z-score adjusts the raw diameter for body surface area.
The grades are:
- dilation: Z-score 2 to less than 2.5;
- small aneurysm: Z-score 2.5 to less than 5;
- medium aneurysm: Z-score 5 to less than 10;
- giant aneurysm: Z-score 10 or more.
What does the grade decide?
The grade is the basis for the long-term plan. The severity of coronary involvement determines that plan, so the echocardiogram is also used for risk stratification: it grades what the plan will follow. Echocardiography establishes which children already have coronary involvement.
If the scan may look normal early, what decides whether to treat?
Preventing coronary involvement is a separate decision. Because an early echocardiogram can look normal, it cannot be what decides preventive treatment. That decision is taken on clinical grounds, before any of these results are available. So what is given to protect the artery, and how soon must it start?